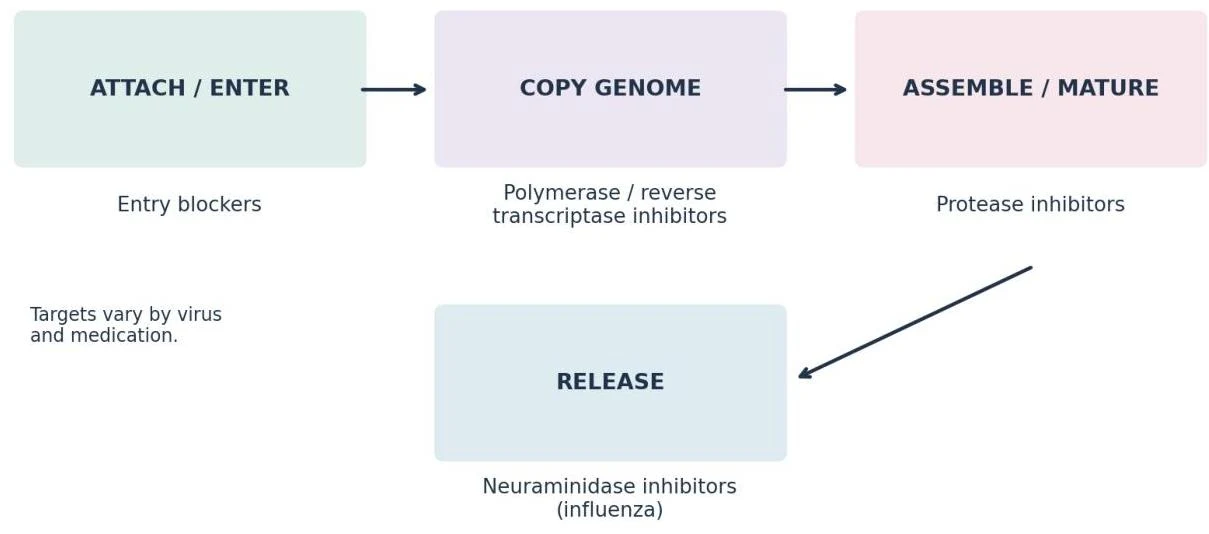
- Attachment and Entry Inhibitors: These prevent the virus from binding to or entering the host cell. Examples include Fostemsavir (which binds to the gp120 protein) and Maraviroc (a CCR5 antagonist).
Nursing Alert: Before administering Maraviroc, a tropism test must be performed to confirm the specific HIV strain uses the CCR5 receptor; otherwise, the drug will be ineffective.
- Reverse Transcriptase Inhibitors: HIV is a retrovirus, meaning it must convert its RNA into DNA to integrate into the host genome.
- NRTIs (Nucleoside Reverse Transcriptase Inhibitors): Drugs like Zidovudine terminate the growing DNA chain. A major safety concern with NRTIs is bone marrow suppression, which can lead to pancytopenia (a decrease in red cells, white cells, and platelets).
- NNRTIs (Non-Nucleoside Reverse Transcriptase Inhibitors): Drugs like Efavirenz bind directly to the enzyme to disable it.
- Integrase Strand Transfer Inhibitors (INSTIs): These prevent the viral DNA from being inserted into the host's DNA. Examples include Dolutegravir and Raltegravir.
- Protease Inhibitors (PIs): These block the enzyme responsible for processing viral proteins into functional components, preventing the assembly of new, mature viruses.
- Ritonavir is frequently used in low doses as a "booster" because it inhibits the CYP3A enzyme, which slows the metabolism of other drugs and keeps their concentrations higher in the blood.
- Capsid Inhibitors: A separate class that targets the protein shell of the virus.
Clinical Complications: IRIS
As ART begins to work, the immune system may "rebound" and become strong enough to recognize and attack existing, latent infections (such as Tuberculosis). This can cause an intense, paradoxical inflammatory response known as Immune Reconstitution Inflammatory Syndrome (IRIS).
Prevention: PrEP and PEP
- PrEP (Pre-Exposure Prophylaxis): Taken by HIV-negative individuals at high risk of exposure to prevent infection. This can include daily oral pills or long-acting injections like Cabotegravir.
- PEP (Post-Exposure Prophylaxis): Urgent medication taken after a potential exposure to prevent the virus from establishing an infection.
Influenza and COVID-19 Management
For respiratory viruses like Influenza and SARS-CoV-2, timing is everything. Most antivirals are most effective when started within 48 hours of symptom onset.
Influenza Medications
- Neuraminidase Inhibitors (NAIs): These block the release of new virus particles from infected cells. Oseltamivir (Tamiflu) is used for both Influenza A and B and can be used for prophylaxis in family members exposed to the virus.
- Cap-dependent Endonuclease Inhibitors: Baloxavir is a newer, single-dose medication for Influenza A and B.
Safety Note: Baloxavir may contain sorbitol, making it contraindicated for patients with fructose allergies. Additionally, patients should avoid taking it with dairy or calcium supplements, as these reduce absorption.
- M2 Ion Channel Inhibitors: Amantadine was once used for Influenza A but is no longer recommended due to widespread viral resistance. Interestingly, it is sometimes used as an adjunct in Parkinson’s disease due to its dopamine activity.
COVID-19 Medications
- Remdesivir: An IV nucleotide analogue used for hospitalized or high-risk patients. Nurses must monitor for hepatotoxicity (liver injury), as it can cause significant elevations in liver enzymes.
- Paxlovid: An oral combination containing a protease inhibitor. Because it inhibits CYP3A, it has a high potential for dangerous drug-drug interactions.
Hepatitis C: The Path to a Virologic Cure
Unlike HIV or Herpes, Hepatitis C (HCV) can often be cured using Direct-Acting Antivirals (DAAs). A virologic cure is defined as having undetectable HCV RNA levels 12 weeks after completing treatment.
Safety and Monitoring
- Hepatitis B Reactivation: This is a critical safety requirement. Because HCV and HBV often coexist, treating HCV with DAAs can cause a sudden "flare" or reactivation of Hepatitis B. All patients must be screened for Hepatitis B before starting HCV therapy.
- Liver Health: Chronic HCV can lead to cirrhosis, which may cause jaundice, ascites, and encephalopathy.
Herpes Simplex (HSV) and Varicella-Zoster (VZV)
Antivirals for the herpes family, such as Acyclovir and Valacyclovir, are effective at treating active outbreaks and reducing the duration of symptoms. However, they do not eliminate the latent virus that resides in the nerve ganglia.
Nursing Priority: When administering IV Acyclovir, ensure the patient is well-hydrated and the infusion is given slowly (over at least 1 hour) to prevent nephrotoxicity (kidney damage) caused by crystal formation. Avoid combining Acyclovir with other nephrotoxins like NSAIDs.
Summary of Nursing Priorities
| Symptom/Finding | Potential Cause | Nursing Action |
|---|
| New fever, pallor, or weakness | Bone marrow suppression (NRTIs) | Check CBC for anemia/neutropenia |
| Jaundice, dark urine, or RUQ pain | Hepatotoxicity or HBV reactivation | Notify provider; check liver enzymes |
| Reduced urine output | Nephrotoxicity (Acyclovir) | Assess hydration and renal function |
| Suicidal thoughts or vivid dreams | CNS effects (Efavirenz) | Immediate safety assessment |
| Dyspnea or wheezing during infusion | Hypersensitivity reaction | Stop infusion; assess ABCs |