Anti-inflammatory Drugs: NSAIDs and Glucocorticoids in Veterinary Medicine
An overview of Nonsteroidal Anti-inflammatory Drugs (NSAIDs) and Glucocorticoids (GCs) used in veterinary medicine, detailing their mechanisms of action, pharmacokinetics, adverse effects, and alternative therapies like Piprants and Anti-NGF Mabs.
Managing inflammation and pain is a cornerstone of veterinary medicine, involving a diverse array of pharmacological tools. From traditional Nonsteroidal Anti-inflammatory Drugs (NSAIDs) to newer monoclonal antibodies and potent Glucocorticoids (GCs), each class targets specific biochemical pathways to alleviate suffering. Understanding the distinction between these mechanisms is vital for selecting the correct therapy while minimizing life-threatening adverse effects.
The Biochemical Foundation: The Arachidonic Acid Cascade
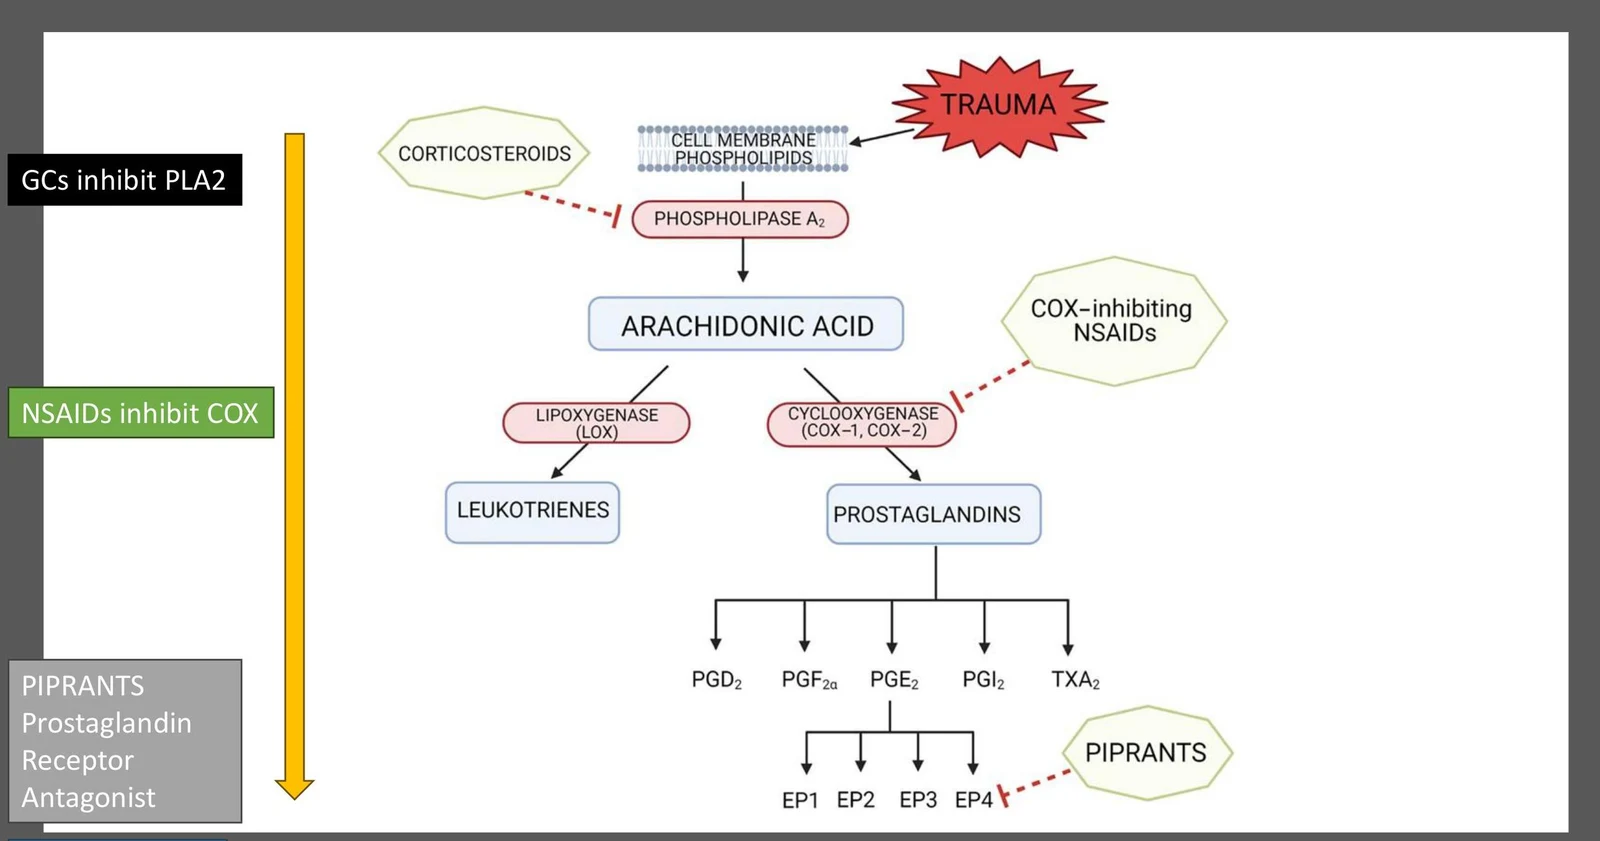
To understand how anti-inflammatory drugs work, one must first understand how inflammation begins. The process starts with the arachidonic acid cascade. When tissue is damaged or an immune response is triggered, enzymes act upon membrane phospholipids to release arachidonic acid. This acid is then processed by various enzymes to produce eicosanoids, including prostaglandins, which mediate pain, fever, and inflammation.
The primary target for most anti-inflammatory drugs is the enzyme cyclooxygenase (COX), which sits within this cascade. By inhibiting COX, drugs can block the subsequent prostaglandin synthesis, thereby reducing the chemical signals that cause pain and swelling.
This diagram illustrates the biochemical pathway of arachidonic acid metabolism, showing how corticosteroids and NSAIDs inhibit key enzymes like PLA2 and COX, respectively, leading to the production of leukotrienes and prostaglandins. It also depicts the role of PIPRANTS as prostaglandin receptor antagonists.
Nonsteroidal Anti-inflammatory Drugs (NSAIDs)
NSAIDs are widely used to minimize the unpleasant aspects of inflammation, specifically pain, pyrexia (fever), and swelling. They are approved for a variety of species, including dogs, cats, horses, cattle, and pigs.
COX-1 vs. COX-2 Inhibition
The clinical utility and safety of NSAIDs depend heavily on their selectivity for two different isoforms of the cyclooxygenase enzyme: COX-1 and COX-2.
COX-1 (Constitutive): This enzyme is present in most tissues and performs "housekeeping" functions. It is responsible for producing prostaglandins that protect the gastrointestinal (GI) lining, maintain renal blood flow, and regulate platelet function.
COX-2 (Induced): This enzyme is primarily produced in response to tissue damage or immune activation. It is the main driver of pain, inflammation, and fever.
NSAIDs are classified based on this selectivity:
Nonselective COX inhibitors: Inhibit both COX-1 and COX-2 (e.g., Aspirin, Phenylbutazone).
Slightly/Moderately selective COX-2 inhibitors: Prefer COX-2 but can inhibit COX-1 at higher doses (e.g., Meloxicam, Carprofen).
Highly selective COX-2 inhibitors (COXIBs): Target COX-2 with minimal impact on COX-1, theoretically reducing GI side effects (e.g., Firocoxib, Robenacoxib).
Pharmacokinetics and Pharmacodynamics (PK/PD)
The effectiveness and safety of NSAIDs are governed by their pharmacokinetics and pharmacodynamics (PK/PD). Most NSAIDs are lipid-soluble weak acids that are well-absorbed orally.
A critical factor in their distribution is plasma protein binding. Most NSAIDs are highly bound to plasma proteins, which limits their passage into interstitial fluids but facilitates their accumulation in inflammatory exudates. However, this high binding also means that drugs can compete for binding sites, and their clearance is heavily dependent on the liver and kidneys.
Exam Tip: Species-Specific Metabolism
Always remember that drug metabolism is species-specific. For example, cats have a decreased ability to perform glucuronidation, making certain NSAIDs more toxic to them.
Adverse Effects of NSAIDs
While effective, NSAIDs can cause significant damage to three main systems: the digestive, renal, and cardiovascular systems.
Gastrointestinal Ulcers
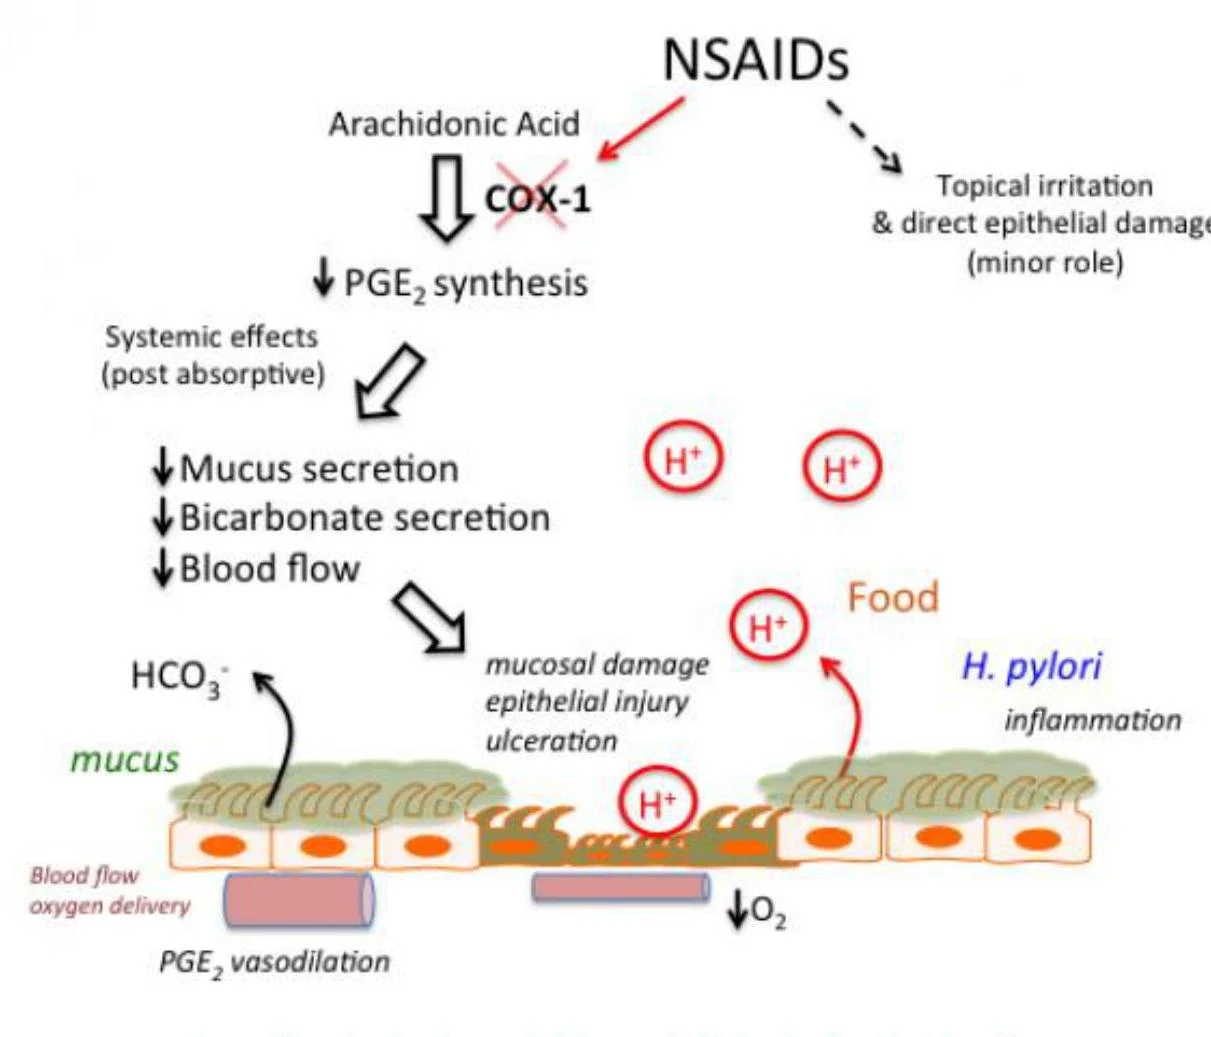
By inhibiting COX-1, NSAIDs reduce the production of mucosal-protective prostaglandins in the stomach. This can lead to gastrointestinal ulcers, vomiting, and bleeding. In horses, this may manifest as right dorsal colitis.
Diagram illustrating the mechanism of NSAID-induced gastric mucosal damage, including the role of COX-1 inhibition, reduced prostaglandin E2 synthesis, decreased mucus and bicarbonate secretion, and increased susceptibility to acid and H. pylori.
Renal Perfusion and GFR
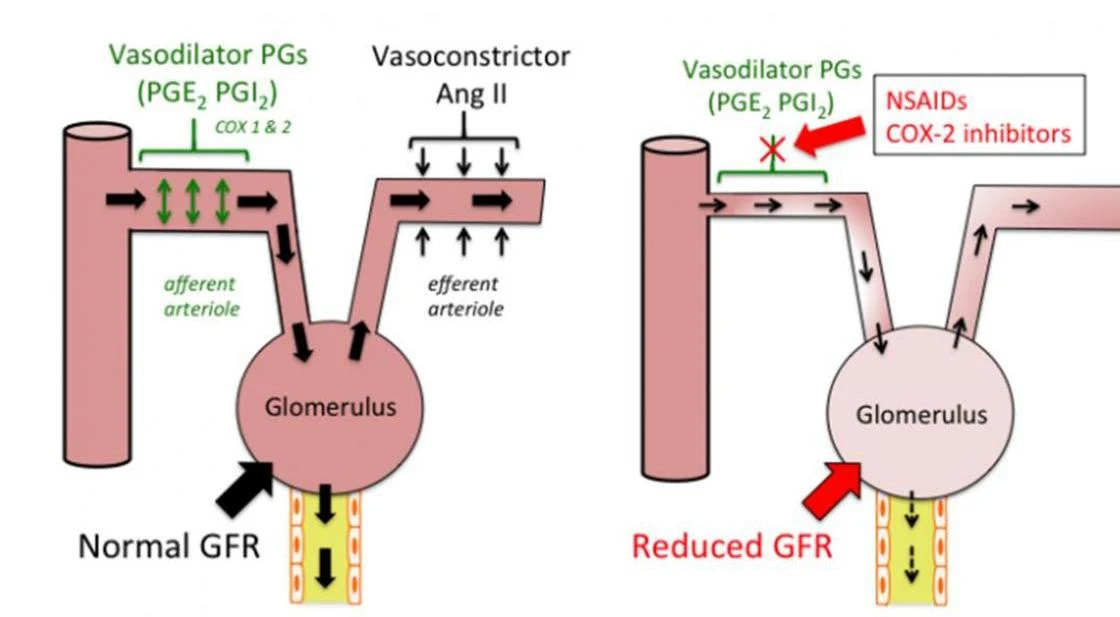
Prostaglandins are essential for maintaining renal perfusion and the glomerular filtration rate (GFR), especially in stressed or dehydrated patients. NSAIDs can block these vasodilatory prostaglandins, leading to reduced blood flow to the kidneys and potentially causing acute kidney injury.
Diagram illustrating the role of prostaglandins and Angiotensin II in regulating glomerular filtration rate (GFR), and the effect of NSAIDs on this process.
Cardiovascular Risk and Platelet Function
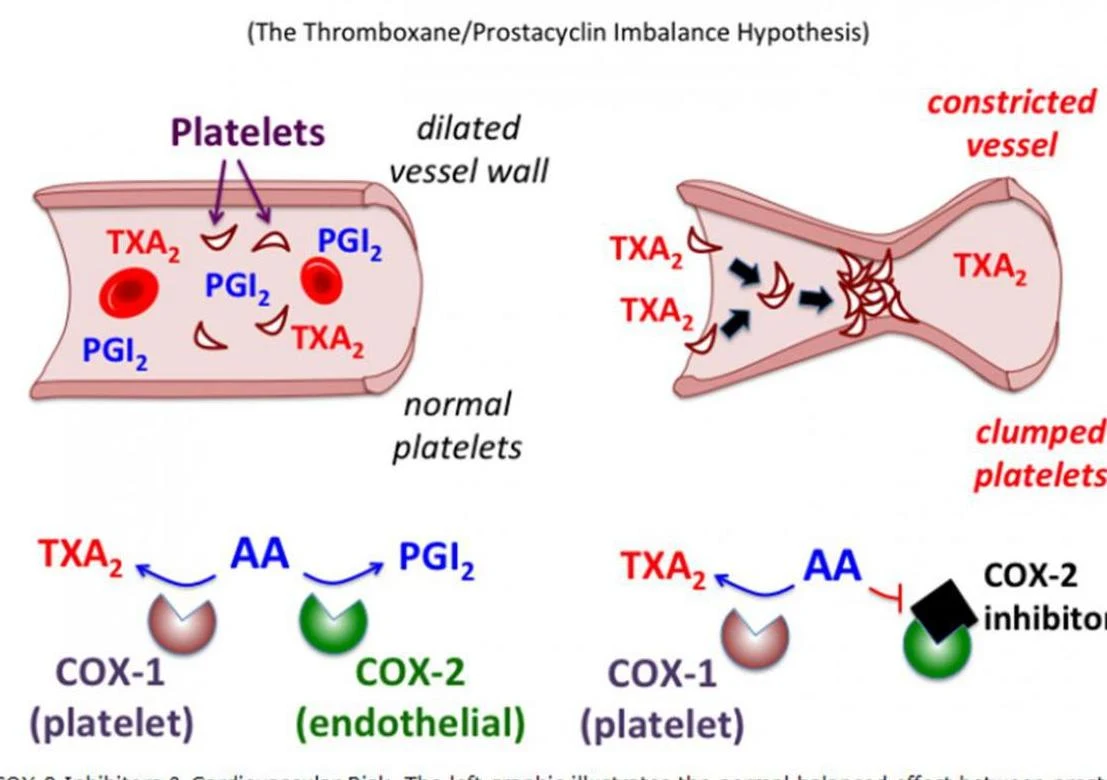
There is a delicate balance between thromboxane (TXA2), which promotes platelet aggregation and vasoconstriction (via COX-1), and prostacyclin (PGI2), which inhibits aggregation and promotes vasodilation (via COX-2). Selective COX-2 inhibition can tip this balance in favor of TXA2, potentially increasing the risk of cardiovascular events. Additionally, low-dose aspirin irreversibly inhibits platelet COX-1, leading to prolonged antiplatelet effects.
This diagram illustrates the thromboxane/prostacyclin imbalance hypothesis. The top left shows normal platelets in a dilated vessel, producing TXA2 and PGI2. The top right depicts constricted vessels with clumped platelets due to an imbalance. The bottom shows the enzymatic pathways: COX-1 in platelets produces TXA2, while COX-2 in endothelial cells produces PGI2 from AA. A COX-2 inhibitor blocks this pathway.
Alternative Therapies: Piprants and Anti-NGF Mabs
Piprants
Piprants (Prostaglandin Receptor Antagonists) represent a different approach. Instead of inhibiting the COX enzyme, they act as prostaglandin receptor antagonists. For example, Grapiprant binds to the EP4 receptor, preventing PGE2 from activating it. This provides analgesic and anti-inflammatory effects without interfering with the COX enzymes, potentially offering a safer profile for the GI tract.
Anti-NGF Monoclonal Antibodies (mAbs)
A newer class of drugs, Anti-NGF Mabs, targets Nerve Growth Factor (NGF). NGF is a signaling protein that, when produced by injured tissue, sensitizes nerve cells to pain. By using monoclonal antibodies like Bedinvetmab (Librela®) for dogs and Frunevetmab (Solensia®) for cats, clinicians can neutralize NGF and reduce pain associated with osteoarthritis.
Warning: Safety Concerns with Anti-NGF Mabs
Recent FDA communications have highlighted concerns regarding Bedinvetmab (Librela), including reports of neurological signs and potential risks of rapidly progressive osteoarthritis due to the role of NGF in bone and cartilage homeostasis.
Glucocorticoids (GCs)
Glucocorticoids are powerful anti-inflammatory and immunosuppressive agents that work much higher up in the inflammatory cascade than NSAIDs. While NSAIDs inhibit COX, Glucocorticoids inhibit Phospholipase A2 (PLA2), which prevents the release of arachidonic acid from the cell membrane entirely.
Mechanisms of Action
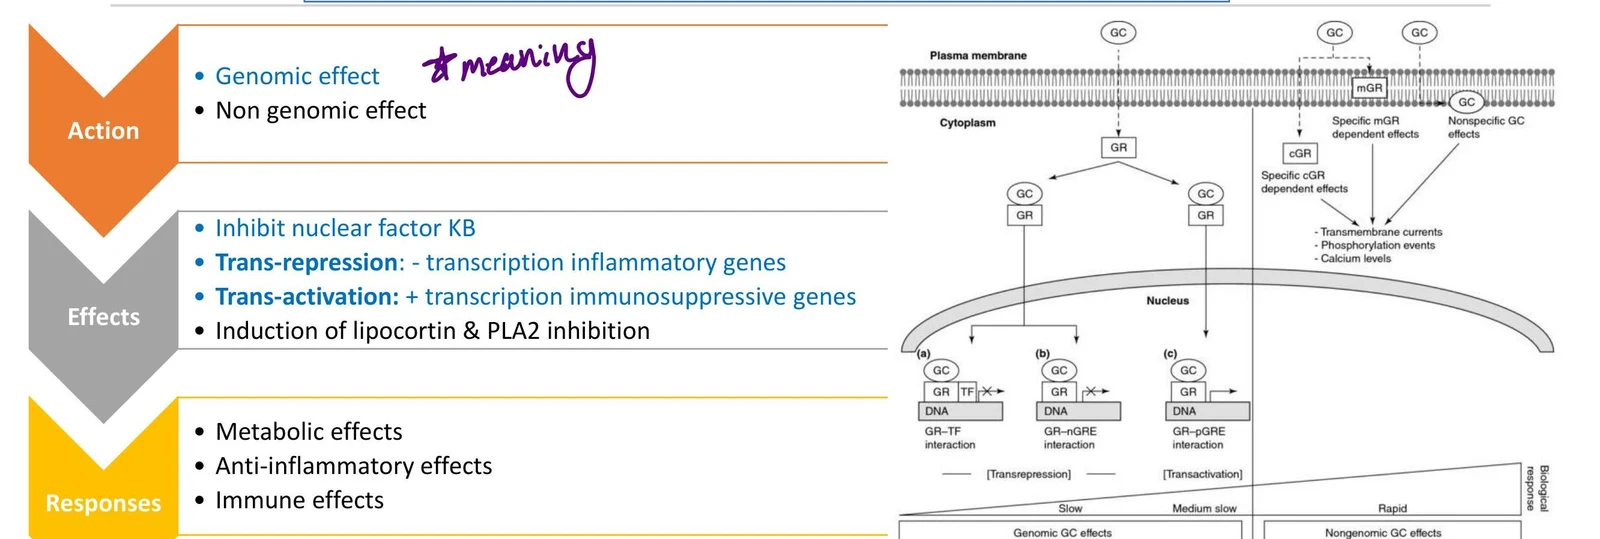
GCs work through both genomic and non-genomic pathways:
Genomic: GCs diffuse into cells and bind to the cytosolic glucocorticoid receptor (GR). The complex then moves to the nucleus to either suppress the transcription of inflammatory genes (transrepression) or activate immunosuppressive genes (transactivation).
Nongenomic: These involve rapid effects on cell membranes and signal transduction pathways.
Diagram illustrating the genomic and non-genomic effects of glucocorticoids (GC) on cellular processes, including their interaction with receptors (GR, mGR, cGR) and influence on gene transcription and biological responses.
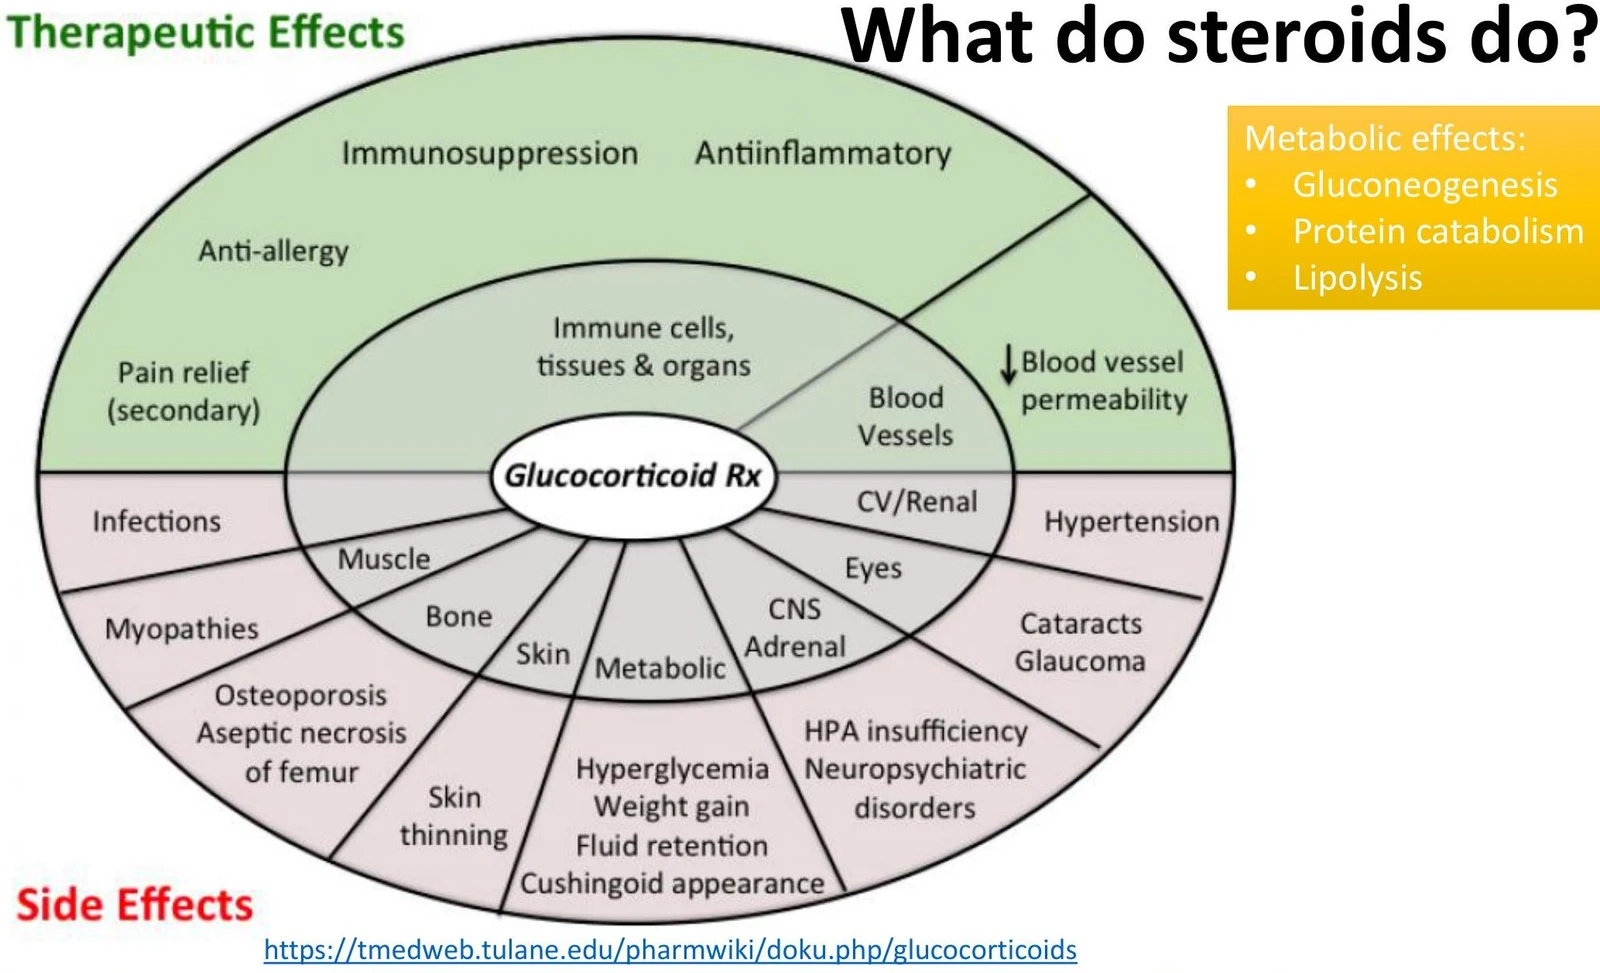
Metabolic and Adverse Effects
Because GCs affect many physiological processes, they have significant side effects:
Metabolic: They increase gluconeogenesis (raising blood glucose) and can lead to muscle atrophy and bone loss (osteoporosis).
Endocrine: Long-term use can cause HPAA (hypothalamic-pituitary-adrenal axis) suppression.
Other: Polyuria (increased urination), polyphagia (increased hunger), and increased risk of infection.
This diagram illustrates the therapeutic effects and side effects of glucocorticoids, including their impact on various bodily systems and metabolic processes.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.