An in-depth exploration of the shoulder joint complex, detailing its bones, ligaments, articulations, and physiological movements. Covers the pectoral girdle, sternoclavicular, acromioclavicular, glenohumeral, and scapulothoracic joints, along with their stability, innervation, and blood supply.
The shoulder is not a single joint, but rather a complex of multiple articulations that work in concert to provide the human upper limb with an extraordinary range of motion. This "shoulder joint complex" involves several bones, ligaments, and specialized articulations that allow for everything from heavy lifting to precise, delicate movements. To understand the shoulder, one must look at the interplay between the pectoral girdle, the various synovial joints, and the physiological gliding of the scapula against the thorax.
The Pectoral Girdle
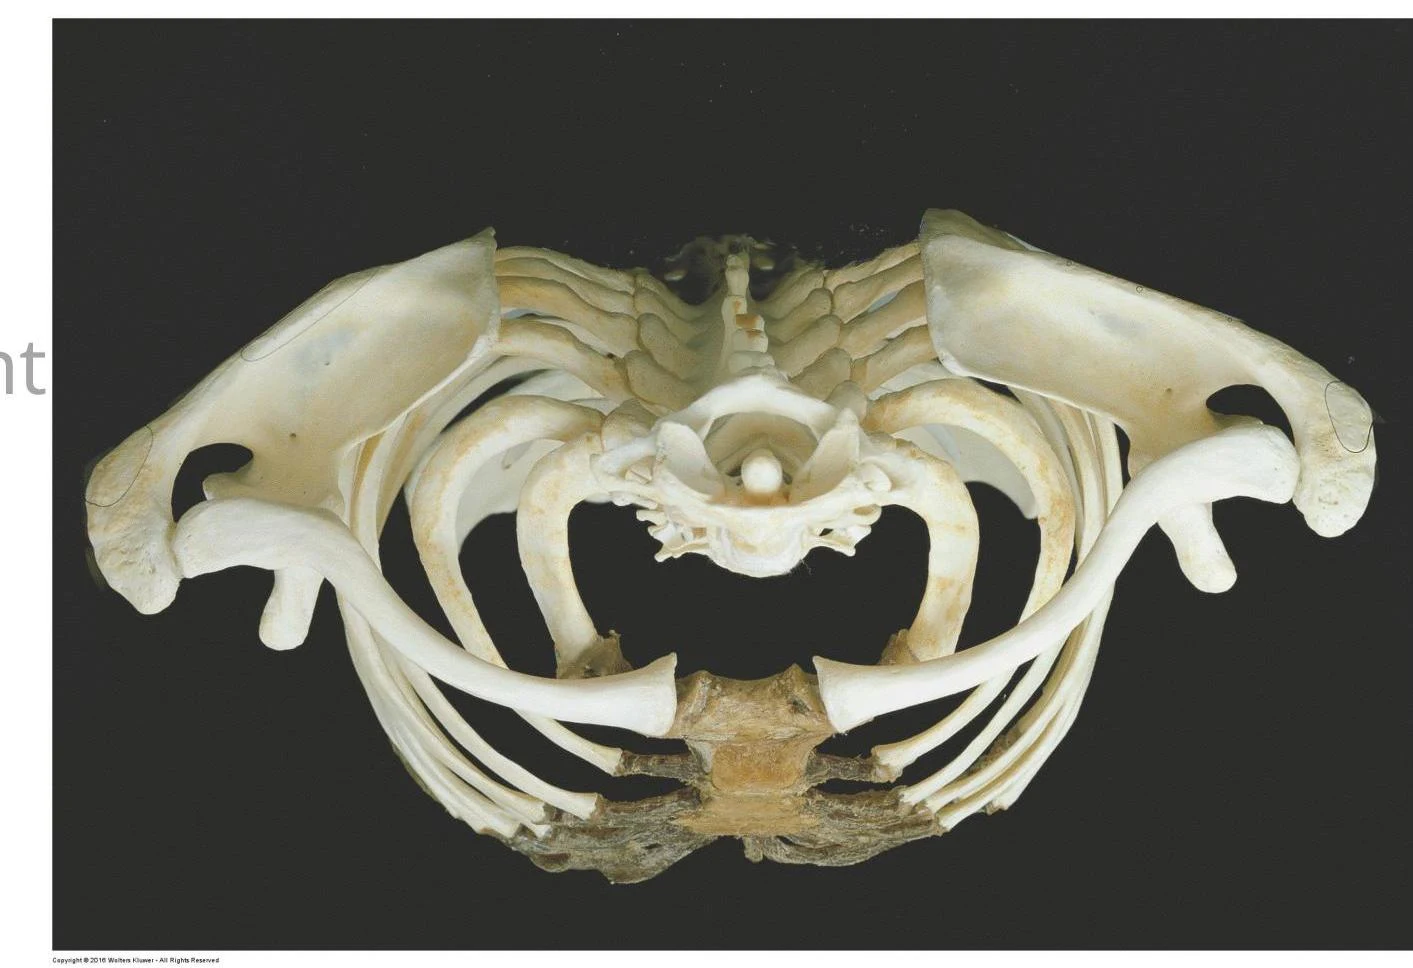
The pectoral girdle serves as the structural foundation for the shoulder complex. It consists of several key articulations that link the upper limb to the axial skeleton. The primary components of this complex include:
Sternoclavicular (SC) Joint
Acromioclavicular (AC) Joint
Glenohumeral (GHJ) Joint
Scapulothoracic (ST) Joint
Anatomical illustration of a rib cage and associated bones.
Sternoclavicular (SC) Joint
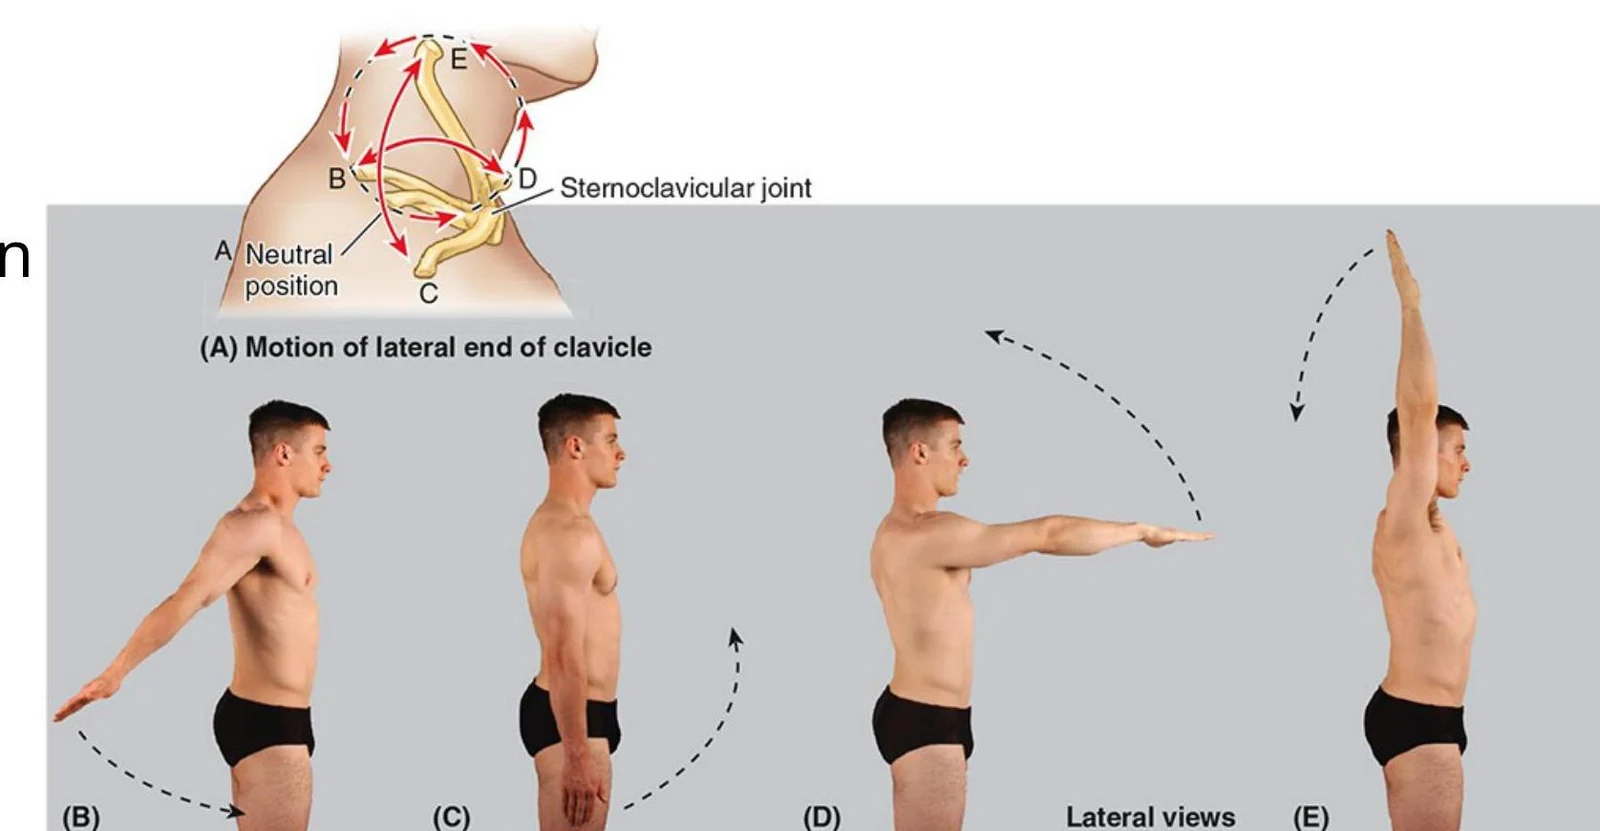
The Sternoclavicular joint is the articulation between the clavicle and the sternum. It is classified as a saddle synovial joint, meaning the articulating surfaces are shaped like two opposing saddles that interlock. This unique shape allows for movement along two planes, specifically elevation/depression, anterior/posterior movement, and rotation.
Diagram illustrating the motion of the lateral end of the clavicle, showing different positions (A-E) and the sternoclavicular joint.
Ligamentous Support and Articular Disc
Several ligaments reinforce this joint to ensure stability:
Anterior and posterior sternoclavicular ligaments: These reinforce the joint capsule on its front and back sides.
Interclavicular ligament: Located between the two clavicles, it strengthens the joint superiorly.
Costoclavicular ligament: This ligament spans between the clavicle and the 1st rib, serving to limit the elevation of the pectoral girdle.
Additionally, the joint contains an articular disc. This disc acts as a shock absorber and divides the joint into two distinct compartments.
Acromioclavicular (AC) Joint
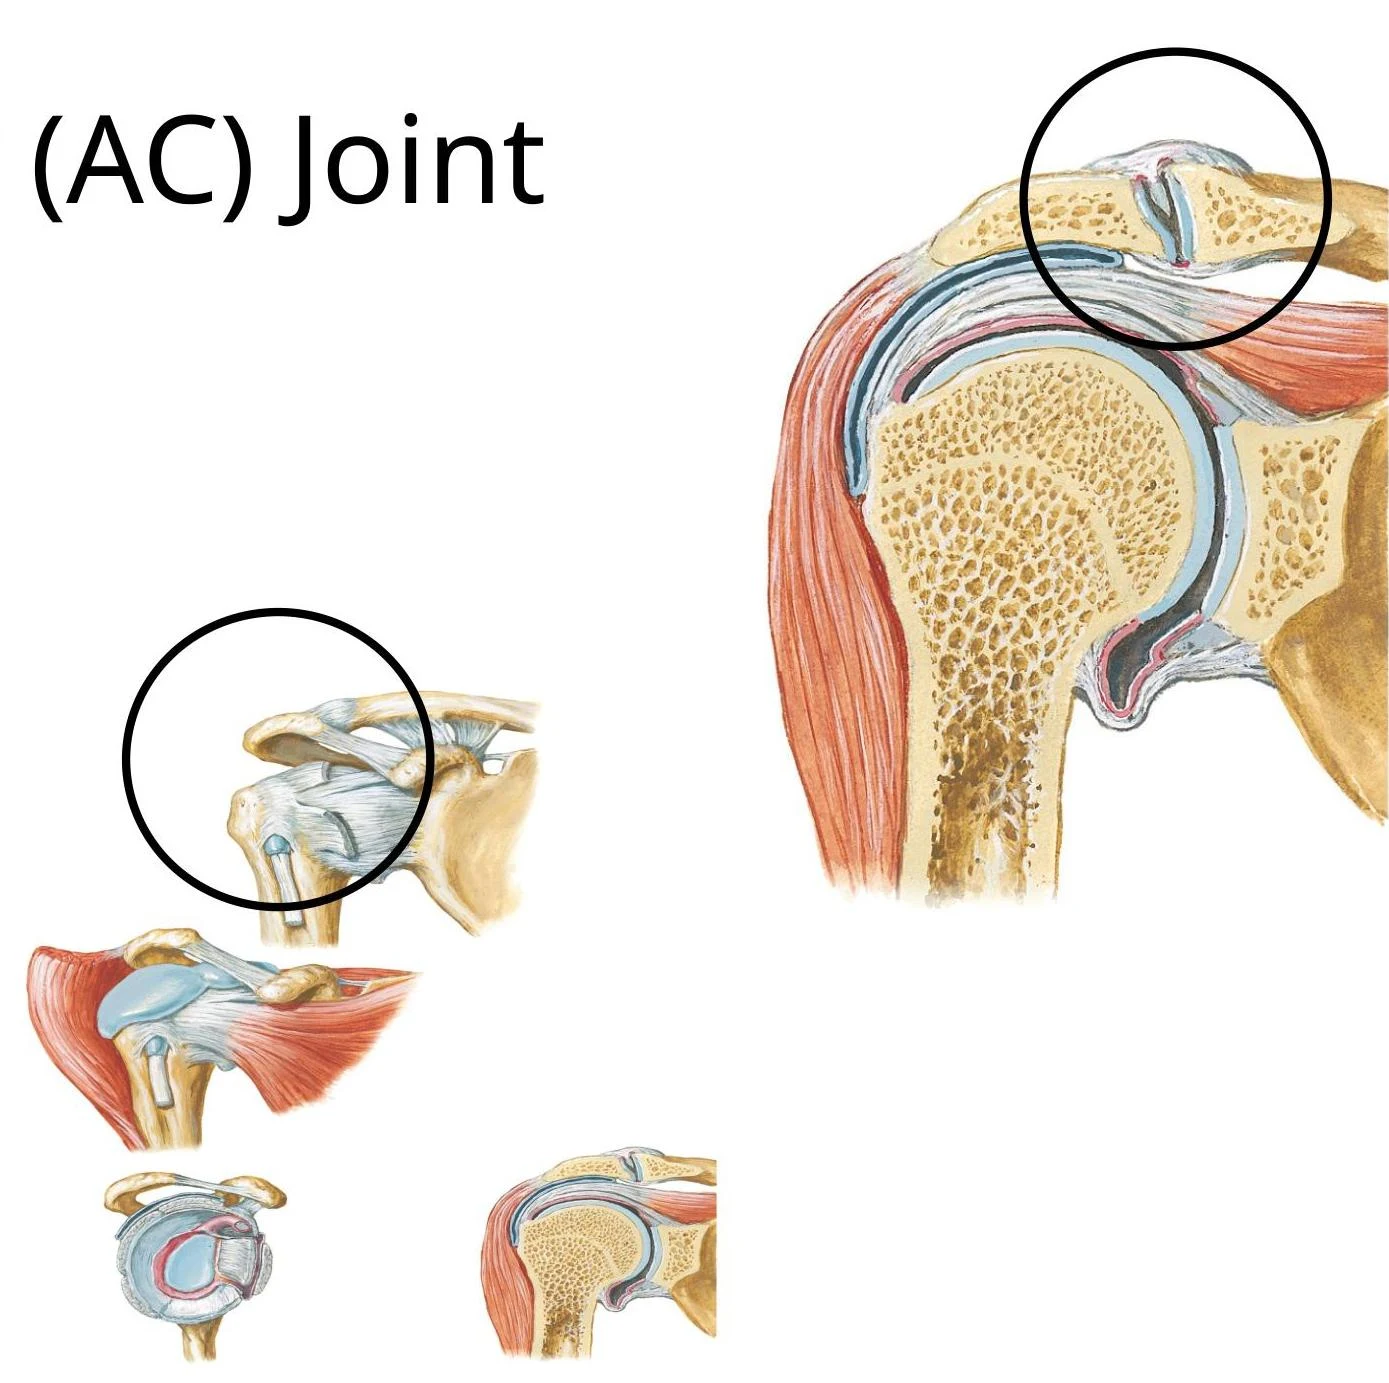
The Acromioclavicular joint connects the acromion of the scapula to the clavicle. Unlike the SC joint, this is a plane synovial joint. Plane joints are typically small, flat surfaces that permit simple gliding or sliding movements.
Anatomical illustration of the acromioclavicular (AC) joint of the shoulder.
Structural Components
The AC joint is stabilized by several key structures:
Articular Disc: An incomplete, wedge-shaped disc located within the joint cavity.
Acromioclavicular Ligament: Spans between the acromion and the clavicle to strengthen the superior aspect of the joint capsule.
Coracoclavicular Ligament: A very strong extrinsic ligament composed of two distinct parts:
Conoid ligament: A vertically oriented, inverted pyramid-shaped ligament spanning from the coracoid process to the inferior clavicle.
Trapezoid ligament: A horizontally oriented ligament attaching at the superior coracoid process and extending posterolaterally to the inferior clavicle.
Clinical Connection: Shoulder Separation
A clavicular dislocation, often called "shoulder separation," frequently results from a hard fall on the shoulder. This injury may involve a rupture of the acromioclavicular ligament alone, or in more severe cases, a rupture of both the acromioclavicular and coracoclavicular ligaments.
Glenohumeral (GHJ) Joint
The Glenohumeral joint is the "true" shoulder joint where the humerus meets the scapula. It is a synovial ball and socket joint, providing the greatest range of motion of any joint in the body. Movements include flexion/extension, abduction/adduction, medial/lateral rotation, and circumduction.
Stability and Anatomy
Because of its wide range of motion, the GHJ requires significant stabilization:
Glenoid Labrum: A fibrocartilaginous ring around the glenoid fossa that deepens the joint socket.
Joint Capsule: A fibrous capsule that contains two apertures: one between the humeral tubercles for the long head of the biceps brachii, and an anterior opening to the subscapular bursa.
Synovial Membrane: Lines the internal surface of the capsule and forms a tubular sheath for the biceps brachii tendon.
Bursae: Fluid-filled sacs like the subscapular bursa and the subacromial/subdeltoid bursa help reduce friction.
Ligamentous Support
The GHJ is reinforced by several ligaments:
Glenohumeral ligaments (Superior, Middle, and Inferior): These are intrinsic ligaments that strengthen the anterior aspect of the joint capsule.
Coracohumeral ligament: An extrinsic ligament spanning from the coracoid process to the greater tubercle, strengthening the joint superiorly.
Transverse humeral ligament: Holds the tendon of the long head of the biceps brachii in the bicipital groove.
Coracoacromial ligament: Spans between the coracoid and acromion to prevent the humerus from displacing superiorly.
Clinical Connection: Dislocations and Stability
The GHJ is reinforced anteriorly, posteriorly, and superiorly by the rotator cuff tendons, the acromion, and the coracoid process. However, it is weakest inferiorly. Consequently, almost all dislocations are inferior. An anterior dislocation is the most common type.
Clinical Connection: Frozen ShoulderAdhesive Capsulitis (Frozen Shoulder) involves inflammation that leads to adhesive fibrosis between the joint capsule, rotator cuff, subacromial bursa, and deltoid. This results in a decreased range of motion, particularly in abduction.
Scapulothoracic (ST) Joint
The Scapulothoracic "joint" is unique because it is not a true skeletal articulation. Instead, it is a physiological joint. It occurs as the scapula glides over the thorax, facilitated by the contact between the subscapularis muscle (on the scapula) and the serratus anterior muscle (on the thorax).
This joint allows for essential movements including elevation/depression, protraction/retraction, and upward/downward rotation. These movements are coordinated with the glenohumeral joint in a pattern known as scapulohumeral rhythm.
Innervation and Blood Supply
Innervation
Joints are typically supplied by branches of the nerves that innervate the muscles acting upon them, but superficial joints also receive cutaneous innervation:
SC Joint: Medial supraclavicular nerve (C3, C4) and the nerve to the subclavius (C5, C6).
AC Joint: Lateral supraclavicular nerve (C3, C4), lateral pectoral nerve (C5-C7), and the axillary nerve (C5, C6).
GHJ: Lateral pectoral nerve (C5-C7), axillary nerve (C5, C6), and the suprascapular nerve (C5-C6).
Blood Supply
The vascular supply to these joints is provided by several key arteries:
SC Joint: Internal thoracic and suprascapular arteries.
AC Joint: Suprascapular and thoracoacromial arteries.
GHJ: Anterior and posterior circumflex humeral arteries, and the suprascapular artery.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.