A detailed anatomical exploration of the pelvis and perineum, covering their bony structures, muscular divisions, fascial layers, neurovascular supply, and clinical significance.
The pelvis and perineum represent a complex anatomical region that serves as the structural foundation for the lower abdomen, the pelvic organs, and the external genitalia. Understanding this region requires a layered approach, moving from the bony framework of the pelvic ring to the intricate muscular and fascial divisions of the perineum. This article explores the structural organization, neurovascular supply, and clinical significance of these regions.
The Bony Pelvis and Pelvic Diaphragm
The bony pelvis is a ring-like structure composed of the two hip bones, the sacrum, and the coccyx. It is divided into two parts by the pelvic inlet (pelvic brim): the greater (false) pelvis, which lies superior to the brim and is bounded by the abdominal wall, and the lesser (true) pelvis, which lies inferior to the brim and contains the pelvic organs.
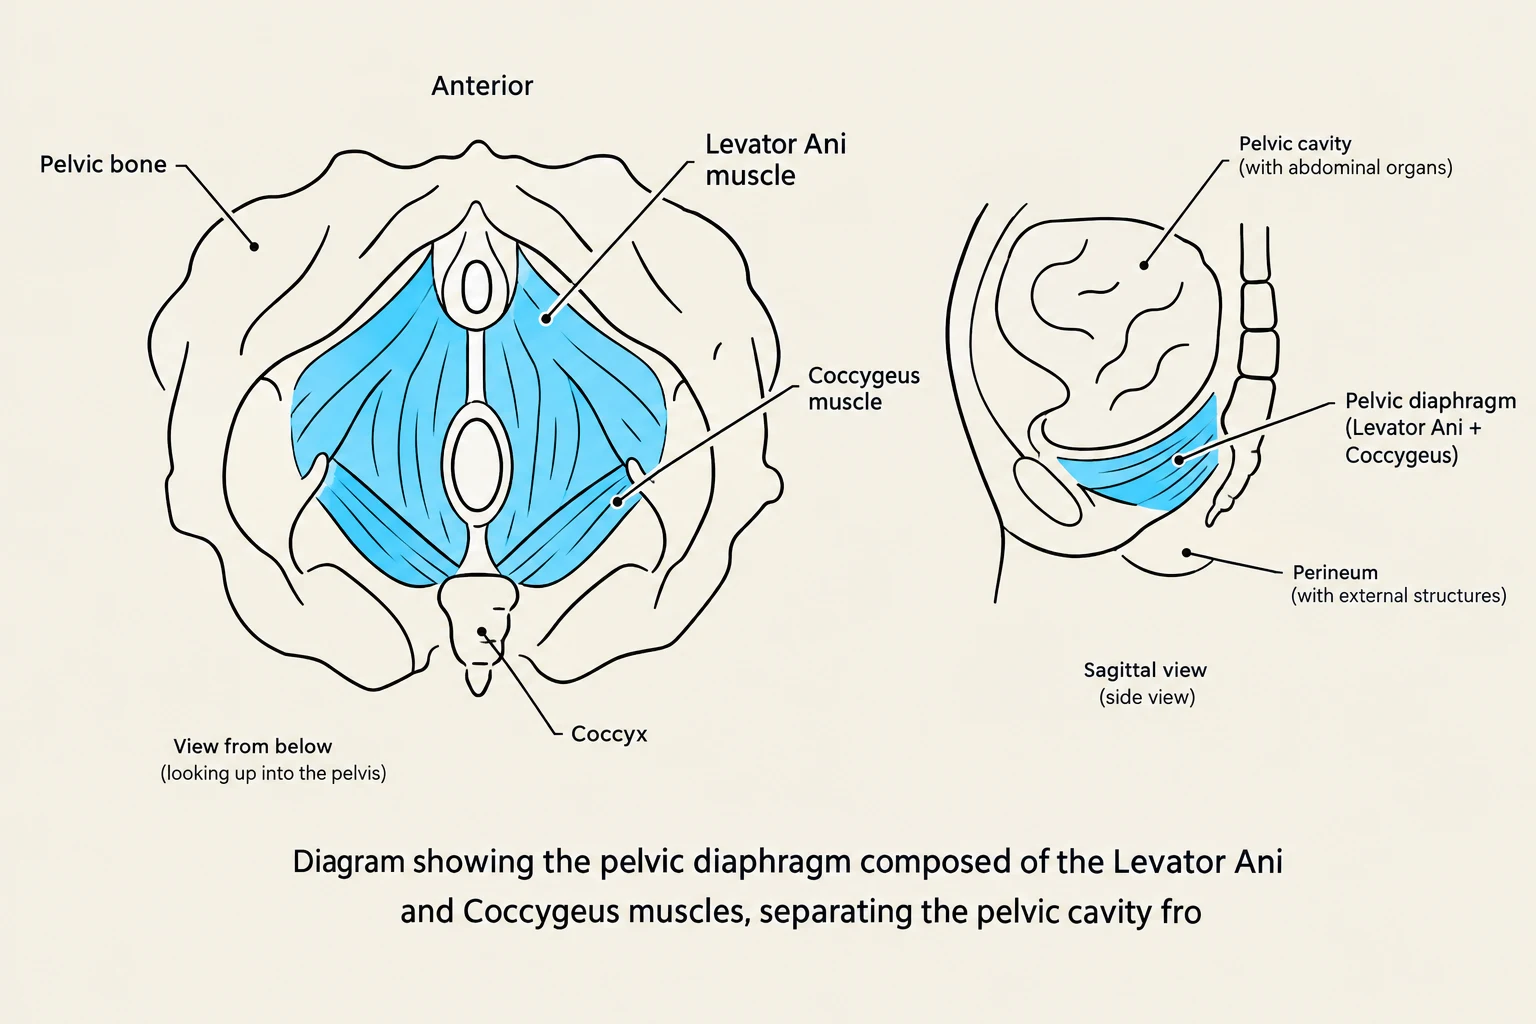
The floor of the pelvic cavity is closed by the pelvic diaphragm, a muscular partition that separates the pelvic cavity from the perineum. This diaphragm is composed of two primary muscles:
Levator Ani: The larger, anterior component, which includes the puborectalis, pubococcygeus, and iliococcygeus muscles. The puborectalis is particularly important as it forms a sling around the rectum, creating the anorectal angle necessary for fecal continence.
Coccygeus: The more posterior component, which originates from the ischial spine and inserts into the coccyx.
Diagram showing the pelvic diaphragm composed of the Levator Ani and Coccygeus muscles, separating the pelvic cavity from the perineum.
Clinical Note: Weakness in the puborectalis muscle can lead to rectal incontinence because the anatomical angulation required to maintain continence is lost.
The Perineum: Subdivisions and Fascial Layers
The perineum is a diamond-shaped area located inferior to the pelvic outlet. It is bounded anteriorly by the pubic symphysis, posteriorly by the coccyx, and laterally by the ischial tuberosities. An imaginary transverse line connecting the two ischial tuberosities divides the perineum into two triangles:
Urogenital Triangle: The anterior portion containing the external genitalia.
Anal Triangle: The posterior portion containing the anal canal and the ischiorectal fossae.
The perineum is organized into distinct layers and pouches. From superficial to deep, the layers consist of the skin, a fatty layer of superficial fascia, Colles’ fascia (the deep membranous layer of the superficial fascia), the perineal membrane, and finally the deep perineal pouch.
The Perineal Membrane and Pouches
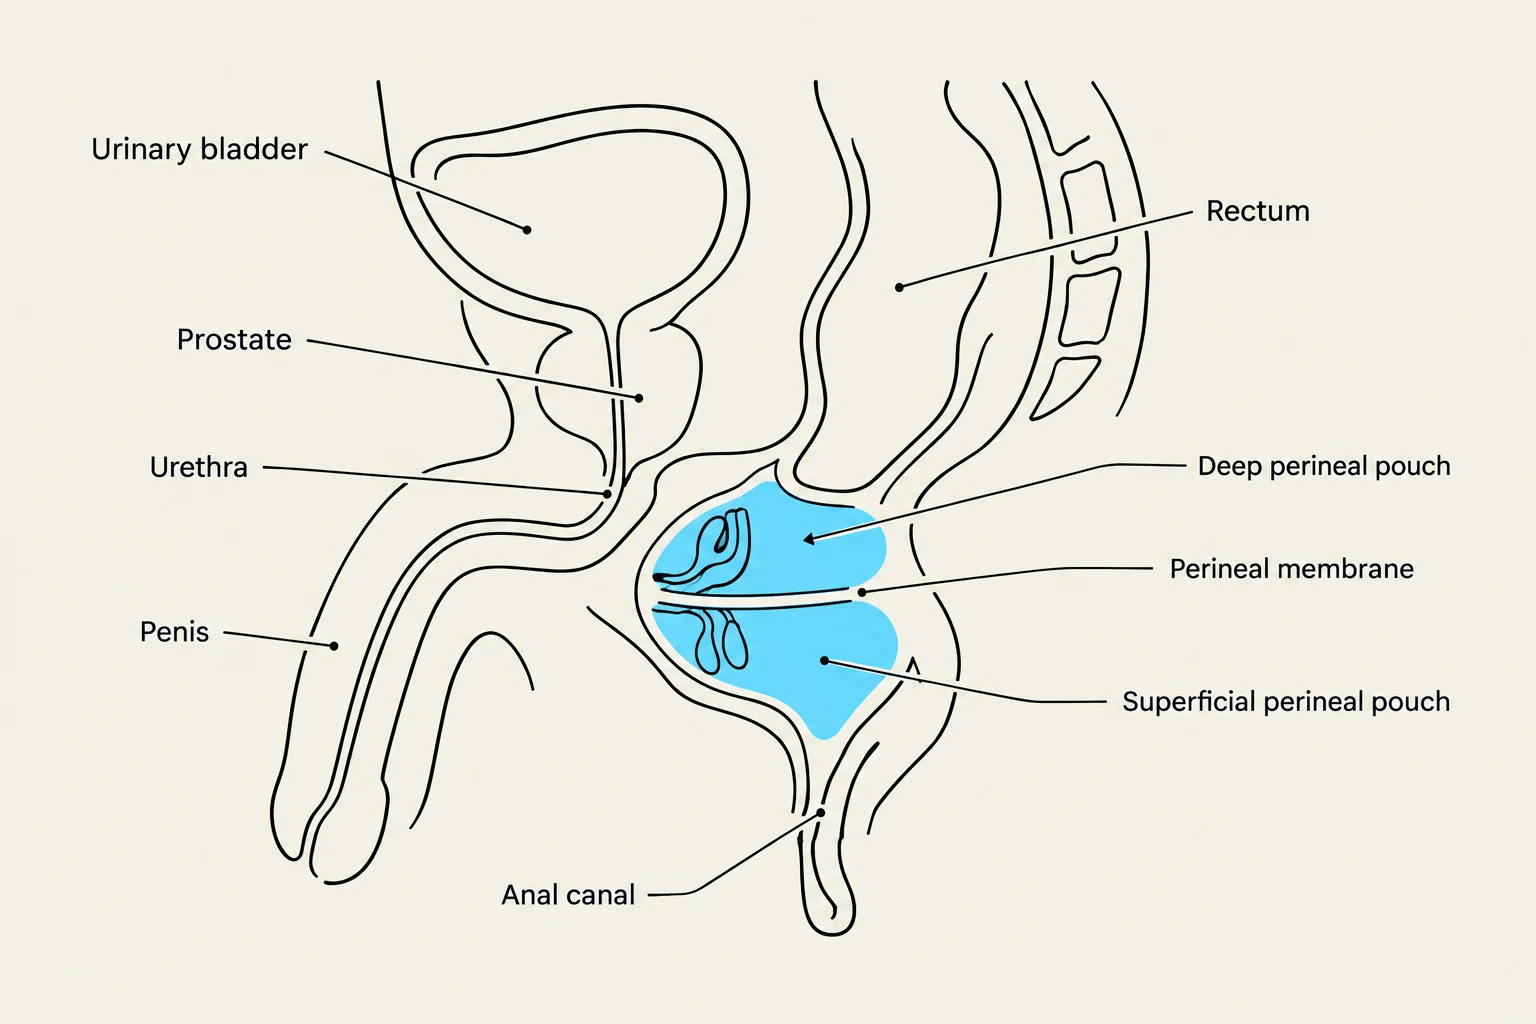
The perineal membrane acts as a critical structural divider. It serves as the roof of the superficial perineal pouch and the floor of the deep perineal pouch.
Superficial Perineal Pouch: Located between the Colles’ fascia and the perineal membrane. In males, it contains the bulb and crura of the penis; in females, it contains the bulbs of the vestibule and crura of the clitoris. Common muscles here include the ischiocavernosus and bulbospongiosus.
Deep Perineal Pouch: Located superior to the perineal membrane. It contains the membranous urethra (in males), the vagina (in females), and the muscles of the urogenital (UG) diaphragm, such as the sphincter urethrae and the deep transverse perineal muscle.
This diagram illustrates the anatomy of the male pelvic region, showing the urinary bladder, prostate, urethra, penis, anal canal, and rectum, along with the deep, perineal, and superficial perineal pouches.
The Anal Triangle and Ischiorectal Fossa
The anal triangle contains the anal orifice and is flanked on either side by the ischiorectal (ischio-anal) fossae. These fossae are wedge-shaped spaces filled with an ischiorectal pad of fat, which helps keep the anal canal closed.
The lateral wall of the fossa is formed by the obturator internus muscle and its fascia, while the medial wall is formed by the levator ani and the external anal sphincter.
Clinical Anatomy: Ischiorectal Abscesses
An abscess in this space is known as an ischiorectal sinus. If the pus opens only at the perianal skin, it is a simple abscess; if it opens both internally (rectum) and externally (skin), it is a fistula-in-ano. When performing surgical drainage, clinicians must be careful to avoid the pudendal canal on the lateral wall to prevent nerve damage.
Neurovascular Supply and Lymphatics
The Pudendal Nerve and Canal
The pudendal nerve (S2, S3, S4) is the principal nerve of the perineum. It travels through the pudendal canal (Alcock’s canal), a tunnel located in the lateral wall of the ischiorectal fossa. The nerve gives off several vital branches:
Inferior rectal nerve: Supplies the external anal sphincter and perianal skin.
Perineal nerve: Supplies the muscles of the urogenital triangle.
Dorsal nerve of the penis/clitoris: Provides sensation to the glans and prepuce.
Blood Vessels and Lymphatics
The internal pudendal artery, a branch of the internal iliac artery, provides the primary blood supply to the perineum. It gives rise to the inferior rectal, perineal, and various penile/clitoral arteries.
Lymphatic drainage follows specific patterns:
The superficial perineum generally drains to the superficial inguinal nodes.
The deep perineal pouch and upper vagina drain to the internal iliac nodes.
The Perineal Body and Clinical Applications
The perineal body (centrum tendinum) is a central fibromuscular structure located between the anus and the urogenital structures. It serves as a vital anchor for the pelvic floor, receiving attachments from various perineal muscles.
Clinical Correlates
Episiotomy: During childbirth, a surgical incision (episiotomy) may be made in the perineum to facilitate delivery. To minimize damage to the perineal body and the pelvic floor, a posterolateral vaginal wall incision is often preferred over a midline incision.
Urethral Rupture: If the urethra is ruptured, urine can extravasate into the superficial perineal pouch. Because Colles’ fascia is continuous with Scarpa’s fascia of the abdominal wall, urine may spread into the scrotum, penis, and anterior abdominal wall.
Pudendal Nerve Block: This is a common local anesthesia procedure used during labor (often called a "saddle block") to provide analgesia for vaginal deliveries.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.