Anatomy and Sonographic Assessment of the Portal Venous System and Spleen
This article provides a comprehensive overview of the anatomy, physiology, and sonographic appearance of the portal venous system and the spleen, essential for diagnostic imaging.
The portal venous system and the spleen are integral components of the abdominal vascular and reticuloendothelial systems. Understanding their anatomical relationships, physiological roles, and distinct sonographic appearances is essential for accurate diagnostic imaging. This article explores the complex network of vessels that supply the liver with nutrients and the spleen's vital role in blood filtration and immune defense.
The Portal Venous System: Anatomy and Physiology
The portal venous system is a specialized vascular network designed to transport blood from the gastrointestinal (GI) tract, spleen, gallbladder, and pancreas directly to the liver. This blood is rich in nutrients absorbed during digestion—such as glucose, amino acids, and fatty acids—but also contains toxins, drugs, and metabolic byproducts like bilirubin from red blood cell breakdown.
Once this blood reaches the liver, the hepatocytes (liver cells) perform critical functions: metabolizing nutrients, detoxifying substances, producing plasma proteins (like albumin), and converting ammonia into urea for excretion. Interestingly, while the portal system provides up to 80% of the liver's required oxygenated blood, it is only partially oxygenated; the liver compensates through the massive volume of blood delivered. This blood eventually transfers to the hepatic veins via sinusoids (small capillary-like spaces) and drains into the inferior vena cava (IVC).
Major Tributaries and the Main Portal Vein
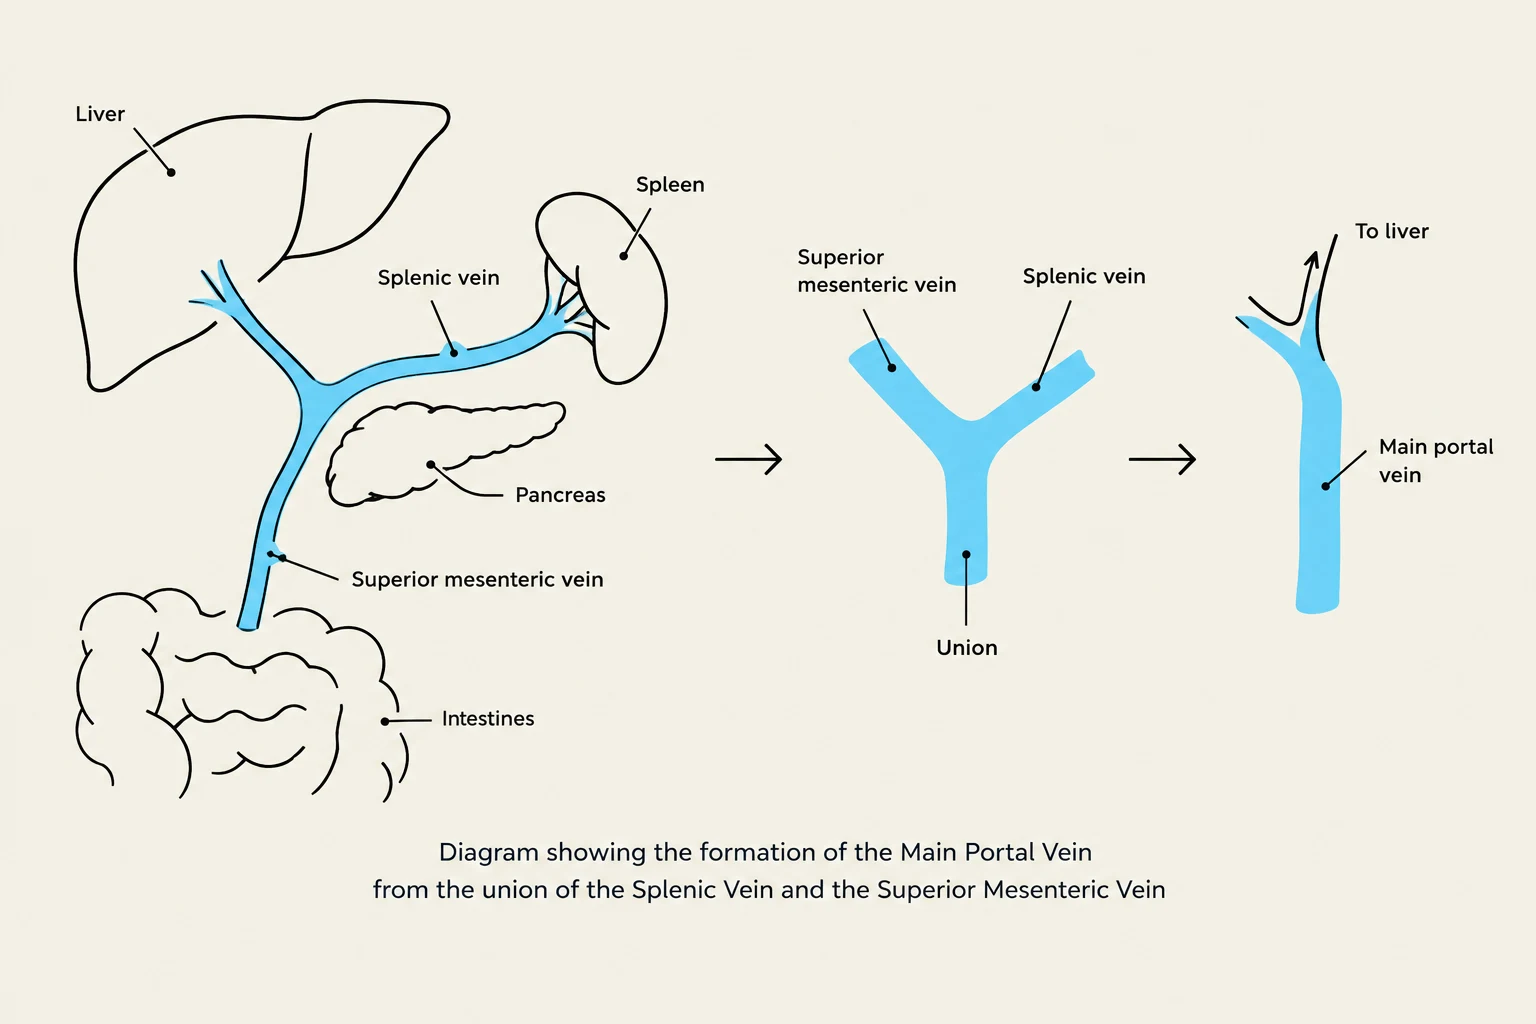
The Main Portal Vein (MPV) is formed at the level of the L2 vertebra by the union of the splenic vein and the superior mesenteric vein (SMV). It courses posterior to the duodenum and enters the porta hepatis at a rightward, cephalic, and posterior approach.
The Splenic Vein
The splenic vein is a primary tributary formed by several smaller veins at the splenic hilum, including the short gastric and left gastroepiploic veins. It drains blood from the stomach, spleen, and pancreas, traveling posterior to the pancreas before joining the SMV.
The Superior Mesenteric Vein (SMV)
The SMV drains the small intestines as well as the ascending and transverse colon. It courses parallel to the superior mesenteric artery (SMA) and joins the splenic vein just posterior to the pancreas neck.
The Inferior Mesenteric Vein (IMV)
The IMV drains the descending colon and rectum. It typically joins the splenic vein, though this can vary anatomically. Because it lies inferior to the splenic vein, it can sometimes be confused with the splenic vein during sonographic assessment, which is a critical distinction in cases of suspected splenic vein thrombosis.
Diagram illustrating the formation of the Main Portal Vein from the union of the Splenic Vein and the Superior Mesenteric Vein, showing the liver, spleen, pancreas, and intestines.
Sonographic Appearance of Portal Vessels
When performing a sonographic assessment, the sonographer must evaluate the size, presence of flow, direction of flow, and the vessel lumen to rule out thrombus.
Main Portal Vein (MPV)
2D Gray Scale: Appears as a tubular anechoic structure. A key identifying feature is the presence of prominent hyperechoic walls, caused by the collagenous sheath surrounding the portal vein, hepatic artery, and bile duct.
Size: The length is typically 5–7 cm. The anteroposterior (AP) diameter is generally considered normal, though some clinicians suggest values exceeding 13–16 mm may indicate dilation.
Doppler: Flow should be hepatopetal (moving toward the liver), appearing above the baseline on color Doppler. The spectral waveform should be phasic with a normal velocity of 20–40 cm/s.
Portal Branches: Left and Right
At the porta hepatis, the MPV divides into the left and right portal veins:
Left Portal Vein: Positioned more anteriorly and cranially; it divides the medial and lateral segments of the left lobe.
Right Portal Vein: Larger than the left branch and positioned more posteriorly; it further divides into anterior and posterior branches.
Exam Tip: It is not possible to assess the main portal vein, splenic vein, and superior mesenteric vein in a single imaging plane. You must adjust your transducer to capture each vessel specifically.
Anatomy and Physiology of the Spleen
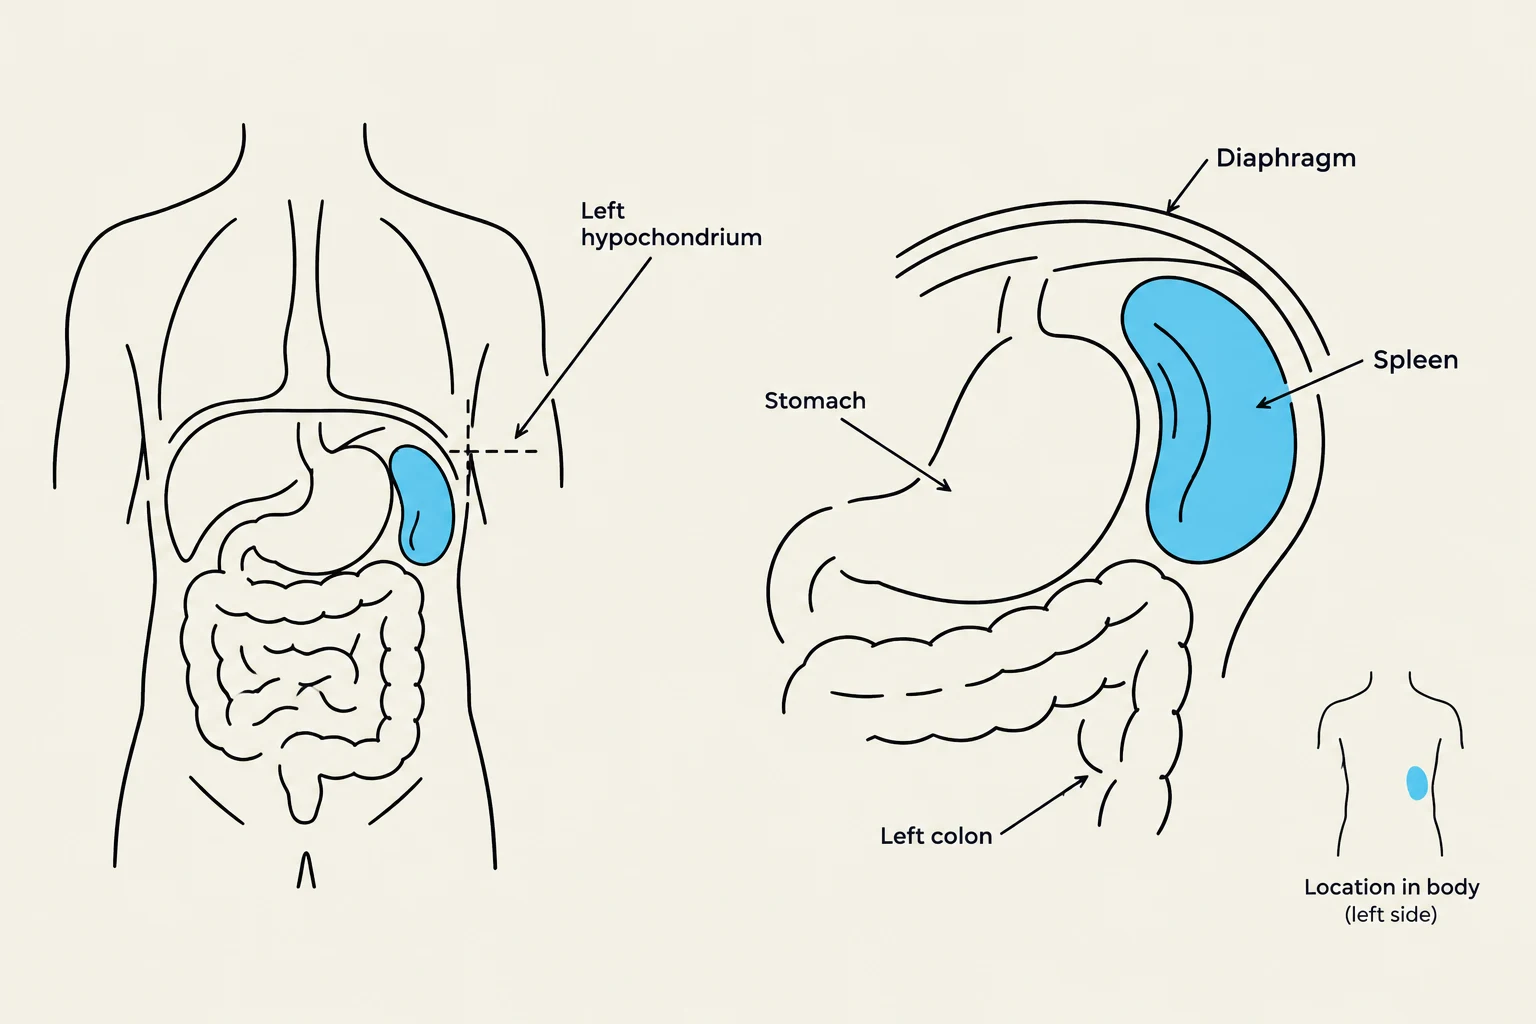
The spleen is a soft, intraperitoneal organ located in the posterior left hypochondrium, typically positioned along the 10th rib. It functions as a key organ of the reticuloendothelial system, providing immune defense through the production of lymphocytes, plasma cells, and antibodies.
Internal Structure and Function
The splenic lobules consist of two types of "pulp":
White Pulp: Contains splenic nodules rich in lymphocytes.
Red Pulp: Fills the spaces between lobules with red blood cells and a large number of macrophages.
The red pulp is responsible for "culling" (removing old or damaged erythrocytes) and "pitting" (removing inclusions from cells). Because the spleen is an elastic organ that can fill with blood (containing 20–30 ml of erythrocytes), it is highly susceptible to significant hemorrhage during trauma.
Splenic Ligaments and Relational Anatomy
The spleen is held in place by several ligaments:
Splenorenal Ligament: Extends between the splenic hilum and the anterior left kidney; it contains the splenic artery and vein, as well as the tail of the pancreas.
Gastrosplenic Ligament: A double layer of peritoneum connecting the gastric fundus to the splenic hilum, containing the short gastric and left gastroepiploic vessels.
Diagram showing the location of the spleen in the human body, adjacent to the stomach and diaphragm.
Sonographic Assessment of the Spleen
Appearance and Measurement
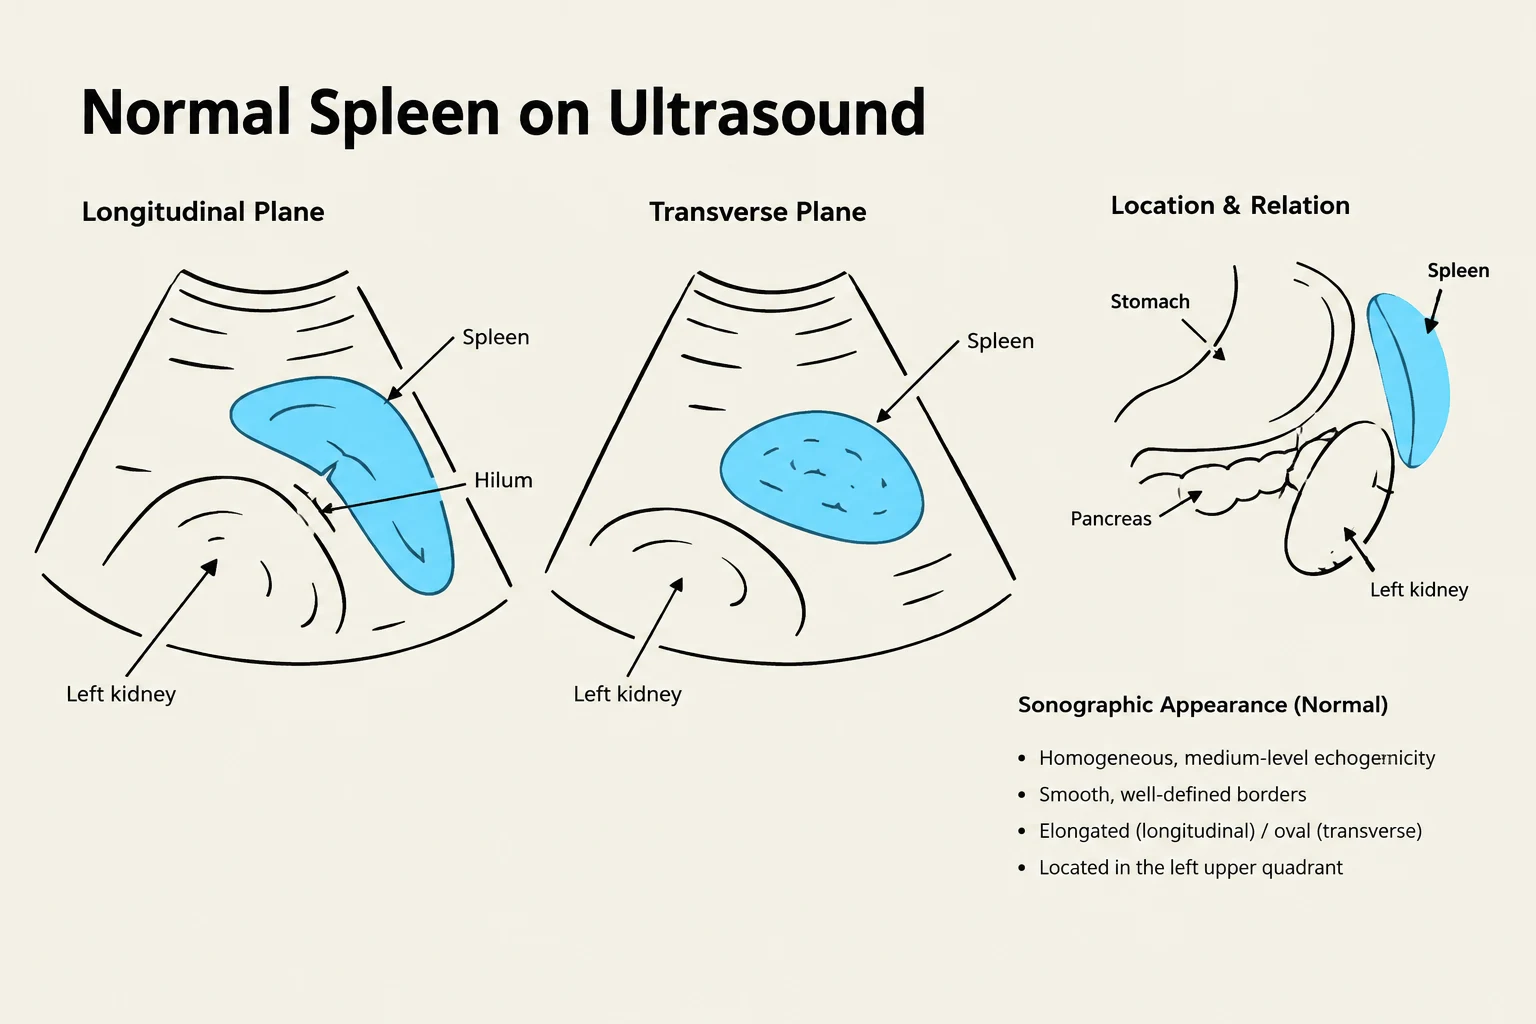
2D Characteristics: The spleen should have a smooth contour and a homogenous echotexture that is mid-to-low level echo pattern, typically slightly more echogenic than the liver.
Shape: Often described as ovoid, triangular, or shaped like an "orange slice".
Measurements: The standard measurement is the length in the longitudinal plane. To calculate the total volume, the following formula is used:
Volume (cm3)=0.523⋅length⋅AP dimension⋅width
Technical Considerations and Variants
Scanning the spleen can be challenging due to its superior location or interference from stomach gas. Sonographers may need to use intercostal scanning or ask the patient to raise their left arm to elongate the rib spaces.
Anatomical Variants to Recognize:
Accessory Spleen (Splenunculus): Found in ~30% of patients; these are small, homogenous masses near the hilum that can be mistaken for lymph nodes.
Wandering Spleen: An embryologic anomaly where a lack of supporting ligaments allows the spleen to move from its typical position, increasing the risk of torsion.
Polysplenia: The presence of multiple small spleens.
This illustration shows the normal spleen in longitudinal and transverse ultrasound planes, its location relative to other organs like the stomach, pancreas, and left kidney, and its typical sonographic appearance.
Clinical Correlation
When imaging these structures, clinicians often look for signs of underlying pathology. Common indications for assessing the portal system and spleen include chronic liver disease, cirrhosis, portal hypertension, and splenomegaly.
In cases of suspected infection or hematologic issues, laboratory values such as leukocyte counts, hemoglobin, and platelet levels are critical for correlation. For example, a patient with splenomegaly and abnormal lab values might be evaluated for splenic sequestration or issues related to the reticuloendothelial system.
Clinical Note: Always assess the left subphrenic and subsplenic (splenorenal) spaces for the presence of free fluid, which could indicate trauma or other acute conditions.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.