The heart is a pyramid-shaped muscular organ situated within the middle mediastinum. It serves as the central pump of the cardiovascular system, facilitating the continuous circulation of blood to provide oxygen and nutrients to tissues while removing metabolic waste. Understanding the heart requires a multi-faceted approach, looking at its physical chambers, the electrical signals that drive its rhythm, the specialized vessels that nourish the muscle itself, and the clinical implications when these systems fail.
Cardiac Anatomy and Blood Flow
The heart is divided into four distinct chambers: the right atrium, right ventricle, left atrium, and left ventricle. These chambers work in a highly coordinated sequence to manage two separate circuits: the pulmonary circulation (to the lungs) and the systemic circulation (to the rest of the body).
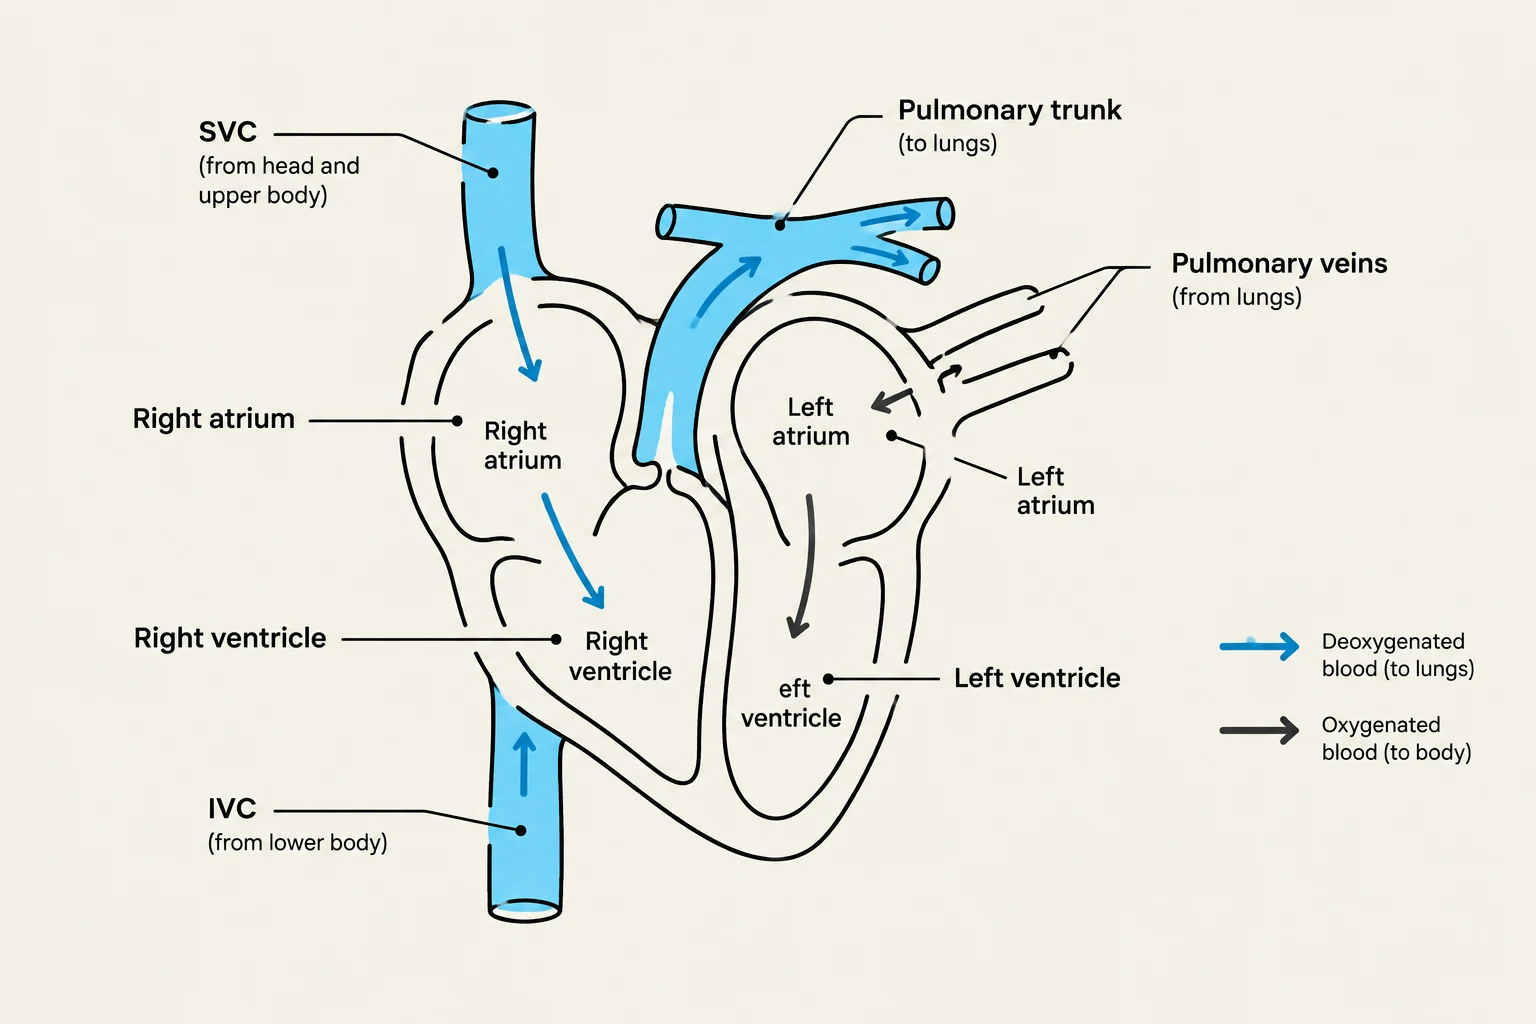
Deoxygenated blood returns from the body via the superior vena cava (SVC) and inferior vena cava (IVC), entering the right atrium. From there, it passes into the right ventricle, which pumps the blood through the pulmonary trunk to the lungs. Once oxygenated, the blood returns via the pulmonary veins to the left atrium, moves into the left ventricle, and is finally ejected into the aorta for systemic distribution.
The left ventricle is notably more muscular than the right, reflecting the high pressure required to pump blood throughout the entire systemic circuit.
Diagram illustrating the flow of blood through the four chambers of the heart: the right atrium, right ventricle, left atrium, and left ventricle. It shows the pulmonary trunk carrying deoxygenated blood to the lungs and pulmonary veins returning oxygenated blood from the lungs. The superior vena cava (SVC) and inferior vena cava (IVC) are depicted bringing deoxygenated blood from the body to the right atrium.
The Role of Cardiac Valves
To ensure blood flows in only one direction, the heart utilizes two types of valves that prevent regurgitation (backflow):
Atrioventricular (AV) Valves: These connect the atria to the ventricles. On the right side is the tricuspid valve, and on the left is the mitral (bicuspid) valve. These valves are actively managed by papillary muscles and chordae tendineae (tendinous cords). During ventricular contraction, the papillary muscles contract, pulling the chordae tendineae taut to hold the valve cusps closed.
Semilunar (SL) Valves: The pulmonary and aortic valves are located at the exits of the ventricles. They consist of three cusps that passively prevent blood from flowing back into the ventricles once it has been ejected.
The Cardiac Cycle: Systole and Diastole
The rhythmic contraction and relaxation of the heart is known as the cardiac cycle. This cycle is characterized by two primary phases that produce the distinct "lub-dub" sounds heard during auscultation:
Systole: This is the period of ventricular contraction. As pressure rises in the ventricles, the AV valves close (producing the first heart sound, "lub") and the semilunar valves open to allow blood to exit.
Diastole: This is the period of ventricular relaxation. As ventricular pressure drops, the semilunar valves close (producing the second heart sound, "dub"), and the AV valves open to allow the chambers to refill with blood.
Clinical Note: Auscultation Sites
When listening to the heart, clinicians do not listen directly over the valves. Instead, they listen "downstream" of the flow:
Aortic: Right 2nd intercostal space at the sternal margin.
Pulmonary: Left 2nd intercostal space at the sternal margin.
Tricuspid: Left 5th intercostal space at the sternal margin.
Mitral: Left 5th intercostal space at the midclavicular line.
The Cardiac Conduction System
The heart does not rely on external nerves to initiate every beat; rather, it possesses an intrinsic electrical conduction system that coordinates the contraction of cardiomyocytes.
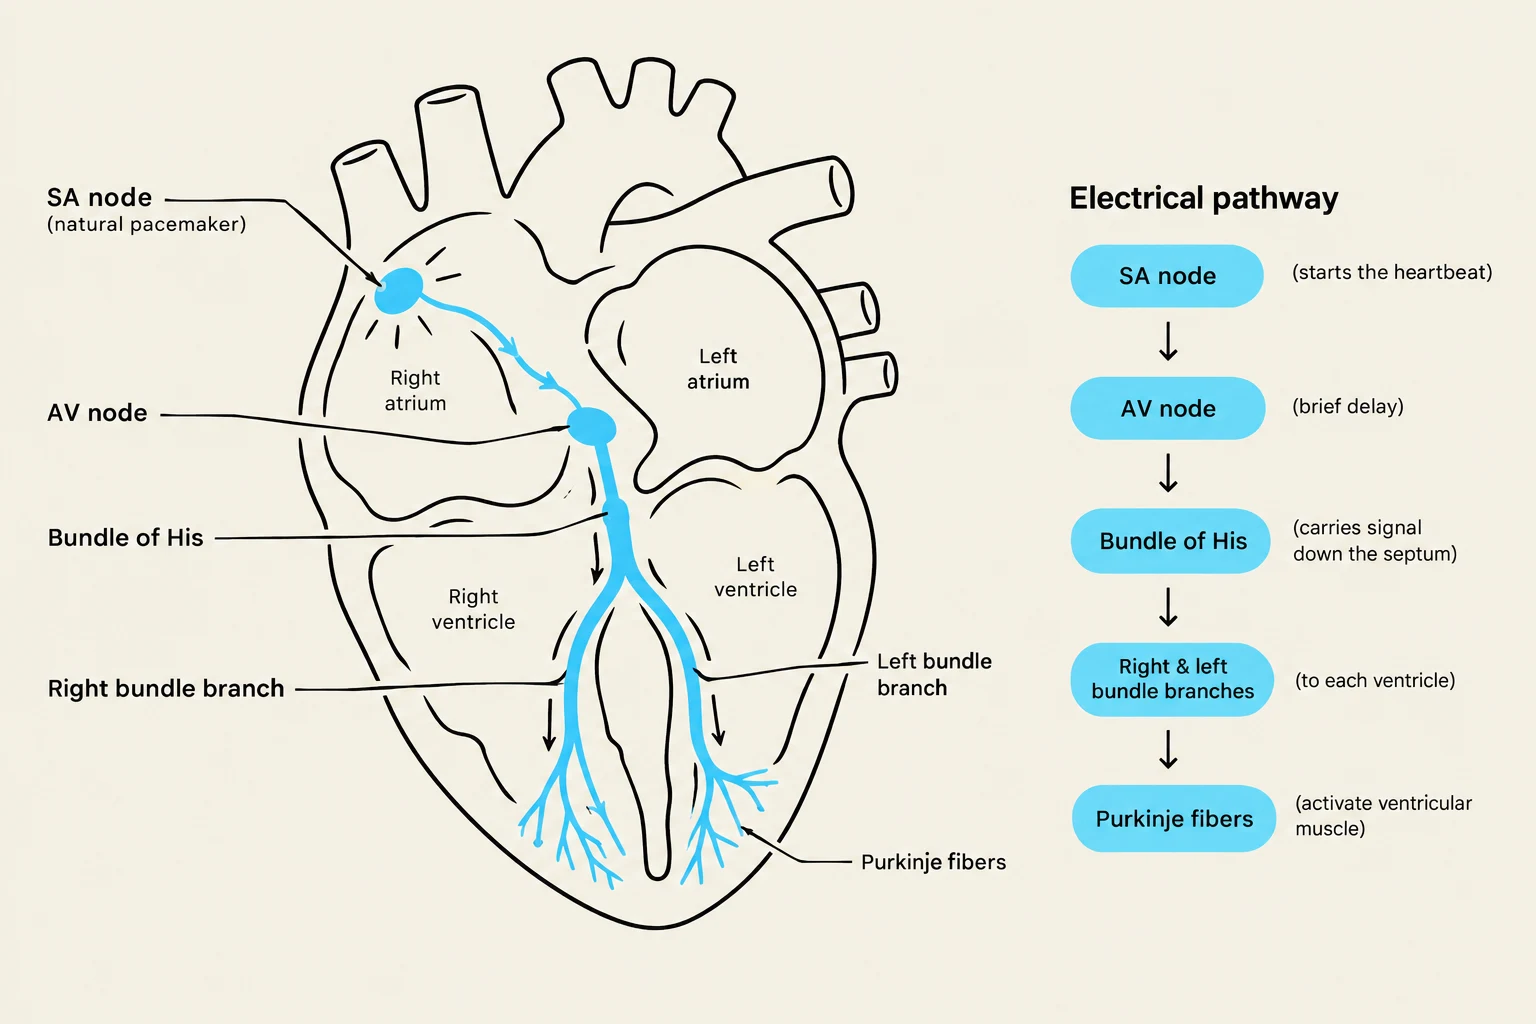
The impulse begins at the sinoatrial (SA) node, often called the pacemaker, which establishes the sinus rhythm. The signal travels to the atrioventricular (AV) node, where it is briefly delayed. This delay is critical because it allows the atria to finish contracting and filling the ventricles before the ventricles begin their own contraction. The impulse then travels through the AV bundle (Bundle of His) and down the bundle branches to the Purkinje fibers. These fibers excite the ventricular cardiomyocytes, causing contraction to begin at the base of the heart and move upward, effectively "squeezing" the blood out toward the great vessels.
Diagram illustrating the electrical pathway of the heart, including the SA node, AV node, Bundle of His, bundle branches, and Purkinje fibers.
Coronary Circulation and Myocardial Health
While the heart pumps blood to the rest of the body, it must also nourish itself. This is achieved through the coronary arteries, which arise from the openings in the aortic sinuses. The two primary branches are the Right Coronary Artery (RCA) and the Left Coronary Artery (LCA). The LCA is particularly vital as it gives rise to the Left Anterior Descending (LAD) artery, often referred to as the "Widow Maker" because it provides the primary blood supply to the ventricles.
Deoxygenated blood from the cardiac tissue is collected by the cardiac veins, which typically converge into a large vessel called the coronary sinus that empties directly into the right atrium.
Clinical Complications: Ischemia and Infarction
When the blood supply to the heart muscle is compromised, several dangerous conditions can arise:
Ischemia: This is the state of inadequate blood supply to a region of the heart, often caused by the narrowing of coronary arteries.
Myocardial Infarction (MI): If an occlusion (blockage) occurs—due to atherosclerosis or a blood clot—the resulting prolonged ischemia leads to an infarct, which is a localized area of dead cardiac tissue. Because cardiomyocytes cannot regenerate, the body replaces the dead tissue with a collagen-based scar.
Hypertrophy: To compensate for the loss of functional tissue, the surviving cardiomyocytes undergo hypertrophy (enlargement). While this helps maintain output initially, it places added strain on the heart and is less efficient over time.
Pulmonary Embolism (PE): While an MI is a problem within the heart muscle, a PE occurs when a blood clot (often from a deep vein thrombosis) travels through the venous system and obstructs a pulmonary artery, blocking blood flow to the lungs.
Exam Tip: Referred Pain
During a myocardial infarction, patients often experience referred pain. This occurs because the visceral afferent (GVA) pain fibers from the heart share spinal cord segments (C8-T5) with the somatic afferent (GSA) fibers from the skin. Consequently, the brain perceives heart pain as coming from the left arm, left shoulder, jaw, neck, or upper abdomen.
Fetal Circulation Remnants
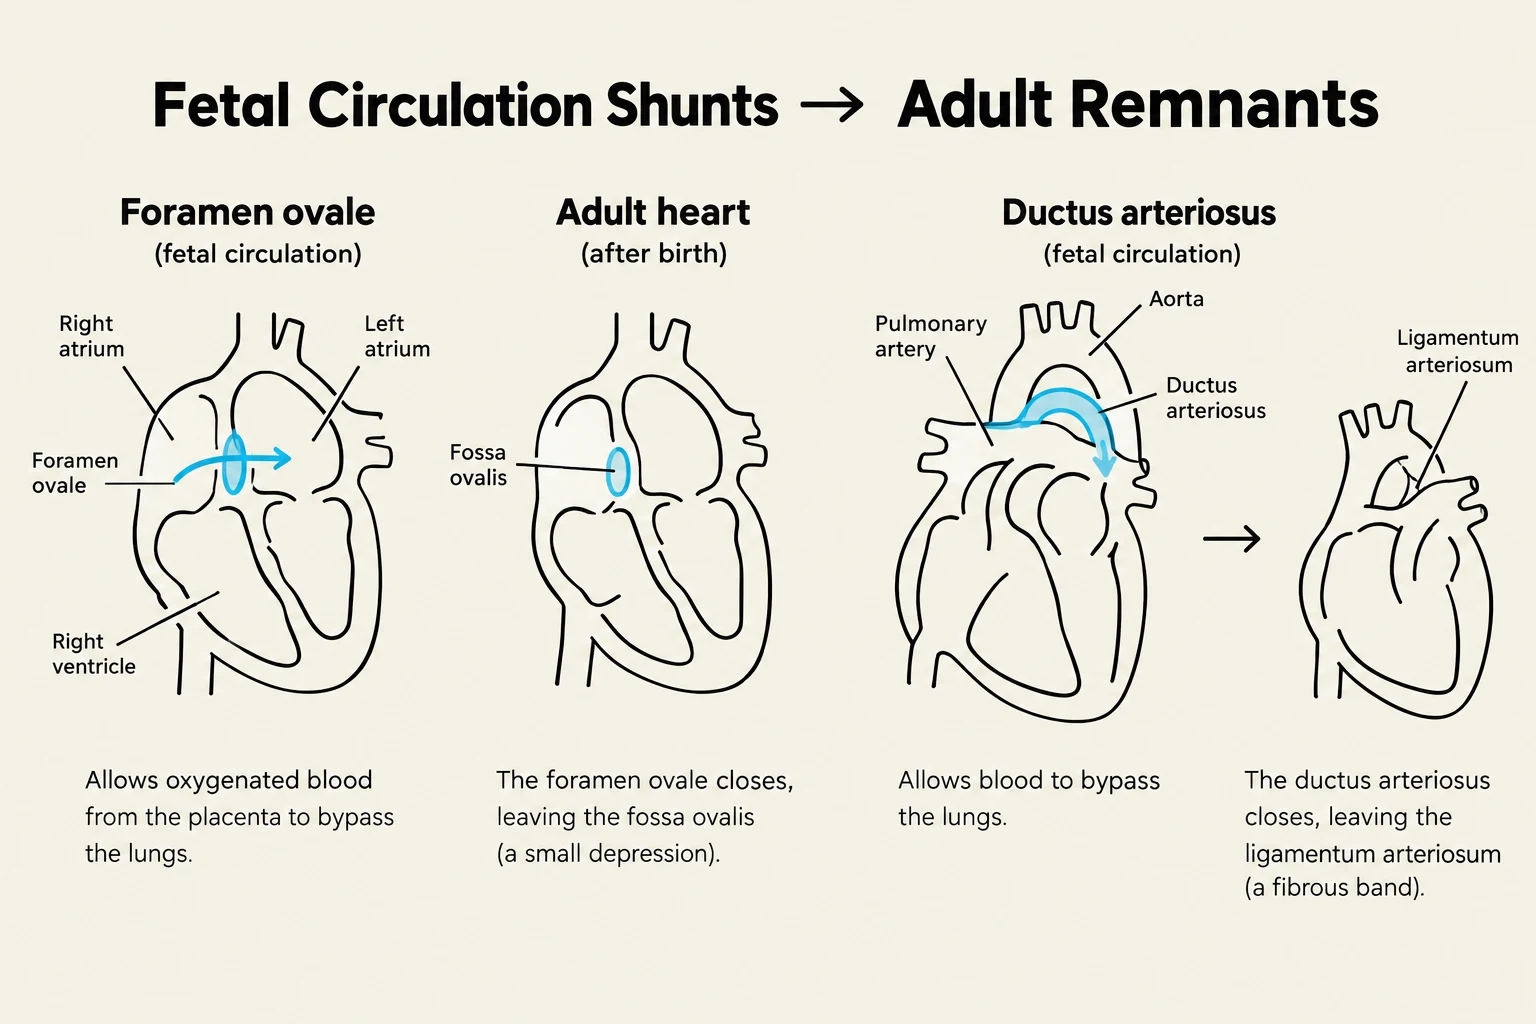
In a developing fetus, the lungs are not used for gas exchange; instead, oxygen is provided by the placenta. To facilitate this, the fetus utilizes specialized shunts: the foramen ovale (an opening between the atria) and the ductus arteriosus (a connection between the pulmonary trunk and aorta).
After birth, as pressure changes in the heart, these structures close. The foramen ovale typically fuses to become the fossa ovalis, and the ductus arteriosus becomes the ligamentum arteriosum. If the foramen ovale fails to close completely, it is known as a patent foramen ovale, which can allow blood clots to bypass the lungs and travel directly to the brain, potentially causing a stroke.
Diagram illustrating fetal circulation shunts and their adult remnants, including the foramen ovale and ductus arteriosus.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.