Anatomy and Neurovasculature of the Posterior Shoulder
This article provides a comprehensive overview of the posterior shoulder, detailing its muscular divisions (axio-appendicular and scapulohumeral), vital neurovascular structures, and key anatomical gateways. It includes information on the rotator cuff, nerves like the suprascapular and axillary, and arteries forming th
The posterior shoulder is a complex anatomical region characterized by a sophisticated arrangement of muscles, nerves, and blood vessels. Understanding this area requires a distinction between muscles that connect the axial skeleton to the appendicular skeleton and those that act directly on the glenohumeral joint. This article provides an overview of these muscular divisions, the vital neurovascular structures, and the anatomical "gateways" that facilitate the passage of these structures through the shoulder region.
Muscular Divisions of the Posterior Shoulder
The muscles of the posterior shoulder are categorized into two primary groups based on their attachment points and functional roles: the axio-appendicular (extrinsic) muscles and the scapulohumeral (intrinsic) muscles.
Axio-appendicular (Extrinsic) Muscles
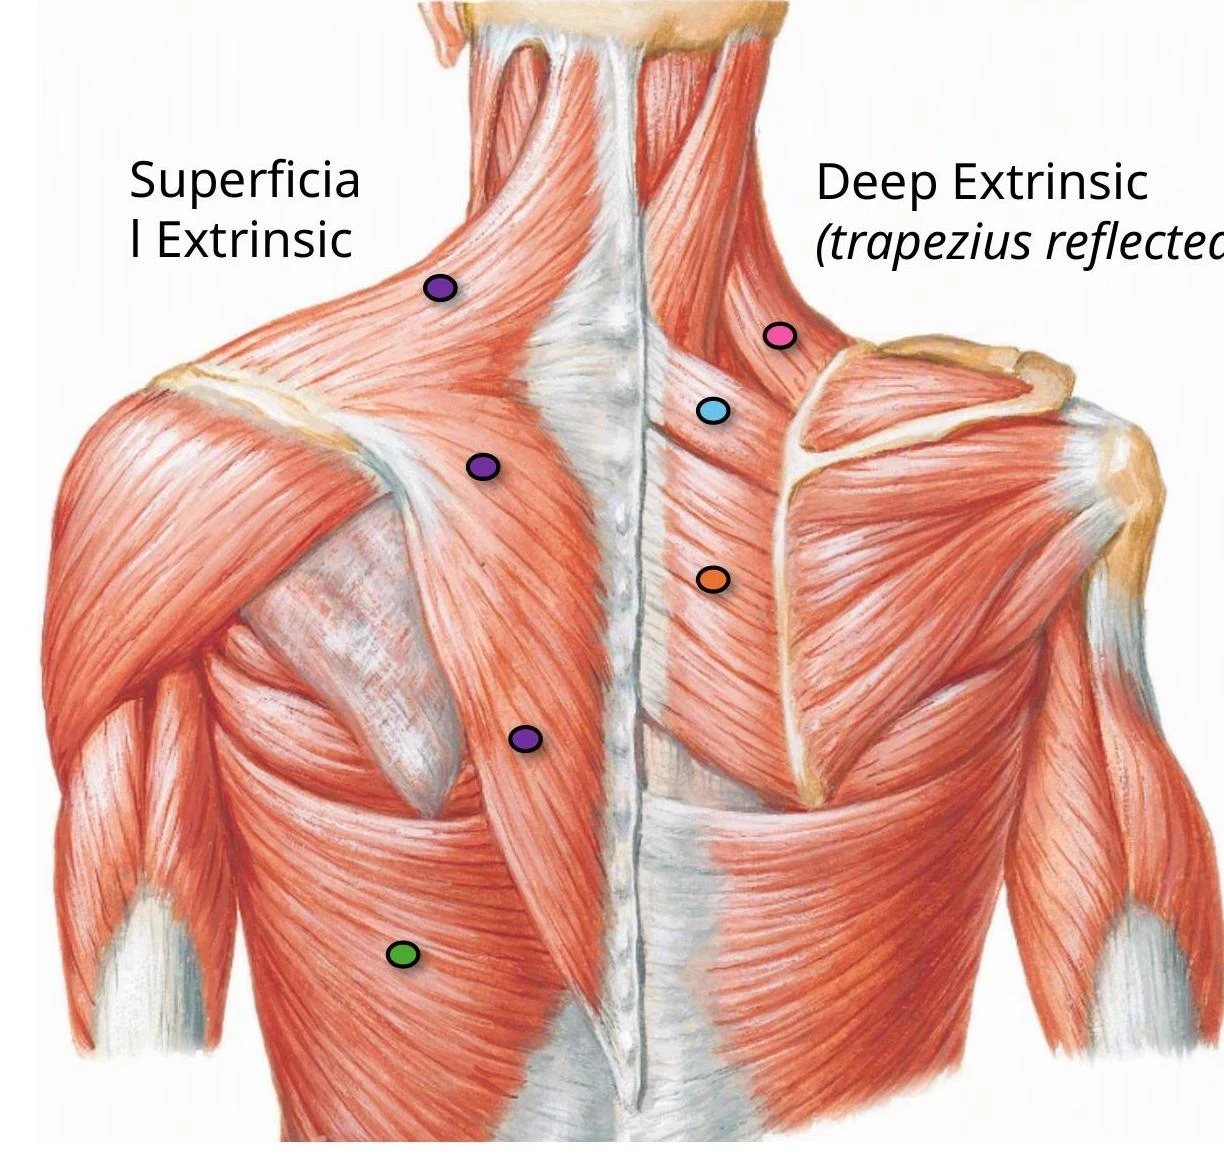
These muscles connect the axial skeleton (such as the spine or ribs) to the appendicular skeleton (the scapula or humerus). They are further divided into superficial and deep layers.
Superficial Layer:
Trapezius: A large, superficial muscle of the back.
Latissimus dorsi: A broad muscle that covers much of the lower back.
Deep Layer:
Levator scapulae: Assists in elevating the scapula.
Rhomboid minor and Rhomboid major: These muscles assist in retracting and stabilizing the scapula.
An anatomical illustration of the superficial and deep extrinsic muscles of the upper back, with colored dots indicating specific points.
Scapulohumeral (Intrinsic) Muscles
These muscles act directly on the glenohumeral joint (the shoulder joint) to facilitate movement and stability.
Deltoid: A large, triangular muscle that is the primary mover of the arm. It has three parts: anterior (flexion/medial rotation), middle (abduction), and posterior (extension/lateral rotation). While the deltoid is highly effective for abduction, it becomes the primary driver after the first 15° of movement.
Teres major: Assists in adduction and medial rotation of the humerus.
The Rotator Cuff (SITS)
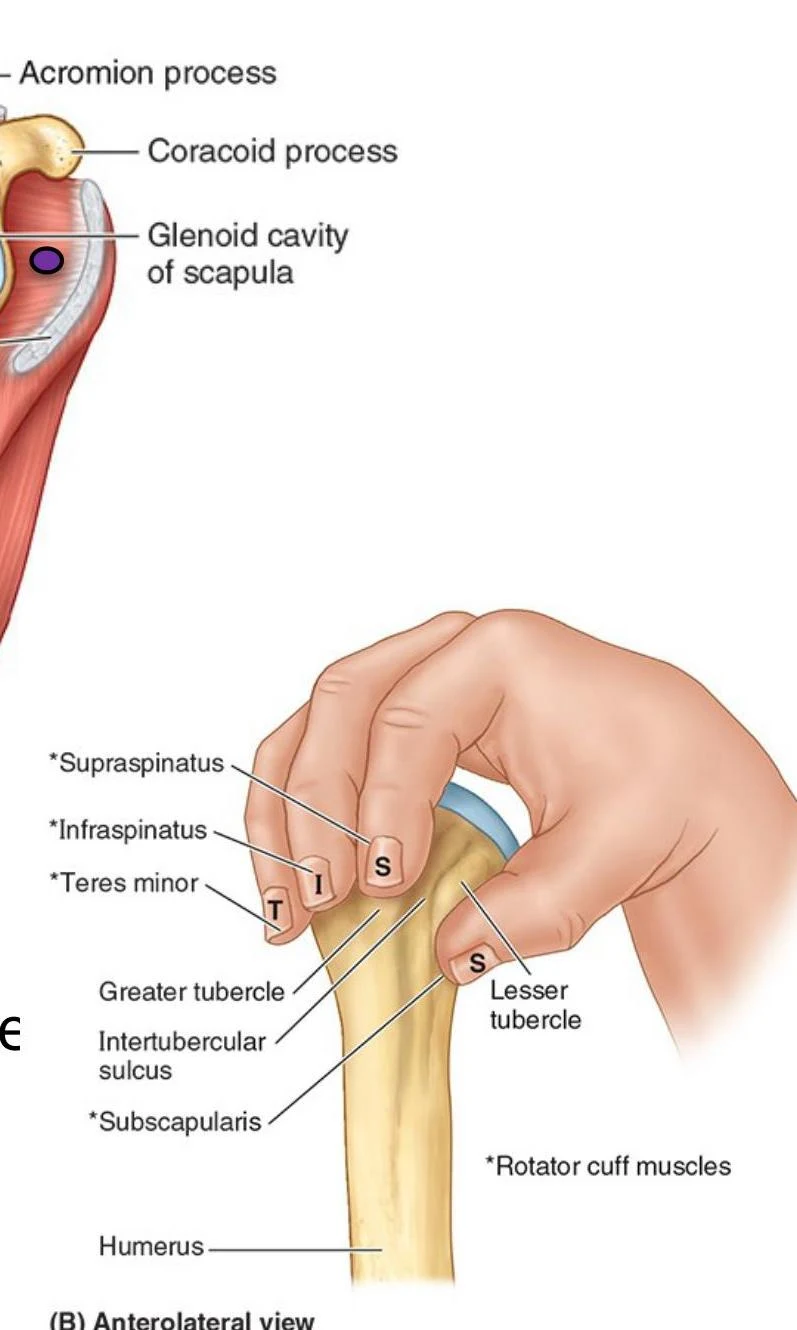
The rotator cuff is a functional unit consisting of four muscles whose tendons fuse with the fibrous joint capsule. This creates a "cuff" that stabilizes the humeral head within the glenoid cavity.
Muscle
Origin
Insertion
Primary Action
Innervation
Supraspinatus
Supraspinous fossa
Superior facet of greater tubercle
Initiates abduction (first 15°)
Suprascapular nerve (C5, C6)
Infraspinatus
Infraspinous fossa
Middle facet of greater tubercle
Lateral rotation
Suprascapular nerve (C5, C6)
Teres minor
Lateral border of scapula
Inferior facet of greater tubercle
Lateral rotation
Axillary nerve (C5, C6)
Subscapularis
Subscapular fossa
Lesser tubercle of humerus
Medial rotation
Upper/Lower subscapular nerves (C5, C6)
An illustration of the human shoulder joint, detailing the glenoid cavity of the scapula, humerus, and rotator cuff muscles including supraspinatus, infraspinatus, teres minor, and subscapularis.
Clinical Connection: Rotator Cuff Injury
Supraspinatus is the most commonly ruptured tendon in the rotator cuff. Injuries often present as night pain, weakness in lifting the arm, and joint crepitus (grinding sensations). Additionally, Supraspinatus Tendinitis can cause a "painful arc," where pain is specifically felt during 60-120° of abduction as the tendon impinges against the acromion.
Neurovasculature of the Posterior Shoulder
Nerves
The innervation of the posterior shoulder is provided by several key nerves originating from the brachial plexus:
Suprascapular nerve (C5-C6): Passes through the suprascapular foramen to innervate the supraspinatus and infraspinatus.
Axillary nerve (C5-C6): Courses from the axilla to the posterior shoulder, innervating the deltoid and teres minor.
Subscapular nerves (C5-C6): The upper and lower branches innervate the subscapularis.
Cutaneous (Sensory) Innervation:
Lateral supraclavicular nerve (C3, C4): Supplies the superior/lateral posterior shoulder.
Superior lateral cutaneous nerve of arm: Supplies the superior/lateral aspect of the arm.
Intercostobrachial nerve (T2): Supplies the axilla and medial proximal arm.
Blood Supply
The posterior shoulder is supported by a robust network of arteries that form a "scapular arcade," providing collateral circulation:
Suprascapular artery: Supplies the supraspinous and infraspinous fossae.
Circumflex humeral arteries: The anterior and posterior branches encircle the surgical neck of the humerus.
Circumflex scapular artery: Curves around the lateral border of the scapula to enter the infraspinous fossa.
Dorsal scapular artery: Anastomoses with the suprascapular and circumflex scapular arteries.
Thoracodorsal artery: Supplies the latissimus dorsi and anastomoses with the dorsal scapular artery.
Exam Tip: Arterial Anastomoses
Because of the extensive anastomoses in the scapular arcade, if the axillary artery is slowly occluded, collateral blood flow from the subclavian artery branches can often prevent ischemia to the surrounding tissues.
Anatomical Gateways
The posterior shoulder contains specific spaces or "gateways" through which nerves and vessels pass between different compartments.
1. Suprascapular Foramen
This is the route for structures passing from the base of the neck to the posterior shoulder. It is formed by the transverse scapular ligament stretching over the suprascapular notch.
Mnemonic: Army over Navy
To remember the contents of the suprascapular notch: The Suprascapular Artery goes over the ligament, while the Suprascapular Nerve goes under the ligament.
2. Quadrangular Space
This space serves as a passage for the axillary nerve and the posterior circumflex humeral artery.
Superior border: Inferior border of teres minor.
Inferior border: Superior border of teres major.
Medial border: Lateral margin of the long head of triceps.
Lateral border: Surgical neck of the humerus.
Clinical Connection: Quadrangular Space Syndrome (QSS)
Hypertrophy or fibrosis in this area can impinge on the axillary nerve and the posterior circumflex humeral artery. Patients may present with diffuse posterior shoulder pain, lateral arm paresthesia, and weakness in the deltoid or teres minor.
3. Triangular Space
This area facilitates communication between the axilla and the posterior scapular region.
Borders: Medial margin of the long head of triceps, inferior margin of teres minor, and superior margin of teres major.
Contents: Circumflex scapular artery and vein.
4. Triangular Interval
This passage connects the anterior and posterior compartments of the arm and axilla.
Borders: Lateral margin of the long head of triceps, the shaft of the humerus, and the inferior margin of teres major.
Contents: Radial nerve, profunda brachii artery, and associated veins.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.