Anatomy and Mechanics of the Thoracic Cavity and Lungs
Explores the anatomy of the thoracic cavity, focusing on the diaphragm as the primary muscle of respiration, the structure and function of the lungs, the pleura, and the mechanics of breathing. It also covers the tracheobronchial tree and clinical correlations like pneumothorax.
The thoracic cavity is a complex anatomical space designed to facilitate the vital processes of respiration and circulation. At the heart of this system is the relationship between the muscular pump of the diaphragm, the protective pleura, and the branching architecture of the tracheobronchial tree. Understanding these structures is essential for grasping how we move air into the lungs and how clinical complications, such as pneumothorax or aspiration, occur.
The Diaphragm: The Primary Engine of Respiration
The diaphragm is a musculotendinous sheet that serves as the anatomical boundary separating the thorax from the abdomen. Its skeletal muscle fibers originate from several key landmarks: the costal margin, the vertebral bodies ($L1$-$L3$), the medial and lateral arcuate ligaments, and the xiphoid process. These fibers converge and insert into a central tendon.
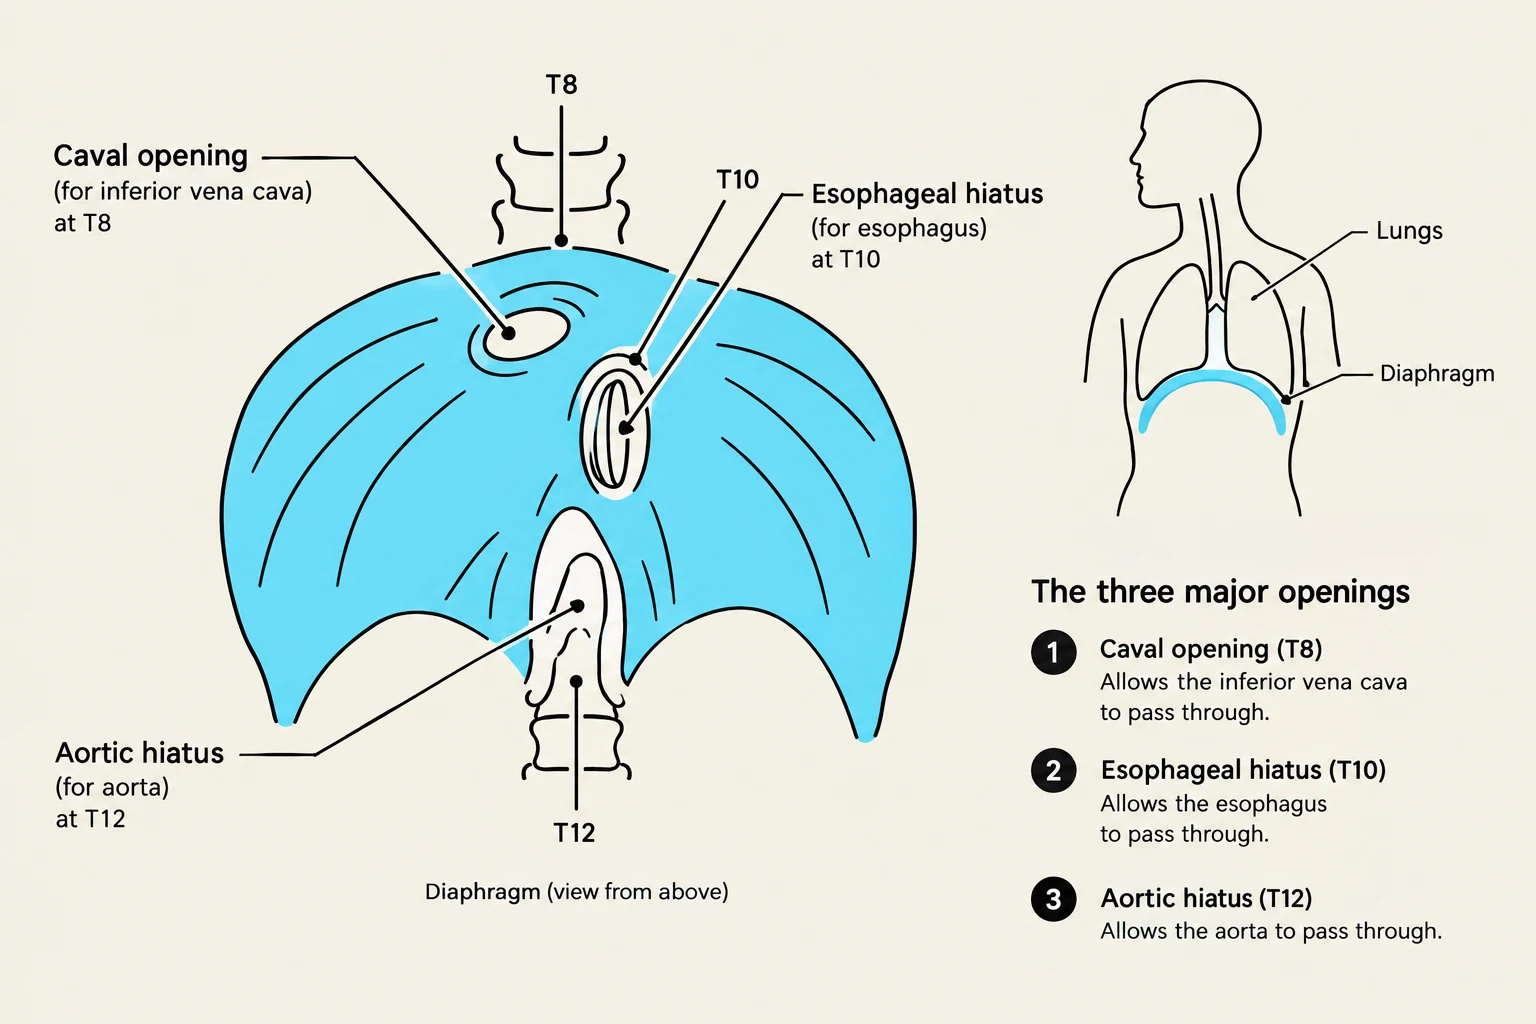
Because the diaphragm must separate two distinct body cavities while allowing vital structures to pass through, it contains three major openings (hiatuses). These openings are clinically significant due to their specific vertebral levels and the structures they permit to pass:
Caval Opening ($T8$): Transmits the Inferior Vena Cava.
Esophageal Hiatus ($T10$): Transmits the esophagus and the vagal trunks.
Aortic Hiatus ($T12$): Transmits the aorta and the thoracic duct.
Study Tip: The Mnemonic for Diaphragmatic Openings
To remember the levels and contents, use: "I 8 10 Eggs At 12"
I (IVC) at 8 ($T8$)
Esophagus (and Vagus) at 10 ($T10$)
Aorta (and Thoracic duct) at 12 ($T12$).
Diagram illustrating the diaphragm and its three major openings: the caval opening (T8), esophageal hiatus (T10), and aortic hiatus (T12), with descriptions of what passes through each.
Innervation: The Phrenic Nerves
The motor and sensory functions of the diaphragm are provided by the phrenic nerves. These nerves originate from the anterior rami of spinal levels $C3, C4,$ and $C5$. A common mnemonic to remember this is: "C3, 4, 5 to stay alive". Beyond the diaphragm, the phrenic nerves also provide somatic sensory innervation to the mediastinal pleura and the pericardium.
Mechanics of Breathing
Breathing is a dynamic process involving pressure changes within the thoracic cavity. Inspiration is an active process that requires energy. The diaphragm is the primary muscle of inspiration; when it contracts, it flattens, increasing the volume of the thoracic cavity. This can be assisted by accessory muscles, including the scalene muscles of the neck and the external intercostal muscles.
Conversely, expiration is typically a passive process during quiet breathing, occurring as the diaphragm and other muscles relax. However, during forced expiration (such as coughing or heavy exercise), the internal intercostal muscles and the abdominal muscles are recruited to drive air out.
The Pulmonary Cavities and the Pleura
The lungs are not directly attached to the thoracic wall; instead, they are enveloped by a fibroserous membrane called the pleura. This membrane consists of two distinct layers:
Visceral Pleura: Covers the surface of the lung itself.
Parietal Pleura: Lines the inner walls of the pulmonary cavity.
Between these two layers lies the pleural cavity, a potential space containing a thin film of serous fluid that reduces friction during breathing.
Clinical Correlation: Pneumothorax
A pneumothorax occurs when the integrity of the pleural cavity is breached—for example, by a puncture of the parietal pleura. This allows air to enter the pleural space, breaking the vacuum/pressure relationship and causing the lung to collapse. Clinicians must be cautious during procedures like dry needling near the thoracic cage, as accidental puncture can lead to this condition.
Anatomy of the Lungs
The lungs are characterized by their surfaces, lobes, and the structures that enter them. Each lung possesses a costal surface (facing the ribs), a mediastinal surface (facing the heart), and a diaphragmatic surface (resting on the diaphragm).
Lobes and Surfaces
The lungs are asymmetrical. The right lung typically has more lobes than the left. The left lung is characterized by having fewer lobes and the presence of a lingula.
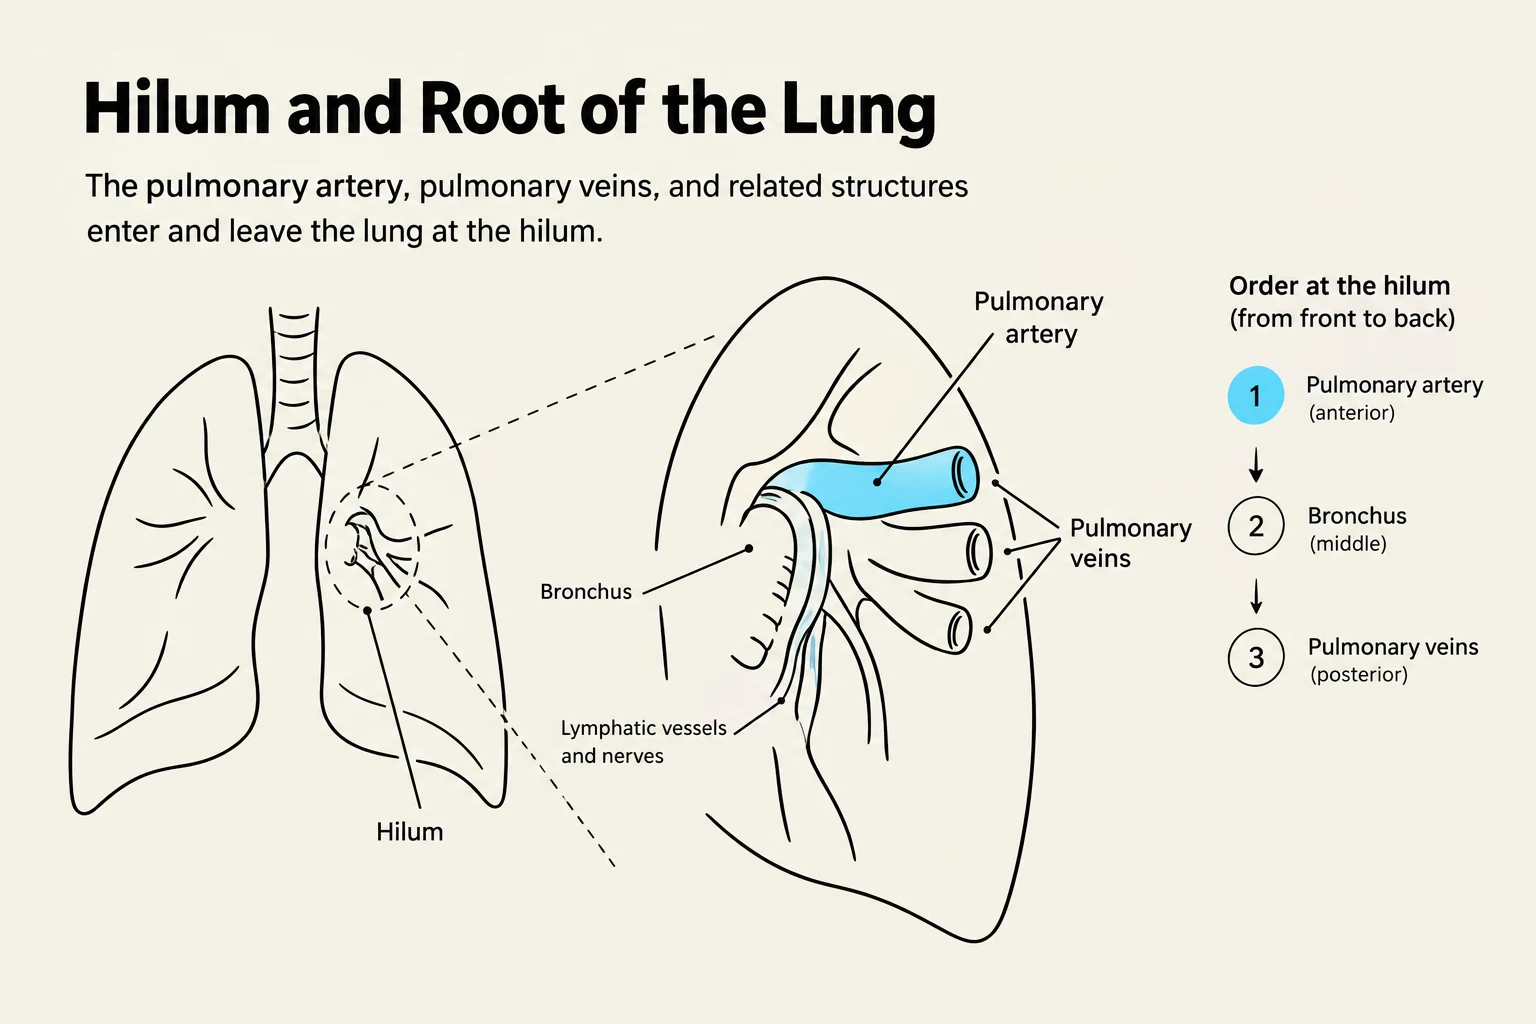
The hilum is the specific site on the mediastinal surface where the root of the lung enters and exits. The root includes several vital structures:
Pulmonary arteries and veins
Primary bronchi
Bronchial arteries and veins
Lymphatics and autonomic nerves.
Diagram illustrating the hilum and root of the lung, showing the pulmonary artery, pulmonary veins, and bronchus, along with their order from front to back.
Blood Supply: Pulmonary vs. Bronchial Arteries
It is crucial to distinguish between the two types of arteries serving the lungs:
Pulmonary Arteries: These transport deoxygenated blood from the heart to the alveolar capillary beds for gas exchange.
Bronchial Arteries: These branch off the thoracic aorta and provide oxygenated blood to the actual lung tissue (the stroma) and the visceral pleura.
The Tracheobronchial Tree
The pathway for air begins at the trachea, which starts at the $C6$ vertebral level. The trachea is composed of C-shaped rings of hyaline cartilage, which are closed posteriorly by the smooth-walled trachealis muscle.
The trachea descends until it reaches the carina, a wedge-shaped piece of cartilage that marks the bifurcation into the primary (main) bronchi.
Aspiration Risk
The anatomy of the primary bronchi significantly influences clinical outcomes during choking or aspiration:
Right Main Bronchus: Shorter, wider, and more vertical (angled at approximately 25-30∘ from the vertical).
Left Main Bronchus: Longer, narrower, and more horizontal (angled at approximately 45∘ from the vertical).
Because of this more vertical orientation, inhaled foreign objects are much more likely to be aspirated into the right main bronchus.
Branching and Functional Units
The bronchial tree continues to divide into smaller branches:
Lobar (secondary) bronchi: One enters each lobe of the lung.
Segmental (tertiary) bronchi: One enters each bronchopulmonary segment.
The bronchopulmonary segments are the most important functional units of the lung. They are discrete, pyramidal-shaped units subdivided by thin connective tissue septa. Because each segment is anatomically and functionally independent, surgeons can perform a resection of a single segment without compromising the entire lobe.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.