Explores anatomical obstructions of the upper airway, such as deviated septums and nasal polyps, and their management through pharmacological and surgical interventions.
The ability to breathe efficiently depends on a clear, unobstructed pathway from the external environment through the nasal cavity and into the lower respiratory tract. When the physical architecture of this pathway is compromised by structural abnormalities, the body faces significant challenges in gas exchange, oxygenation, and sleep quality. Anatomical obstructions are not merely "stuffy noses"; they are physical barriers that can lead to chronic hypoxia, increased work of breathing, and long-term cardiovascular strain.
This article explores the primary anatomical obstructions—specifically deviated septums and nasal polyps—and examines the clinical pathways for managing these conditions through both pharmacological and surgical interventions.
Understanding the Nasal Architecture
To understand what goes wrong, one must first understand the normal state. The nasal cavity is divided by the nasal septum, a wall of bone and cartilage that separates the left and right nostrils. This structure ensures that airflow is distributed evenly and that the air is warmed, humidified, and filtered before reaching the lungs.
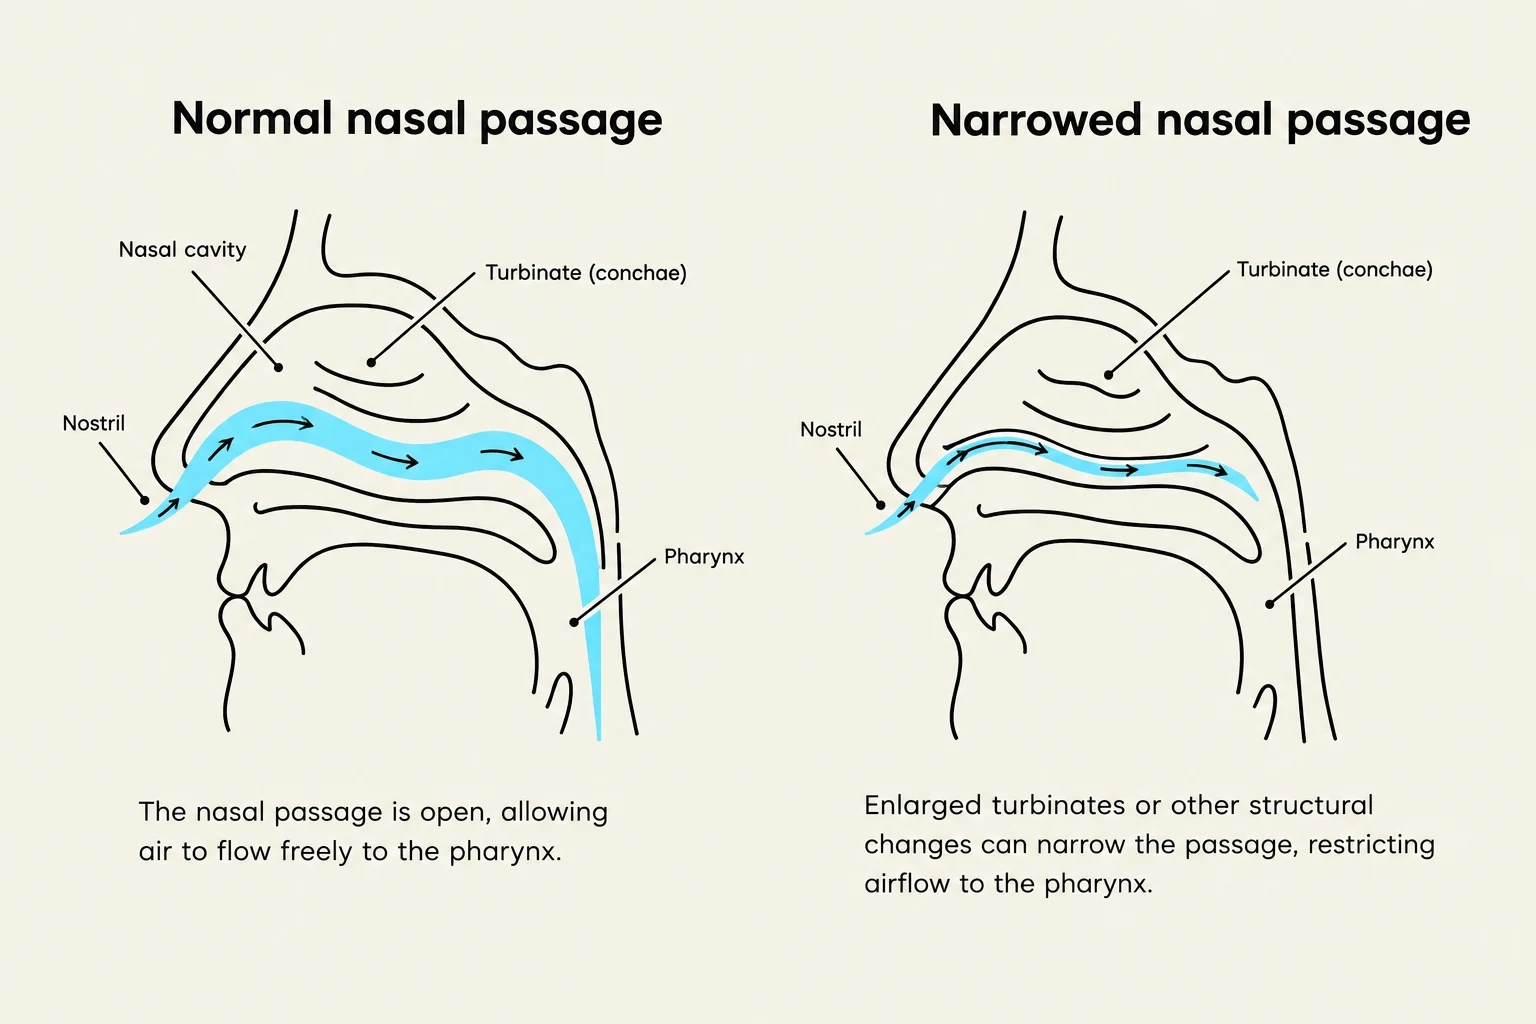
When this architecture is altered, the resistance to airflow increases. According to Poiseuille's Law, the resistance to fluid (or air) flow is inversely proportional to the fourth power of the radius (R∝r41). This means that even a small reduction in the diameter of the nasal passage due to an obstruction results in a massive increase in the effort required to inhale.
Diagrams illustrating normal and narrowed nasal passages, showing airflow in each scenario.
Deviated Septum: Structural Misalignment
A deviated septum occurs when the thin wall (nasal septum) between your nostrils is displaced to one side. This can be congenital (present at birth) or the result of trauma, such as a sports injury or a car accident.
Clinical Presentation
Patients with a deviated septum often report:
Difficulty breathing through one or both nostrils.
Nasal congestion that does not respond to decongestants.
Frequent sinus infections due to impaired drainage.
Snoring or sleep apnea.
Management Strategies
Management is dictated by the severity of the obstruction and the impact on the patient's quality of life.
1. Pharmacological Management:
For mild cases, medications are used to manage the symptoms rather than the underlying structural issue. Nasal corticosteroids can reduce inflammation in the mucosal lining, which may slightly increase the available space in the nasal passage. However, it is crucial to note that medication cannot "straighten" a bone or cartilage.
2. Surgical Management (Septoplasty):
When the deviation is significant enough to cause chronic respiratory distress or sleep disorders, a septoplasty is indicated. During this procedure, the surgeon repositions the septum to the midline, removing or reshaping the bone and cartilage to create a symmetrical airway.
Exam Tip: If a question asks for the definitive treatment of a structural nasal obstruction, look for "surgical intervention." Pharmacological treatments like steroids are considered symptomatic management, not curative for the anatomical defect itself.
Nasal Polyps: Soft Tissue Obstructions
Unlike a deviated septum, which is a rigid structural issue, nasal polyps are soft, painless, noncancerous growths on the lining of your nasal passages or sinuses. They often resemble teardrops or grapes hanging from the nasal mucosa.
Pathophysiology
Polyps are typically the result of chronic inflammation caused by asthma, recurring infections, allergies, or certain immune disorders. As these polyps grow, they can physically block the ostia (the openings of the sinuses), preventing mucus from draining. This creates a vicious cycle: blockage leads to mucus buildup, which leads to more inflammation, which leads to larger polyps.
Management Strategies
The approach to polyps is often more heavily weighted toward pharmacological control than septal deviations because polyps are driven by inflammatory processes.
1. Pharmacological Management:
Corticosteroids: Inhaled or oral corticosteroids are the gold standard. They work by reducing the inflammatory response that drives polyp growth.
Biologics: In severe, refractory cases, newer biologic therapies target specific inflammatory pathways (such as IgE or Interleukin-5) to prevent polyp formation.
2. Surgical Management (Polypectomy/FESS):
If polyps are large enough to cause total airway obstruction or severe sinus disease, surgery is required. Functional Endoscopic Sinus Surgery (FESS) is the common approach. Surgeons use an endoscope to visualize the nasal passages and remove the polyps while preserving as much healthy tissue and sinus function as possible.
Comparative Summary of Obstructions
Feature
Deviated Septum
Nasal Polyps
Nature
Rigid (Bone/Cartilage)
Soft (Inflammatory tissue)
Primary Cause
Trauma or Congenital
Chronic Inflammation/Allergy
Primary Goal
Structural Realignment
Inflammation Reduction
Definitive Treatment
Septoplasty
Polypectomy / FESS
Edge Cases and Clinical Nuances
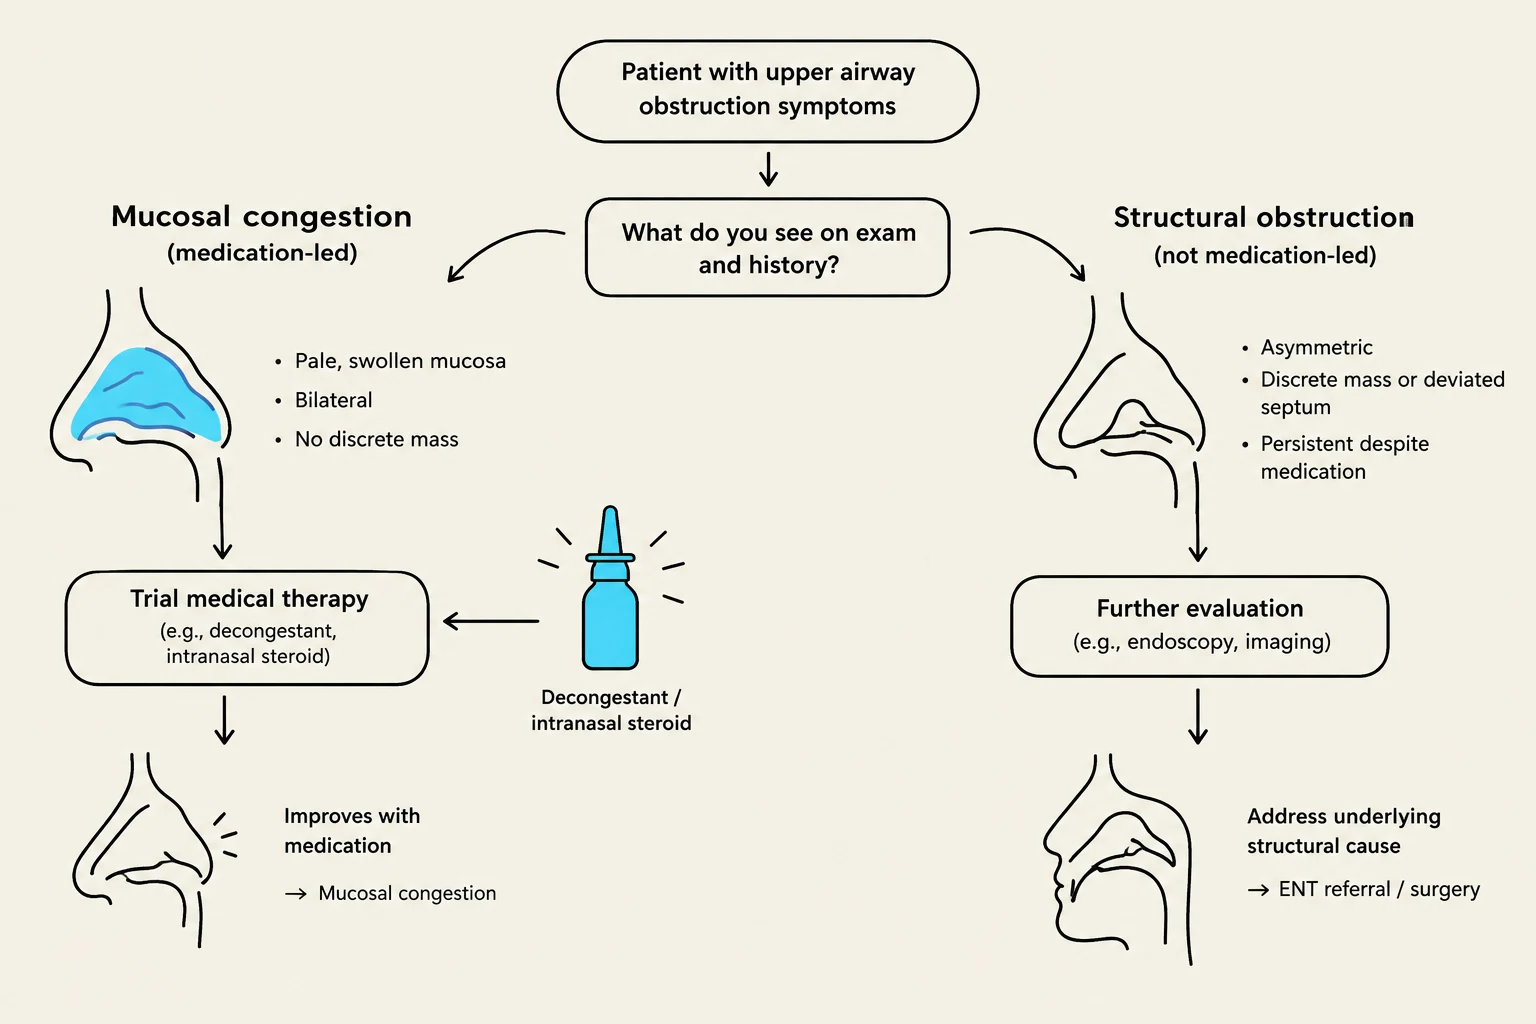
Students often struggle with distinguishing between "congestion" and "obstruction."
Congestion is typically mucosal (swelling of the tissue), which is often reversible with medication.
Obstruction is anatomical (a physical blockage), which often requires mechanical intervention.
A common "edge case" occurs when a patient has both a deviated septum and nasal polyps. In these instances, surgery must be carefully sequenced. If a surgeon performs a septoplasty first but leaves the polyps intact, the patient may still experience significant airway resistance. Conversely, removing polyps without correcting the septum may lead to poor sinus drainage and rapid polyp recurrence.
This flowchart illustrates the differential diagnosis and management of upper airway obstruction symptoms, distinguishing between mucosal congestion and structural obstruction.
Conclusion
Anatomical obstructions of the upper airway represent a significant hurdle to efficient respiration. Whether the issue is the rigid misalignment of the septum or the inflammatory growth of polyps, the physiological consequence is an increase in airway resistance and a potential decrease in oxygenation. Understanding the distinction between structural and inflammatory causes is the key to selecting the appropriate management strategy, ranging from topical steroids to complex endoscopic surgeries.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.