Aerosol Drug Delivery Systems: Principles and Devices
Explores the principles of aerosol drug delivery, focusing on pulmonary applications, lung anatomy, particle deposition mechanisms, and various inhaler devices like MDIs, DPIs, SMIs, and nebulizers. Discusses emerging technologies and essential patient counseling.
An aerosol is defined as a dispersion of liquid droplets or solid particles within a gas. In the pharmaceutical industry, these dispersions are utilized for a variety of purposes, ranging from topical applications to sophisticated pulmonary drug delivery. By delivering medication directly to the respiratory tract, clinicians can achieve targeted therapeutic effects with unique pharmacokinetic advantages.
Pulmonary Drug Delivery: Applications and Advantages
Pulmonary drug delivery is a specialized field aimed at treating both local airway diseases and systemic conditions.
Clinical Applications
Airway Diseases: Common treatments for asthma and Chronic Obstructive Pulmonary Disease (COPD) include bronchodilators and inhaled corticosteroids.
Infections: Inhaled antibiotics are used for specific indications, such as treating chronic Pseudomonas infections in patients with cystic fibrosis.
Systemic Delivery: Certain protein drugs, such as inhaled insulin, are designed for systemic action, though not all proteins are suitable for this route.
Advantages and Challenges
Delivering drugs via inhalation offers several clinical benefits:
Faster onset of action for most drugs.
Smaller required doses due to direct delivery to the target site.
Lower side-effect profile and reduced pain compared to systemic administration.
However, the method is not without difficulties. Only a small fraction of the total dose is typically deposited in the lungs. Success depends heavily on strict particle size control, correct patient technique, and extensive patient education.
Lung Anatomy and Deposition Zones
To understand how drugs reach their target, one must understand the complex architecture of the human respiratory system. The surface area of the lungs is approximately 150 m2, which is more than half the area of a tennis court.
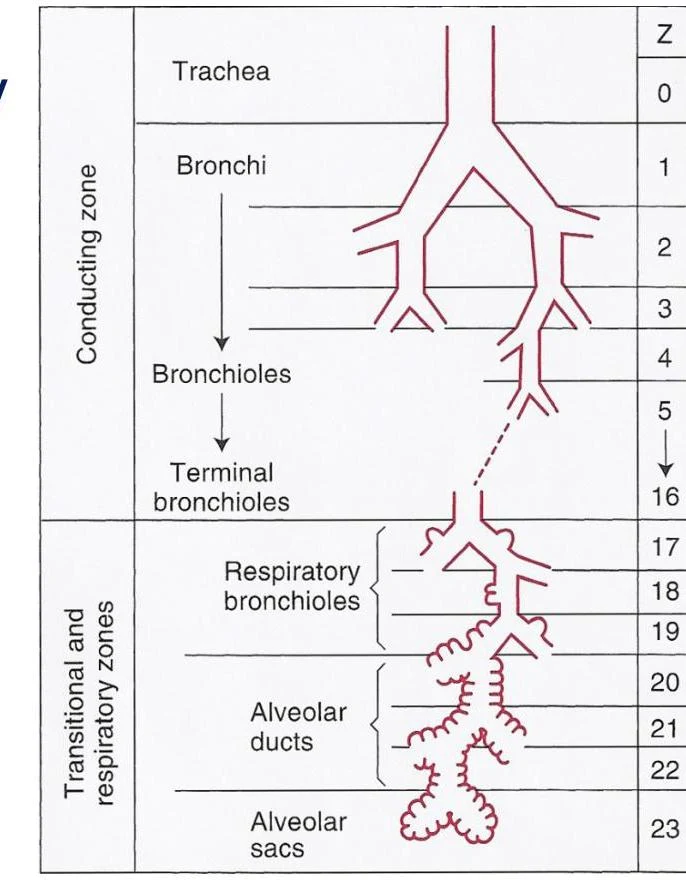
The airway structure is often described using the Weibel model, which accounts for approximately 23 generations of branching. These are divided into two primary zones:
Conducting Zone: The upper airways that transport air but do not participate in gas exchange.
Respiratory Zone: The deeper regions, including the alveolar sacs, where gas exchange occurs.
Diagram illustrating the conducting and transitional/respiratory zones of the human respiratory system, showing the progression from the trachea to bronchi, bronchioles, alveolar ducts, and alveolar sacs.
Once a drug reaches the alveolar-capillary barrier, it can cross into the bloodstream for systemic absorption. This makes the lungs an excellent organ for drug delivery, though the structure remains incredibly delicate.
The Influence of Particle Size on Deposition
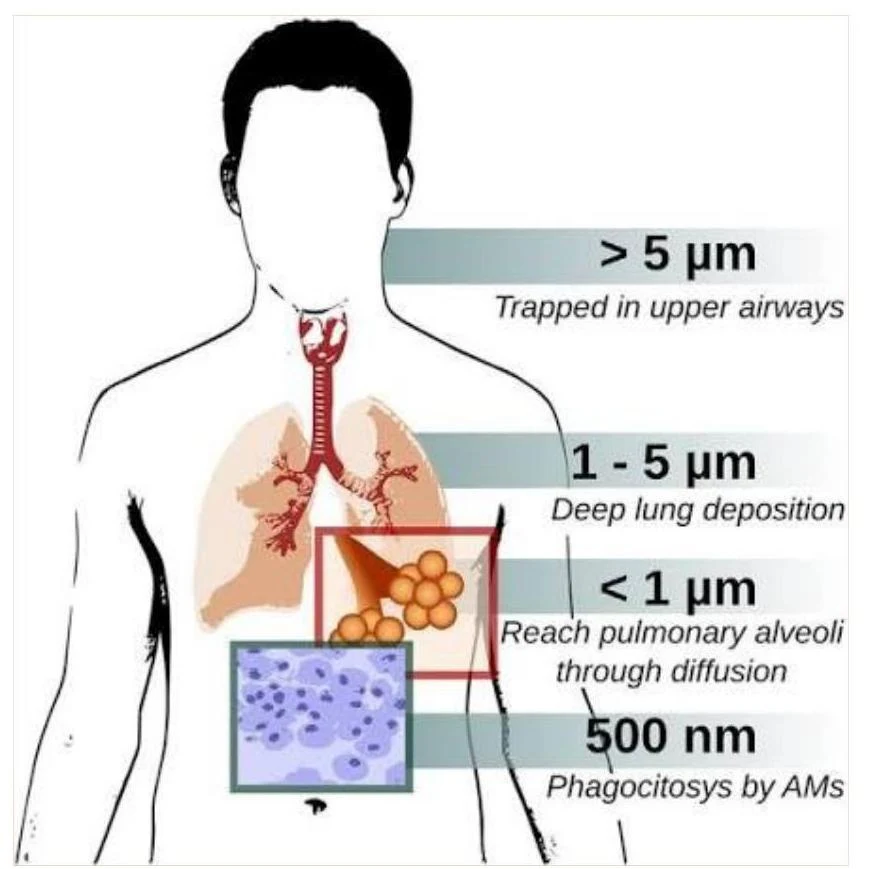
The most critical factor in determining where a drug lands in the lung is not its geometric diameter, but its aerodynamic diameter. The aerodynamic diameter predicts how a particle will behave under the influence of various physical forces during inhalation.
This diagram illustrates how particles of different sizes are deposited in the respiratory system. Larger particles (> 5 μm) are trapped in the upper airways, while smaller particles (1-5 μm) deposit deeper in the lungs. Particles less than 1 μm can reach the pulmonary alveoli through diffusion, and particles around 500 nm are phagocytosed by alveolar macrophages (AMs).
Mechanisms of Deposition
Deposition is governed by several overlapping physical mechanisms:
Inertial Impaction: Affects larger particles (>10–15μm). Due to their mass, these particles cannot follow the rapidly changing airflow in the branching airways and instead strike the walls of the mouth and throat.
Gravitational Sedimentation: Affects mid-sized particles (5–10μm). These particles "settle" out of the air stream onto the airway walls due to gravity.
Diffusion (Brownian Motion): Affects very small particles (<1μm). These particles move erratically due to collisions with gas molecules, allowing them to reach the deep alveolar regions.
Electrostatic Deposition: Particles may be deposited due to electrical charges generated by mechanical disintegration or the hygroscopic nature of the particle.
Exam Tip: The "Respirable Range"—the ideal size for reaching the lower airways and alveoli—is generally considered to be between 1–5μm.
This graph illustrates the deposition fraction of various airborne particles in the respiratory system as a function of their aerodynamic diameter, categorized by deposition mechanisms: diffusion, sedimentation, and inertial impaction.
Aerosol Delivery Devices
Different devices utilize different physical principles to transform a drug formulation into an inhalable aerosol.
Metered-Dose Inhalers (MDIs)
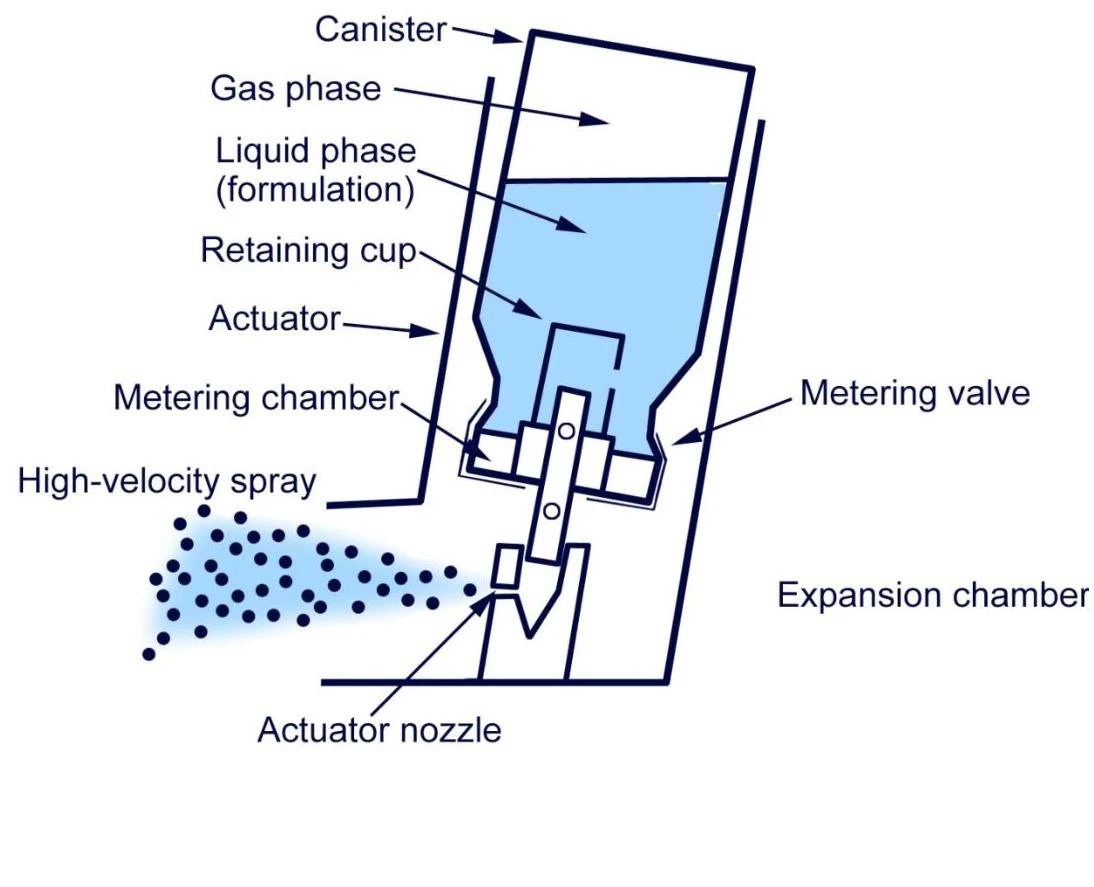
MDIs are pressurized devices that use a propellant to create a dispersion. They typically utilize a dual-valve mechanism: when the actuator is depressed, the chamber opens to the atmosphere while simultaneously sealing from the container to release a precise, high-velocity spray. Modern MDIs often use hydrofluoroalkane (HFA) propellants, though research is ongoing into lower-climate-impact alternatives.
Diagram illustrating the components and operation of a metered-dose inhaler, showing the canister, liquid and gas phases, metering valve, actuator, and the resulting high-velocity spray.
Dry Powder Inhalers (DPIs)
Unlike MDIs, DPIs are breath-actuated and do not use propellants. The patient's own inspiratory flow disperses the powder. Because they rely on the patient's breath, users must typically inhale quickly, forcefully, and deeply.
Soft Mist Inhalers (SMIs)
SMIs, such as the Respimat® system, represent a middle ground. They use a cartridge-based liquid formulation but do not use propellants. Instead, a mechanical spring forces the liquid through a "uniblock" capillary system, creating a slow-moving mist. This slow mist can improve lung penetration and reduce drug wastage in the mouth and throat compared to MDIs.
Nebulizers
Nebulizers convert liquid medication into an aerosol over a period of multiple breaths. They are often used for more intensive or continuous dosing requirements.
Emerging Technologies: RNA and Nanoparticles
The future of pulmonary delivery lies in the ability to treat genetic diseases directly in the lung. Researchers are currently exploring the use of lipid nanoparticles to deliver RNA-delivery particles for gene editing. This technology holds the potential to develop entirely new treatments for complex conditions like cystic fibrosis. Additionally, mucosal vaccines are under active development to provide localized immune responses.
Summary of Patient Counseling Essentials
Because delivery effectiveness is so dependent on technique, patient education is paramount.
Device Type
Key Technique
pMDI
Shake before use; inhale slowly and deeply while actuating; use a spacer if prescribed.
DPI
Load correctly; exhale away from the device; inhale quickly and deeply.
SMI
Prepare/prime as directed; inhale slowly and deeply while the mist is released.
Nebulizer
Requires regular cleaning and maintenance of the equipment.
Clinical Note: For patients using inhaled corticosteroids, always instruct them to rinse their mouth and spit after use to reduce the risk of local side effects.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.