Adrenergic Agonists and Blocking Agents: Modulating the Sympathetic Nervous System
An overview of adrenergic agonists and blocking agents, explaining how they mimic or antagonize the sympathetic nervous system and their various clinical applications.
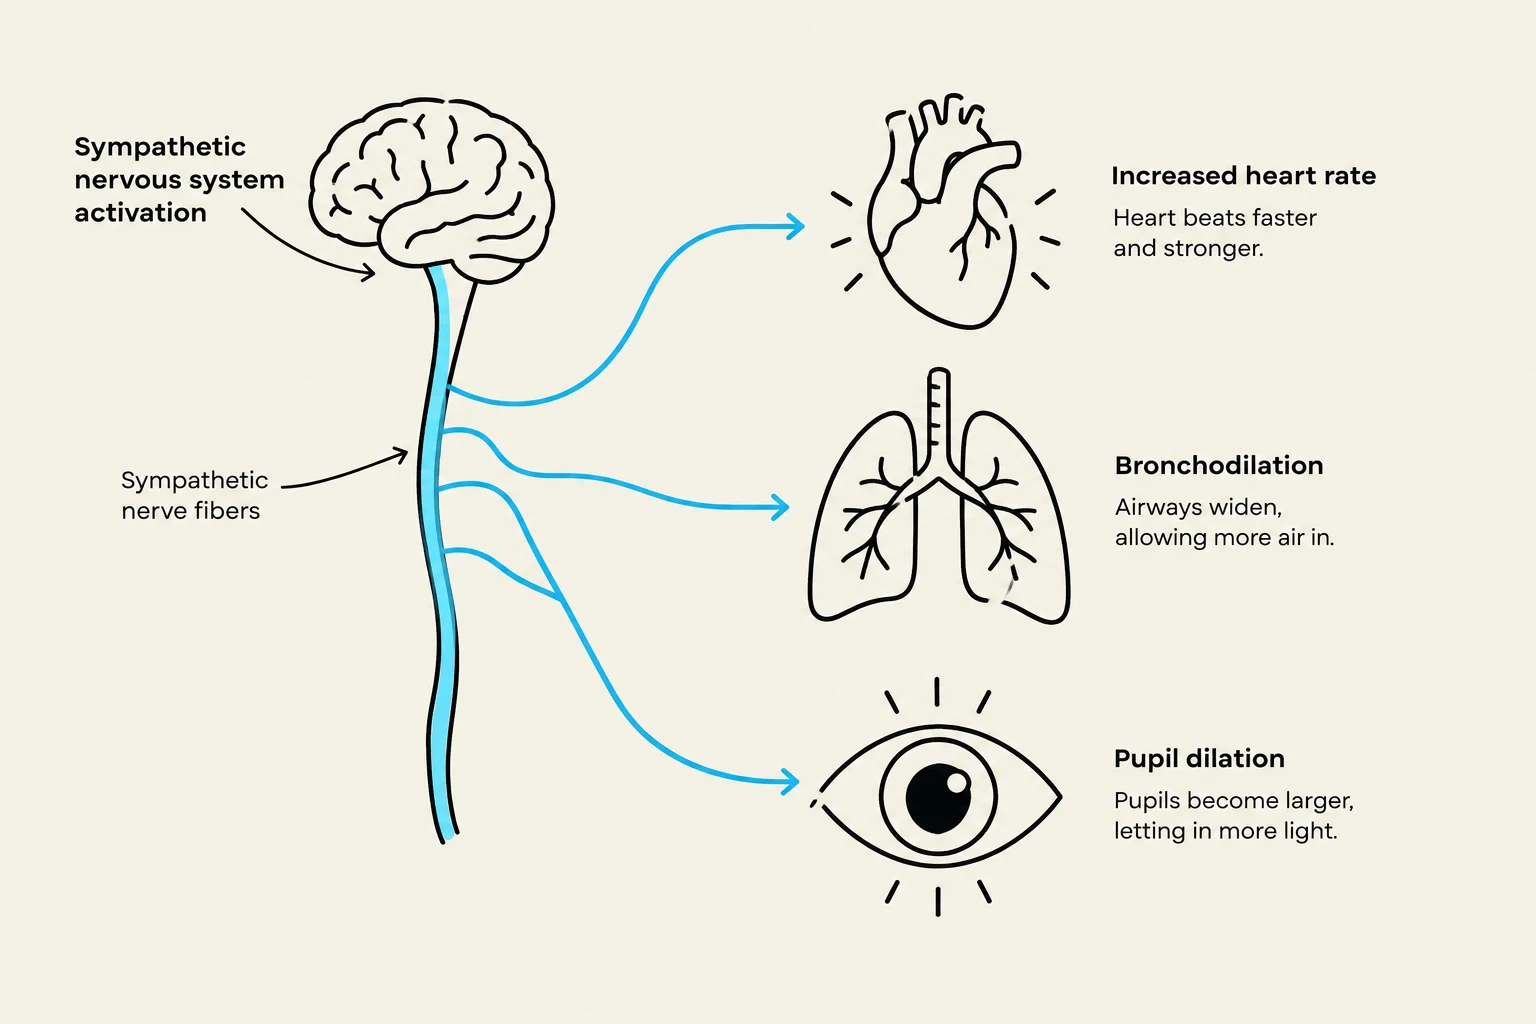
The autonomic nervous system (ANS) is responsible for maintaining homeostasis through two primary branches: the parasympathetic and the sympathetic nervous systems. While the parasympathetic system promotes "rest and digest" activities, the sympathetic nervous system (SNS) prepares the body for "fight or flight". This physiological response involves increasing heart rate, dilating bronchioles for better oxygenation, and diverting blood away from the gastrointestinal tract toward essential organs like the heart and skeletal muscles.
Pharmacology allows us to manipulate these responses using two main classes of drugs: adrenergic agonists, which mimic the SNS, and adrenergic blocking agents, which antagonize it.
Adrenergic Agonists (Sympathomimetics)
Adrenergic agonists are often referred to as sympathomimetic drugs because they mimic the effects of the sympathetic nervous system. These drugs work by stimulating adrenergic receptor sites, which are typically activated by the neurotransmitter noradrenaline (also known as norepinephrine).
The physiological outcome of an agonist depends entirely on which specific receptor subtype it targets. These receptors are broadly categorized into alpha (α) and beta (β) receptors.
Mixed α/β Agonists
Some agonists are not highly selective and act on both alpha and beta receptors simultaneously. These "mixed" agonists are critical in emergency medicine. Because they stimulate a wide range of sympathetic responses, they are used to treat life-threatening conditions such as:
Anaphylactic shock
Cardiac arrest
Emergency asthma.
Exam Tip: When you see a question regarding emergency resuscitation or severe allergic reactions, think of mixed α/β agonists acting as direct sympathomimetics at post-synaptic receptors.
This diagram illustrates the effects of sympathetic nervous system activation on the body, including increased heart rate, bronchodilation, and pupil dilation.
Alpha-Selective Adrenergics
Alpha-selective agonists target the α receptor subtypes, which have a higher affinity for noradrenaline than beta receptors. These are divided into two functional groups:
α1 Selective Agonists: These act as direct sympathomimetics at post-synaptic receptors. A common clinical use is nasal decongestion.
α2 Selective Agonists: These function differently; they act as indirect sympatholytics. Instead of stimulating a response, they activate pre-synaptic auto-inhibitory α2 receptors, which signals the neuron to reduce the release of noradrenaline, thereby treating hypertension.
Beta-Selective Adrenergics
Beta-selective agonists target the β receptors, which generally have a higher affinity for agents like isoprenaline than noradrenaline.
β1 Selective Agonists: These are primarily focused on the heart. They exert inotropic effects (increasing the force of muscle contraction) and chronotropic effects (increasing the heart rate). This makes them useful for treating congestive heart failure and cardiogenic shock.
β2 Selective Agonists: These target the smooth muscles of the lungs to induce bronchodilation. Consequently, they are a cornerstone of anti-asthmatic therapy.
This diagram illustrates the subtypes of adrenergic receptors (alpha-1, alpha-2, beta-1, and beta-2) and their respective effects on the body, such as vasoconstriction, decreased norepinephrine release, increased heart rate, bronchodilation, bladder sphincter contraction, vasodilation, and skeletal muscle relaxation. It also shows how the same neurotransmitter can bind to different receptors, leading to different physiological responses.
Adrenergic Blocking Agents (Sympatholytics)
While agonists mimic the SNS, adrenergic blocking agents—also known as sympatholytic drugs—act as antagonists. Their primary mechanism is to prevent noradrenaline from binding to and activating specific receptor sites.
Alpha-Adrenergic Antagonists
These agents primarily block post-synaptic α1 receptors. By preventing α1 stimulation, they can reduce blood pressure and are used to manage:
Hypertension
Phaeochromocytoma (a tumor of the chromaffin tissue)
Benign Prostatic Hyperplasia (BPH).
A common side effect to monitor in patients taking these drugs is postural hypotension (a sudden drop in blood pressure upon standing) and drowsiness.
Beta-Adrenergic Antagonists
Beta-blockers act through the competitive blocking of β-receptors. These are categorized into non-selective and selective types.
Non-selective β-Blockers
Non-selective blockers target both β1 and β2 receptors. They are used for a wide variety of cardiovascular and ocular conditions, including:
Hypertension, angina pectoris, and cardiac dysrhythmias.
Glaucoma.
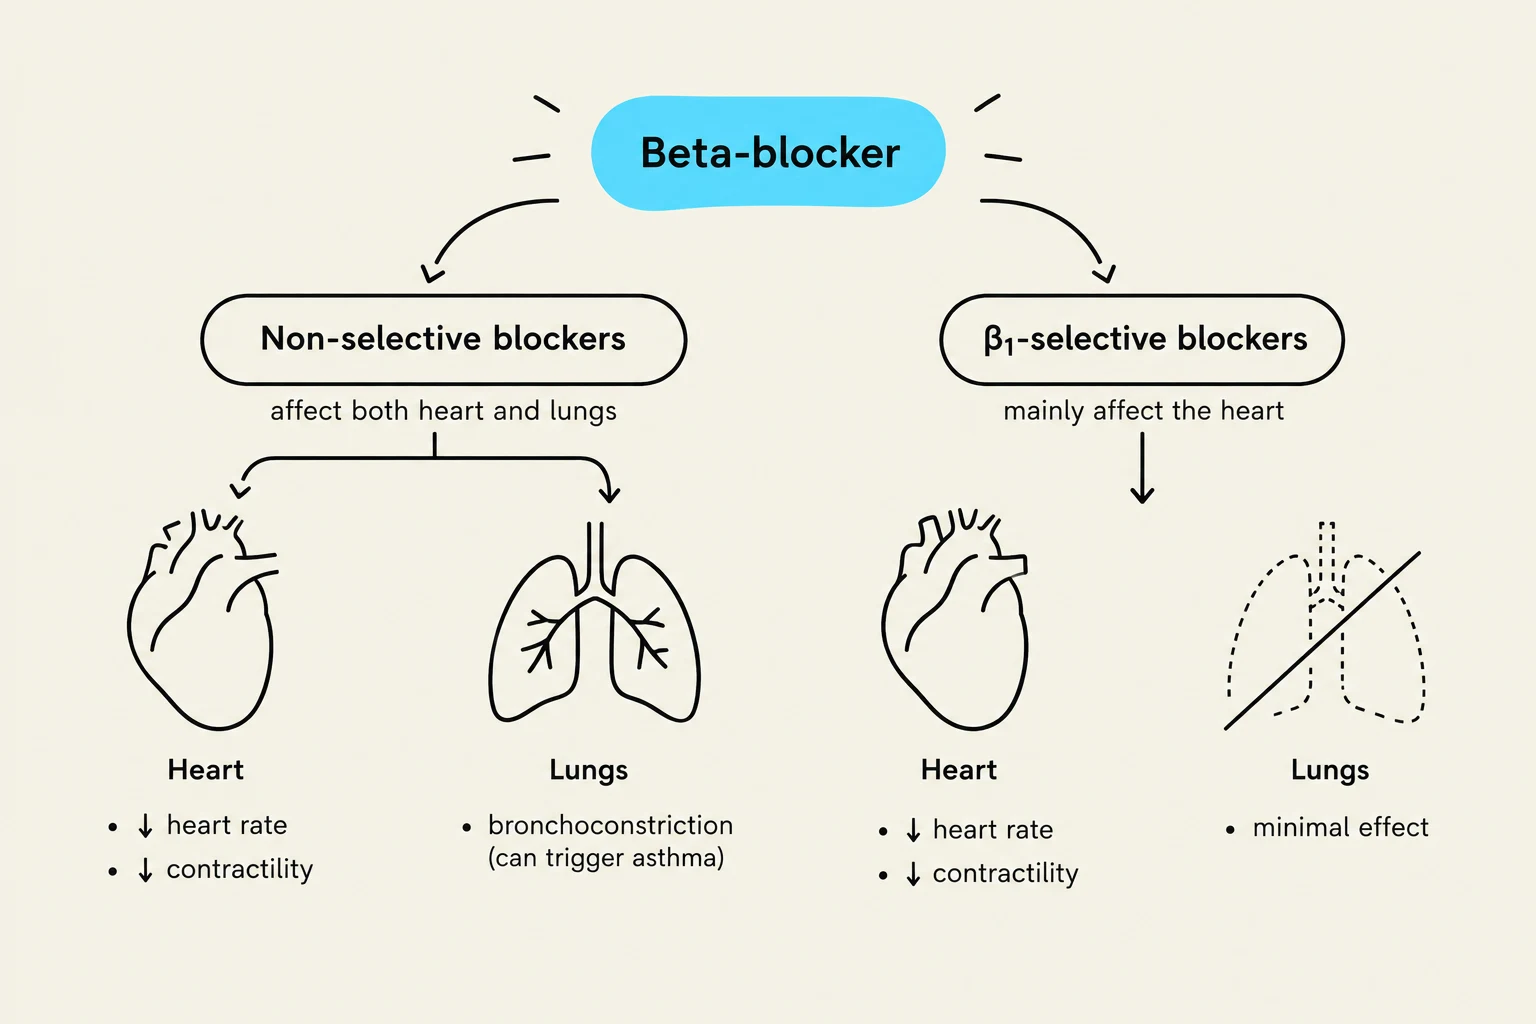
However, because they block β2 receptors in the lungs, they can cause bronchoconstriction. Other side effects include fatigue, hypoglycemia, and even "bad dreams" or depression.
β1-Selective Adrenergic Blocking Agents
To avoid the respiratory side effects of non-selective blockers, clinicians often use β1-selective antagonists. These are frequently referred to as "heart-selective" drugs.
By targeting β1 receptors specifically, these drugs can treat hypertension and angina while minimizing the blockade of β2 receptors in the lungs. This selectivity is vital for patient safety in specific populations.
Clinical Application:β1-selective blockers are the preferred choice for patients with respiratory conditions such as asthma, COPD, or seasonal allergic rhinitis, as they avoid the risk of inducing bronchoconstriction.
This diagram illustrates the effects of beta-blockers on the heart and lungs, differentiating between non-selective and beta-1 selective blockers.
Summary Table of Adrenergic Modulators
Drug Class
Primary Target
Key Clinical Use
Major Side Effect/Note
Mixed Agonist
α and β
Anaphylaxis, Cardiac Arrest
Severe hypertension/arrhythmia
α1 Agonist
α1
Nasal decongestion
Direct sympathomimetic
α2 Agonist
α2
Hypertension
Indirect sympatholytic
β1 Agonist
β1
Heart failure
Increases HR and contraction
β2 Agonist
β2
Asthma
Bronchodilation
α Antagonist
α1
Hypertension, BPH
Postural hypotension
Non-selective β Antagonist
β1 and β2
Hypertension, Glaucoma
Bronchoconstriction
β1-Selective Antagonist
β1
Hypertension (Asthma patients)
"Heart selective"
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.