Adjuvant Therapy for Breast Cancer: Clinical Evidence and Strategies
An overview of adjuvant therapy for breast cancer, detailing genomic and molecular risk assessment, targeted and endocrine therapies, chemotherapy strategies, and bone-targeted therapy. It highlights key clinical trials and evidence-based approaches to personalize treatment and improve outcomes.
The landscape of breast cancer management has shifted from a "one-size-fits-all" approach to a highly individualized model driven by molecular profiling and clinical trial data. Adjuvant therapy—treatment administered after the primary surgical intervention—aims to eradicate micrometastatic disease and reduce the risk of recurrence. Modern clinical decision-making relies heavily on the integration of genomic assays, targeted molecular therapies, and optimized systemic regimens to tailor care to the specific biological subtype of the tumor.
Genomic and Molecular Risk Assessment
One of the most significant advancements in adjuvant therapy is the ability to predict the biological behavior of hormone receptor-positive (HR+), human epidermal growth factor receptor 2-negative (HER2-) tumors. For many patients, the central clinical question is whether the addition of chemotherapy to endocrine therapy provides a meaningful survival benefit.
Recurrence Scores and Genomic Signatures
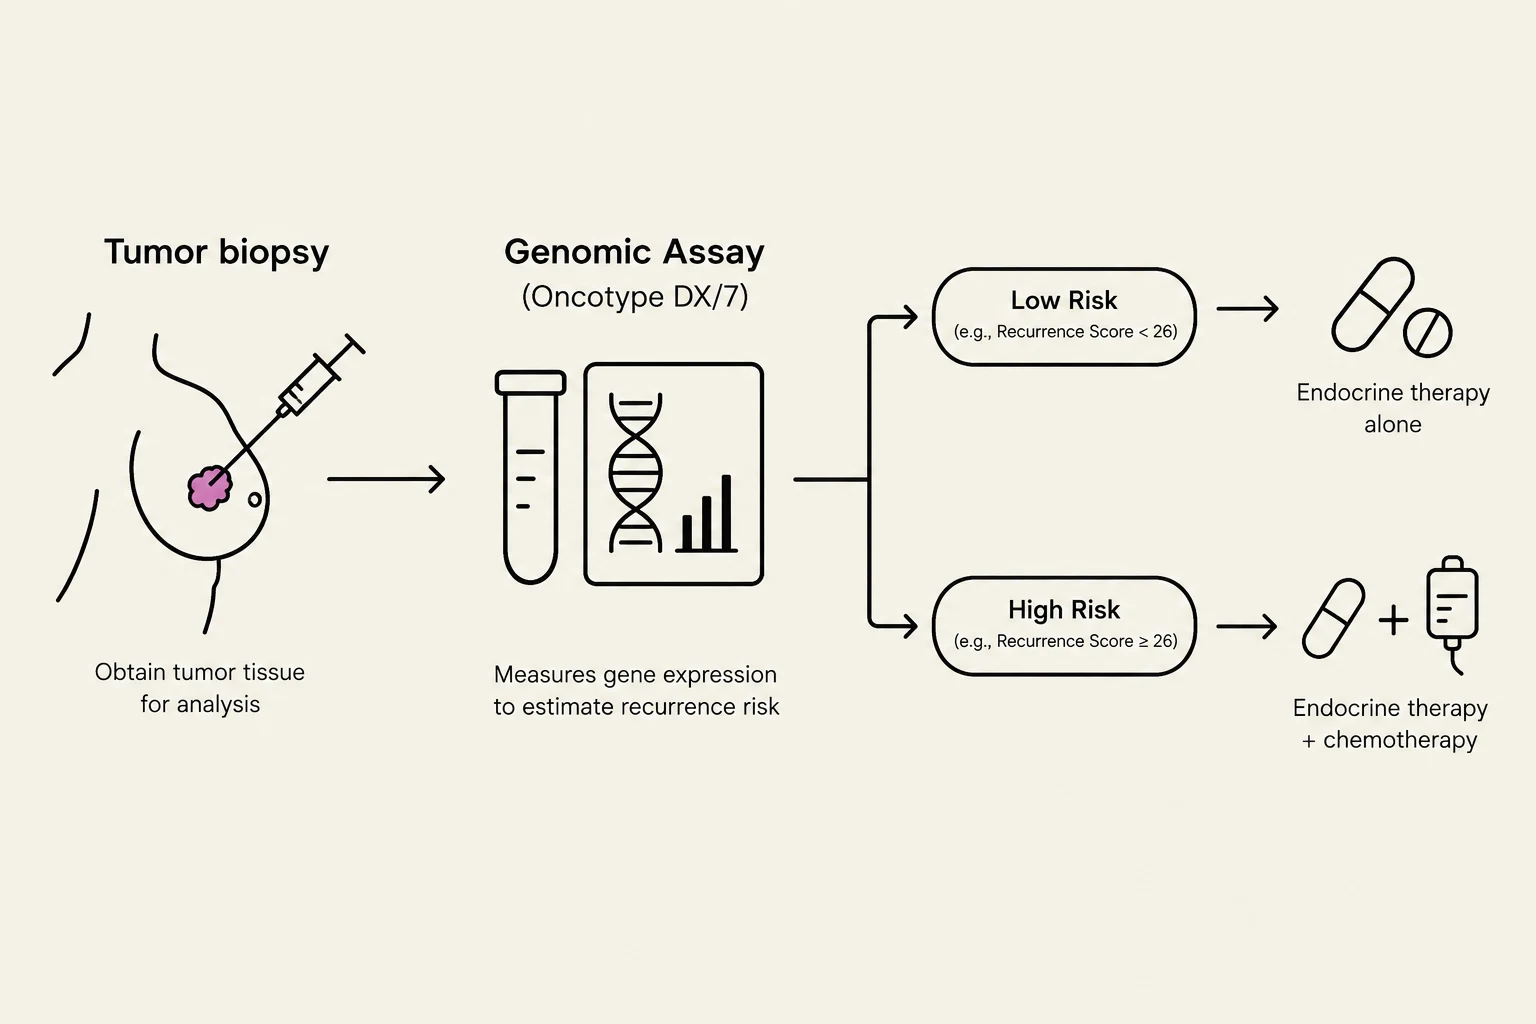
Genomic assays analyze the expression of specific genes to provide a quantitative assessment of risk. The 21-gene recurrence score (Oncotype DX) and the 70-gene signature are pivotal tools used to guide these decisions. By evaluating the expression levels of genes involved in proliferation and hormone signaling, these assays can categorize patients into low, intermediate, or high risk of distant recurrence.
This diagram illustrates the process of tumor biopsy and genomic assay (Oncotype DX/7) to determine recurrence risk in cancer patients. Based on the risk assessment (low or high), patients receive either endocrine therapy alone or a combination of endocrine therapy and chemotherapy.
Advanced Predictive Markers
Beyond standard recurrence scores, newer assays provide more granular data. The PAM50 risk of recurrence score helps refine the molecular subtype and prognosis, while the Breast Cancer Index (BCI) assay is specifically utilized to predict the risk of distant recurrence and assist clinicians in determining if a patient requires extended endocrine therapy.
Exam Tip: When evaluating a patient with ER+/HER2- disease, always look for the genomic assay results. A low recurrence score often indicates that chemotherapy may be omitted without compromising survival, whereas a high score strongly suggests the benefit of chemotherapy.
Targeted and Endocrine Therapies
Targeted therapies have revolutionized the treatment of specific molecular subtypes, particularly HER2-positive and BRCA-mutated cancers.
HER2-Targeted Therapy
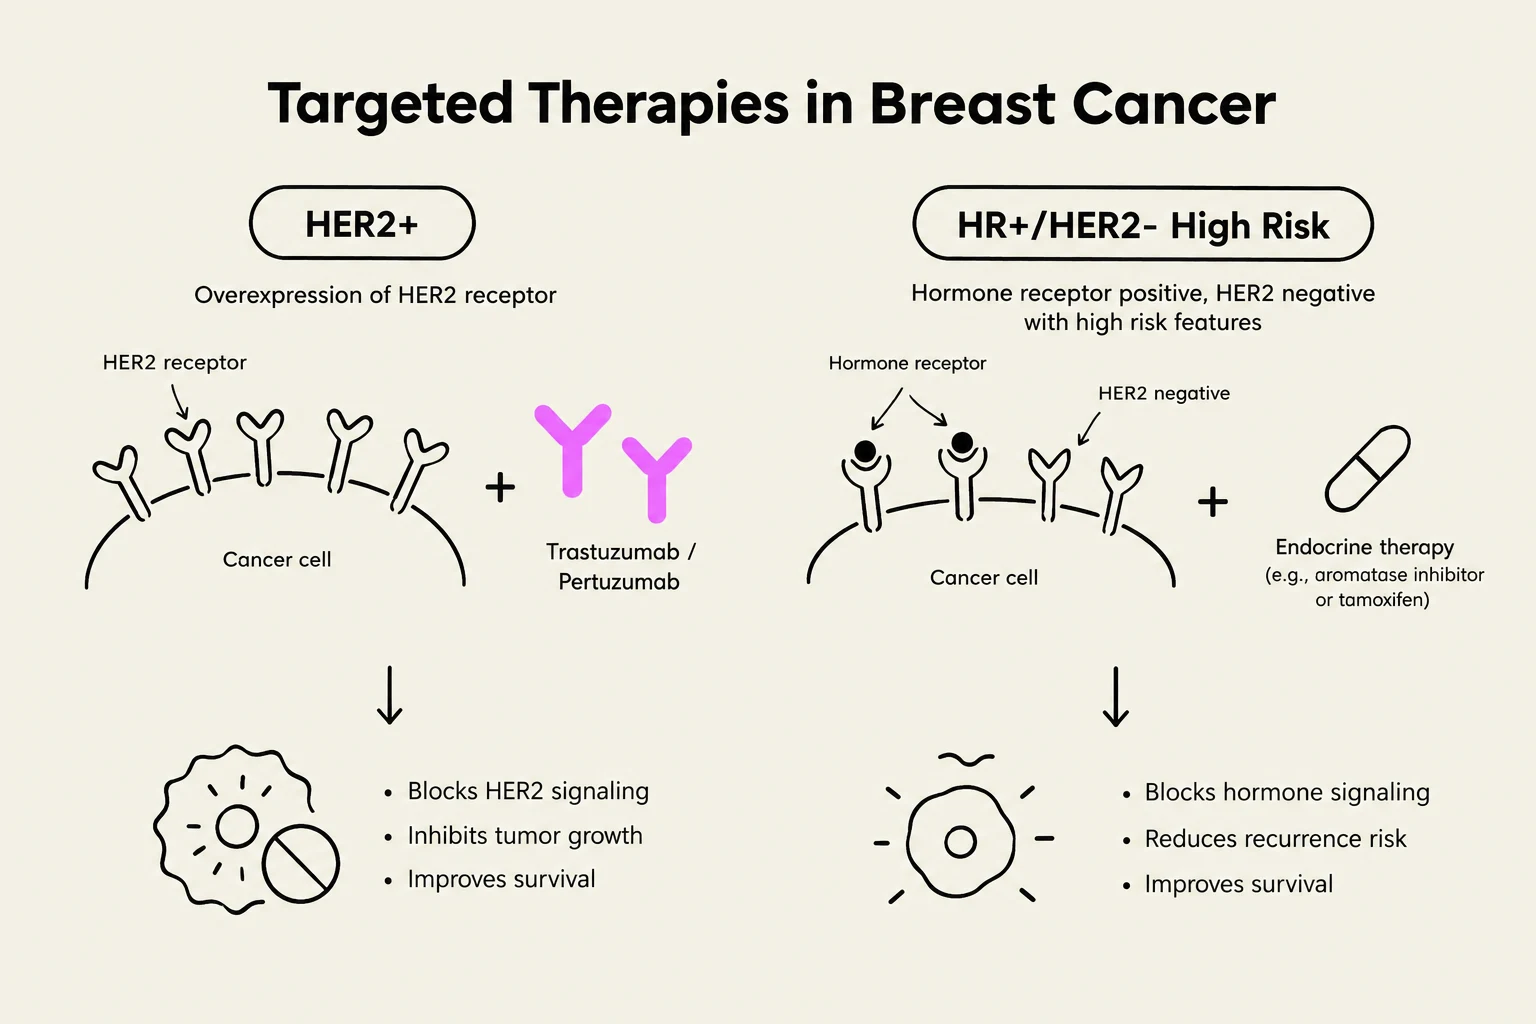
For patients with HER2-positive disease, the standard of care involves blocking the HER2 signaling pathway. Clinical evidence from trials such as HERA and APT supports the use of trastuzumab and pertuzumab. In the neoadjuvant setting (treatment before surgery), dual blockade with trastuzumab and pertuzumab has shown significant efficacy. Furthermore, for patients who exhibit residual invasive disease following neoadjuvant therapy, trastuzumab emtansine (T-DM1) or fam-trastuzumab deruxtecan-nxki are indicated to reduce the high risk of recurrence.
CDK4/6 Inhibitors and Endocrine Therapy
In the HR+/HER2- setting, the addition of CDK4/6 inhibitors to endocrine therapy has become a cornerstone of treatment for high-risk patients. The monarchE trial provided landmark evidence supporting the use of abemaciclib in high-risk, node-positive, early breast cancer. While other inhibitors like palbociclib (investigated in the PALLAS and Penelope-B trials) and ribociclib have been studied, the clinical application varies based on the specific risk profile and nodal status.
PARP Inhibitors and BRCA Status
The presence of germline BRCA1 or BRCA2 mutations significantly alters the adjuvant strategy. The OlympiA trial demonstrated that olaparib, a PARP inhibitor, provides a survival benefit for patients with high-risk, early-stage breast cancer harboring these mutations.
This diagram illustrates targeted therapies for breast cancer, differentiating between HER2+ and HR+/HER2- high-risk types, and their respective treatment mechanisms.
Chemotherapy and Dosing Strategies
Despite the rise of targeted agents, cytotoxic chemotherapy remains a vital component of adjuvant therapy, particularly for HR-negative or high-risk HER2-positive disease.
Regimen Selection and Dose Intensity
Standard regimens often involve anthracycline-based combinations, such as doxorubicin and cyclophosphamide, or taxane-based regimens using docetaxel or paclitaxel. Clinical meta-analyses have highlighted the importance of dose intensity; specifically, dose-dense chemotherapy schedules—which deliver drugs more frequently—may offer superior outcomes compared to conventional, more spaced-out schedules.
Sequential vs. Concurrent Approaches
Research, including studies like NSABP B-28, has investigated the efficacy of adding sequential taxanes to standard regimens to improve outcomes in patients with node-positive disease.
Bone-Targeted Therapy and Supportive Care
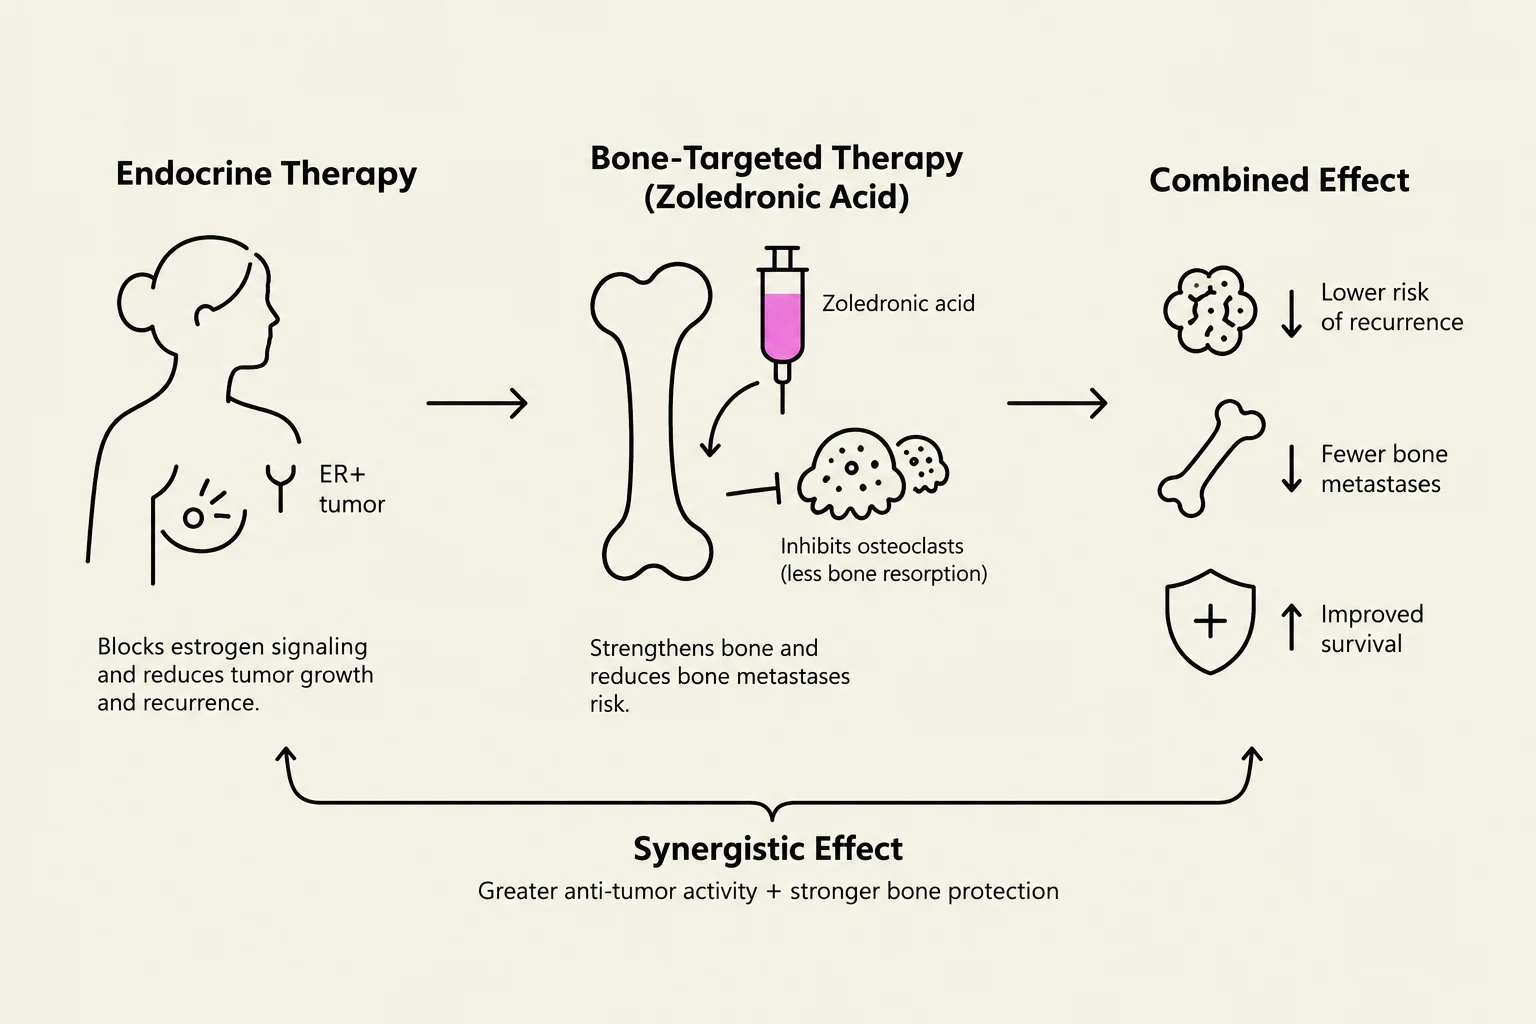
For certain patient populations, particularly premenopausal women receiving endocrine therapy, managing bone health is a critical component of adjuvant care. The use of bone-modifying agents like zoledronic acid or denosumab alongside endocrine therapy is supported by evidence to help reduce the risk of recurrence and manage bone density.
This diagram illustrates the combined effect of endocrine therapy and bone-targeted therapy (Zoledronic Acid) in treating ER+ breast cancer. Endocrine therapy blocks estrogen signaling, reducing tumor growth and recurrence. Zoledronic acid inhibits osteoclasts, strengthening bone and reducing the risk of bone metastases. The synergistic effect leads to a lower risk of recurrence, fewer bone metastases, and improved survival.
Summary of Evidence-Based Strategies
The following table summarizes the key clinical evidence discussed:
Molecular Subtype
Key Targeted Agent
Supporting Evidence/Trial
HER2-Positive
Trastuzumab + Pertuzumab
HERA, APT, NeoAdjuvant trials
HR+/HER2- (High Risk)
Abemaciclib
monarchE trial
BRCA1/2 Mutation
Olaparib
OlympiA trial
ER+/HER2- (Low Risk)
Endocrine Therapy alone
Oncotype DX / 70-gene signature
As molecular profiling continues to advance, the ability to precisely match a patient's tumor biology to the most effective adjuvant therapy will continue to improve survival and reduce unnecessary toxicity.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.