An overview of acute complications of Diabetes Mellitus (DM), including Diabetic Ketoacidosis (DKA), Hyperosmolar Hyperglycemic State (HHS), and hypoglycemia. Discusses their causes, clinical manifestations, and management strategies.
Diabetes mellitus (DM) is a chronic multisystem disease characterized by abnormal insulin production, impaired insulin utilization, or both. While long-term management focuses on preventing chronic complications like retinopathy or nephropathy, patients and healthcare providers must be equally vigilant regarding acute, life-threatening emergencies. These acute complications—primarily Diabetic Ketoacidosis (DKA), Hyperosmolar Hyperglycemic State (HHS), and hypoglycemia—require rapid recognition and precise intervention to prevent severe morbidity or death.
Diabetic Ketoacidosis (DKA)
Diabetic ketoacidosis is a profound metabolic crisis most commonly associated with Type 1 Diabetes, though it can occur in Type 2 patients. DKA is triggered by a severe deficiency of insulin, often due to infection, illness, or inadequate insulin dosage.
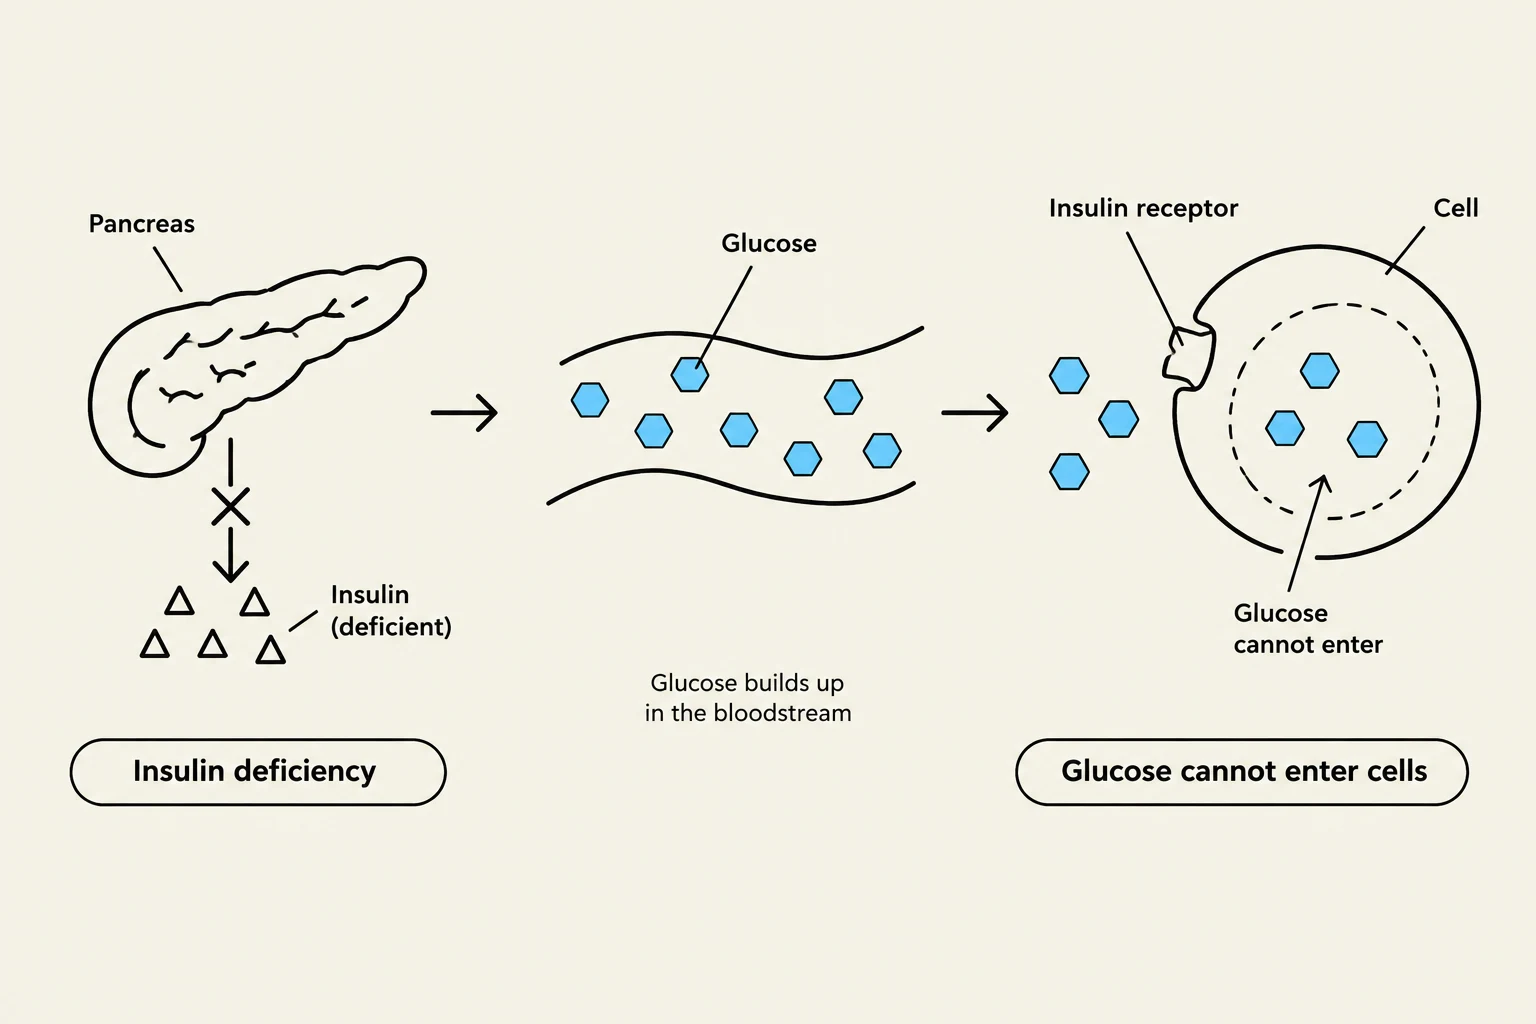
When the body cannot utilize glucose for energy due to the lack of insulin, it shifts to an alternative fuel source: fat. This process, known as lipolysis, breaks down fat stores to produce energy. A significant byproduct of this fat metabolism is the production of ketones. Because ketones are acidic, their accumulation in the bloodstream leads to metabolic acidosis, a state where the blood's pH balance is disrupted.
Clinical manifestations of DKA often present with a sudden onset. Patients may experience lethargy, weakness, tachycardia, and orthostatic hypotension due to severe dehydration. A hallmark sign is Kussmaul respirations—rapid, deep breathing patterns that the body employs in a desperate attempt to blow off carbon dioxide and reverse the metabolic acidosis. Additionally, patients may exhibit a characteristic "sweet, fruity" odor on their breath due to the presence of ketones.
Diagram illustrating insulin deficiency and its effect on glucose uptake by cells.
Exam Tip: If a patient presents with sudden onset hyperglycemia, abdominal pain, and Kussmaul respirations, suspect DKA. Always check for the presence of ketones in the urine.
Hyperosmolar Hyperglycemic State (HHS)
Hyperosmolar Hyperglycemic State (HHS) is a life-threatening syndrome that is less common than DKA but carries a high mortality rate. It typically occurs in older patients (over 60 years of age) with Type 2 Diabetes.
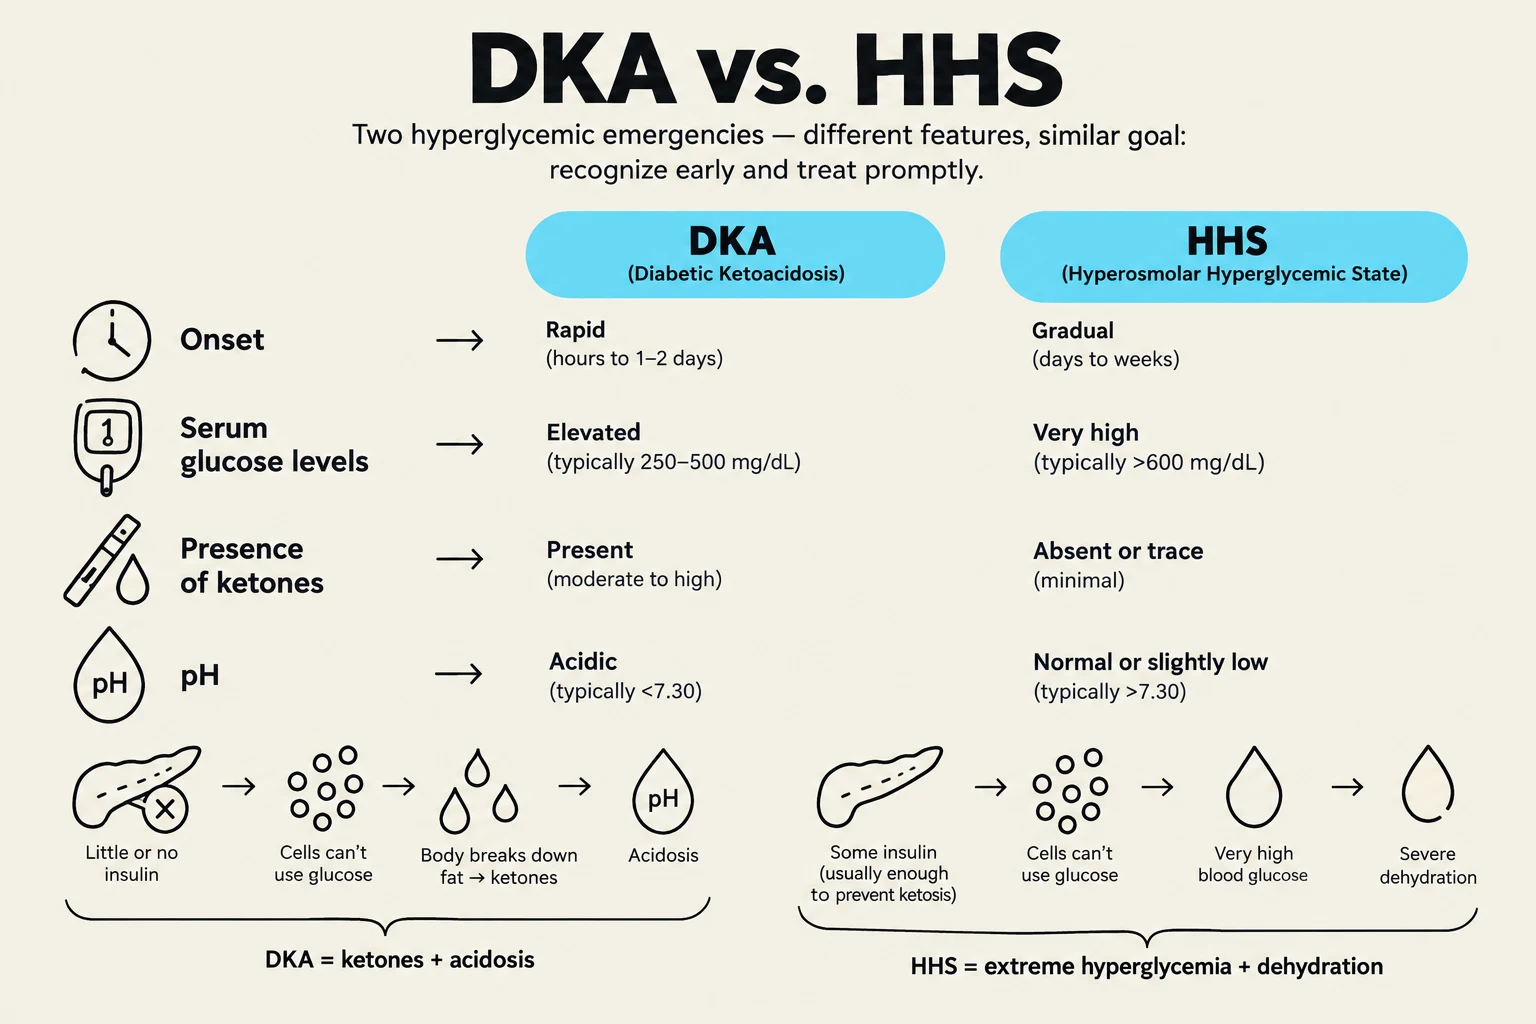
Unlike DKA, HHS is characterized by a more gradual onset. Because these patients usually have enough circulating insulin to prevent the breakdown of fats into ketones, they do not experience significant ketosis or metabolic acidosis. Instead, the primary issue is extreme hyperglycemia, often with blood glucose levels exceeding 34 mmol/L.
This massive amount of glucose in the blood increases the serum osmolality (the concentration of particles in the blood). This high osmotic pressure draws water out of the cells, leading to severe cellular dehydration and neurological manifestations, such as altered central nervous system function.
This diagram compares Diabetic Ketoacidosis (DKA) and Hyperosmolar Hyperglycemic State (HHS), two hyperglycemic emergencies, highlighting their distinct features and a shared goal of prompt recognition and treatment.
Management of DKA and HHS
The management of both DKA and HHS focuses on three pillars: fluid resuscitation, electrolyte correction, and insulin therapy.
Fluid Resuscitation and Electrolytes
The first priority is restoring volume and correcting dehydration. This is achieved through IV infusion of 0.45% or 0.9% NaCl to restore blood pressure and urine output. Because HHS involves more profound dehydration, it often requires more extensive fluid replacement than DKA.
During this process, clinicians must monitor electrolytes closely. Both conditions often lead to hypokalemia (low potassium levels). As insulin is administered, it causes potassium to shift from the bloodstream into the cells, which can further deplete vascular potassium levels. Therefore, potassium replacement is frequently necessary.
Insulin Therapy
In DKA, insulin therapy typically involves an insulin bolus followed by a continuous insulin drip. However, a critical safety rule is that insulin therapy should be withheld until fluid resuscitation has begun. If insulin is given too early, it can drive water and potassium into the cells too rapidly, potentially causing a collapse in vascular volume and worsening hypokalemia.
As blood glucose levels drop toward 14 mmol/L in DKA patients, 5% dextrose is added to the IV regimen to prevent the patient from sliding into hypoglycemia.
Hypoglycemia
While the previous two conditions involve high blood sugar, hypoglycemia is the danger of blood glucose levels falling below 4 mmol/L. This is most commonly caused by a mismatch between insulin action and food intake—for example, taking too much insulin relative to the amount of carbohydrates consumed.
Common symptoms include:
Hunger (polyphagia)
Fatigue and weakness
Confusion and irritability
Diaphoresis (sweating) and tremors
If left untreated, hypoglycemia can progress to seizures, loss of consciousness, coma, and death.
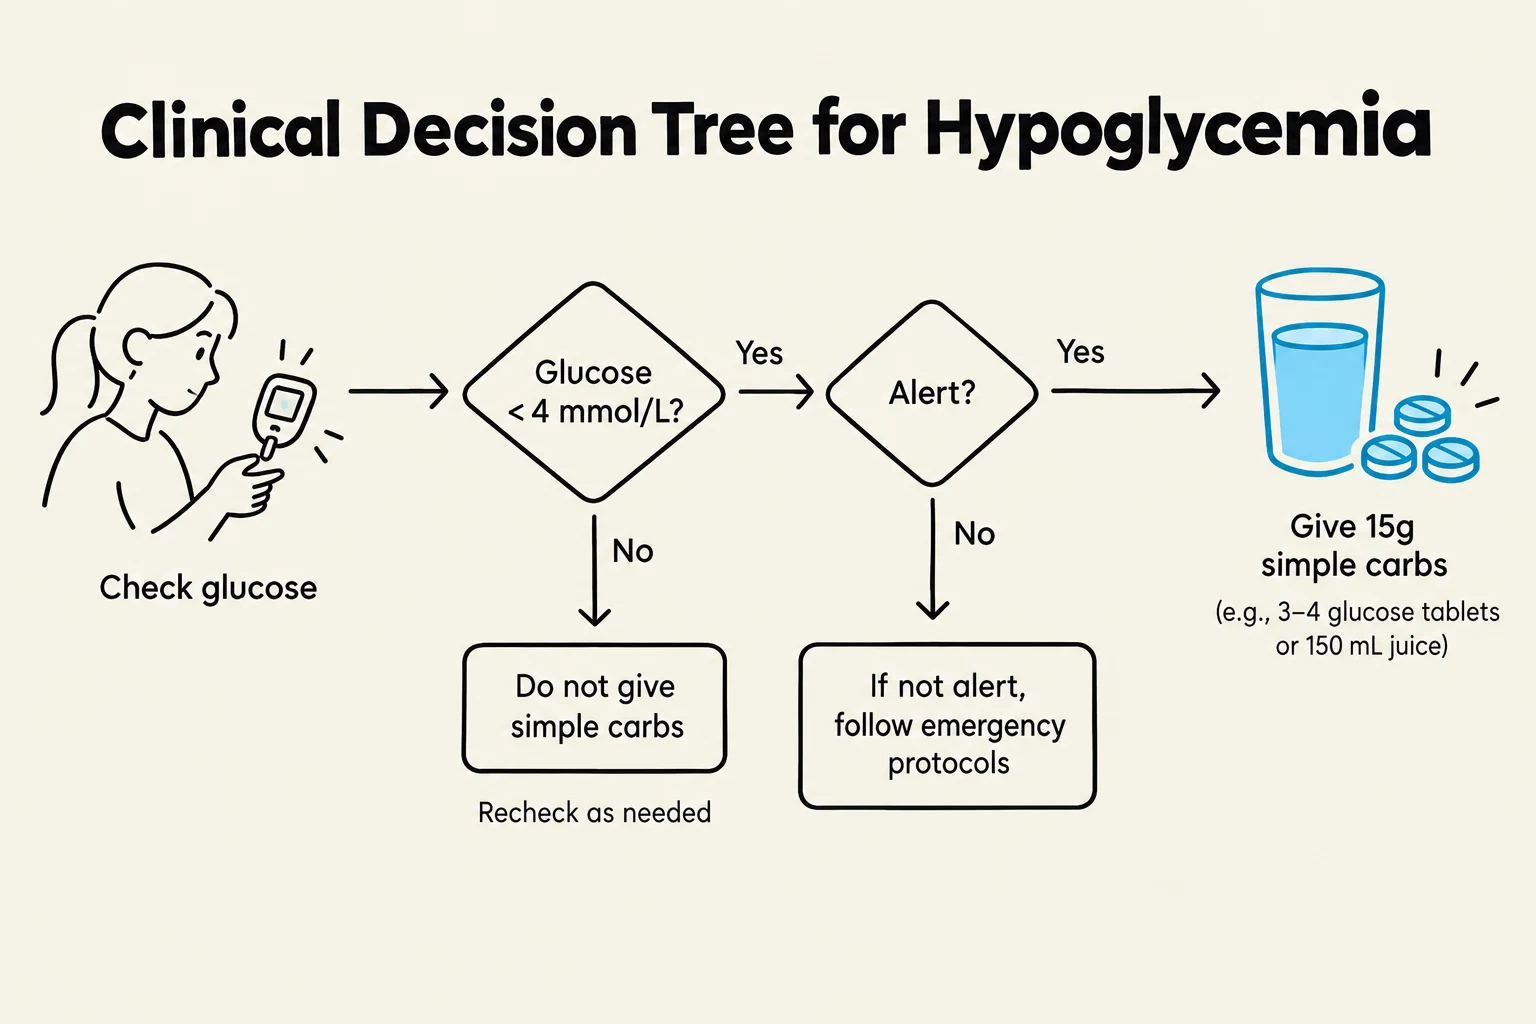
A clinical decision tree illustrating the steps to manage hypoglycemia, including checking glucose levels, administering simple carbohydrates, and following emergency protocols if necessary.
Clinical Note: In the elderly, patients may experience "hypoglycemic unawareness" due to autonomic neuropathy, meaning they do not feel the warning signs of dropping blood sugar.
Treatment Protocols
For an alert patient, the "15-15 Rule" is often employed: consume 15g of a simple carbohydrate (like 175 mL of fruit juice), wait 15 minutes, and recheck blood glucose. If the patient is unconscious, medical intervention is required, such as 1 mg of glucagon administered intramuscularly or 20 to 50 mL of 50% dextrose via IV push.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.