This reading explains the underlying mechanisms of epilepsy, focusing on the ionic basis of action potentials, neurotransmitter imbalances, and the classification of seizures. It details how disruptions in ion channel function and neurotransmitter systems lead to abnormal neuronal firing and seizures.
Epilepsy is a neurological disorder characterized by recurrent, unprovoked seizures, which are transient alterations in brain function caused by abnormal electrical activity. While a single episode of such activity is termed a "seizure," epilepsy refers to the underlying tendency to experience these events repeatedly. At its core, epilepsy is a breakdown in the delicate balance of electrical signaling within the brain, where the mechanisms meant to regulate and isolate nerve signals fail, leading to excessive and synchronized neuronal firing.
The Ionic Basis of the Action Potential
To understand epilepsy, one must first understand how a healthy neuron communicates. Nerve signaling relies on the movement of ions across the cell membrane through voltage-gated ion channels (VGICs).
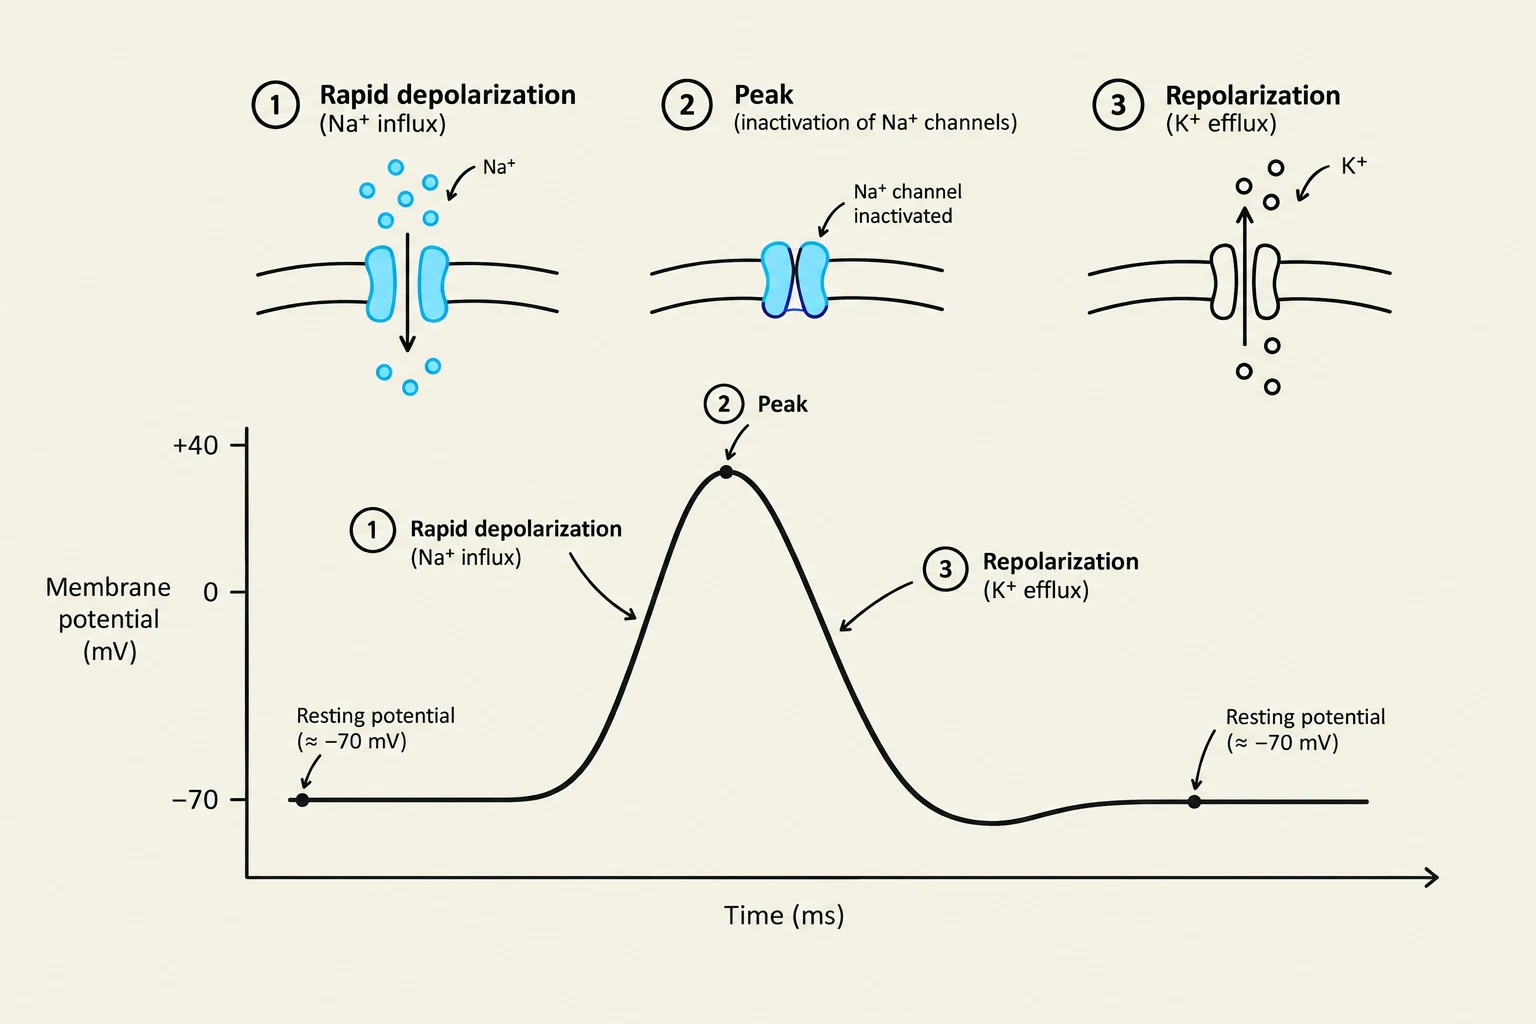
When a neuron receives a stimulus, it undergoes membrane depolarization, a process where the interior of the cell becomes less negative. This depolarization is primarily driven by the rapid opening of voltage-gated Na+ channels (VGSC), allowing sodium ions to rush into the cell. This rapid influx is responsible for the rising phase of the action potential.
To prevent the cell from remaining in a permanent state of excitation, the cell must repolarize. This is achieved through two main mechanisms:
The inactivation of VGSCs.
The opening of voltage-gated K+ channels (VGKC), which allow potassium ions to exit the cell, restoring a negative membrane potential.
Diagram illustrating the phases of an action potential in a neuron, including rapid depolarization due to Na+ influx, peak potential with Na+ channel inactivation, and repolarization via K+ efflux, returning to resting potential.
Exam Tip: Remember that VGSC opens much faster than VGKC. The speed of VGSC opening drives depolarization, while the subsequent VGKC opening drives repolarization.
Mechanisms of Control: Preventing Repetitive Firing
A critical safeguard against seizures is the refractory period. This is the time during which a neuron cannot fire another action potential immediately after one has occurred. This period is determined by the time it takes for VGSCs to transition from an "inactivated" state back to a "resting" state.
In a healthy brain, this inactivation imposes a "time-limit" on how frequently a neuron can fire. If neurons fire at a normal, low frequency, there is ample time for these channels to recover. However, if a group of neurons overrides these limits, they begin repetitive nerve firing. This excessive firing can lead to a "Paroxysmal Depolarization Shift" (PDS), characterized by high-voltage, long-lasting depolarization currents caused by a massive influx of Na+ and Ca2+.
Neurotransmitter Imbalance: Glutamate vs. GABA
The brain maintains electrical stability through the balance of excitatory and inhibitory neurotransmission.
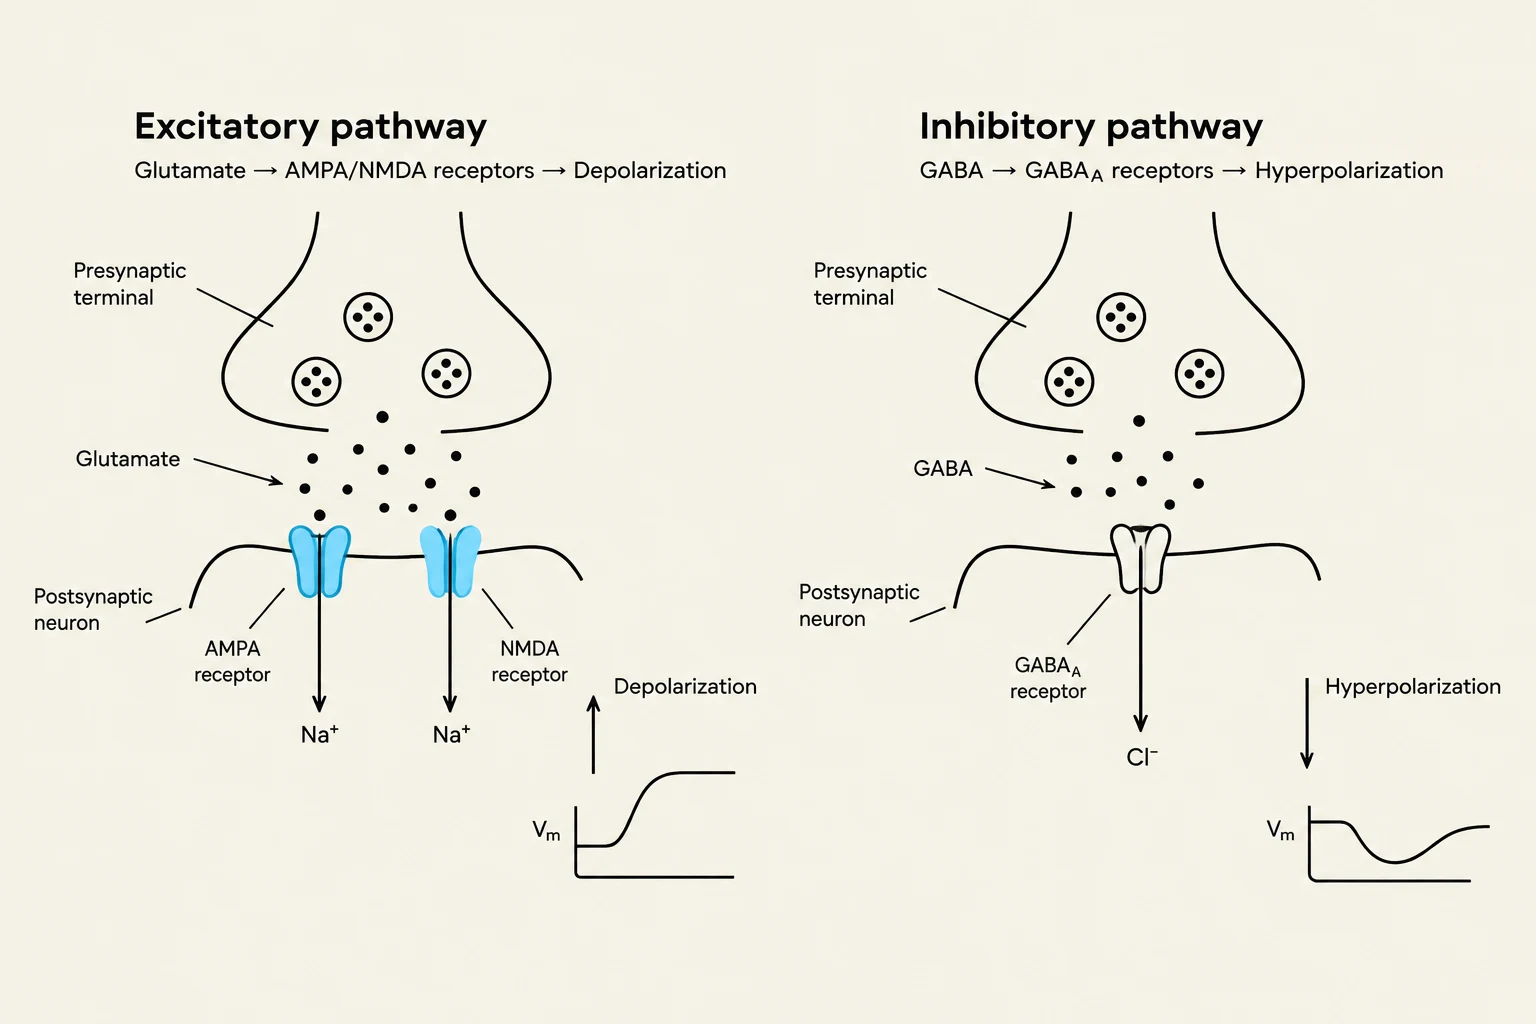
Excitatory Neurotransmission: Driven by Glutamate, the primary excitatory neurotransmitter. Glutamate acts on ionotropic receptors, specifically AMPA receptors (responsible for fast transmission) and NMDA receptors. Excessive glutamate activity promotes depolarization and seizure activity.
Inhibitory Neurotransmission: Driven by GABA (gamma-aminobutyric acid). GABAergic interneurons release GABA to inhibit surrounding neurons, primarily through GABA type A receptors.
In epilepsy, the goal of the brain is to prevent synchronization—the phenomenon where a large group of neurons all fire at the exact same time. GABAergic interneurons are the primary defense against this; they act as "brakes" to ensure that neuronal signals remain isolated and do not spread uncontrollably across the cortex.
Diagram illustrating the difference between excitatory and inhibitory neural pathways, showing the roles of glutamate and GABA in synaptic transmission and their effects on postsynaptic neuron membrane potential.
Classification of Seizures
Seizures are classified based on where they begin in the brain and how they manifest clinically.
Focal Onset Seizures
Focal seizures (formerly called partial seizures) begin in a specific group of neurons limited to one side of a cerebral hemisphere.
Focal Aware Seizures: The patient remains conscious. Symptoms depend on which cortical area is affected (e.g., sensory or motor changes).
Focal Impaired Awareness Seizures: The patient's consciousness or contact with reality is affected. This may include automatisms (repetitive, involuntary movements like lip-smacking or hand-rubbing).
Focal seizures can sometimes progress into focal to bilateral tonic-clonic seizures, where the activity starts in one focus and spreads to both hemispheres via the corpus callosum or thalamic projections.
Generalized Onset Seizures
Generalized seizures involve both cerebral hemispheres from the very beginning.
Absence Seizures (Petit Mal): These are characterized by brief "staring spells" and a loss of consciousness. On an EEG, they typically show a very specific 3-Hz spike-and-wave activity, often linked to abnormal activity in the thalamus involving T-type Ca2+ channels.
Tonic-Clonic Seizures (Grand Mal): These are more dramatic and involve a sudden loss of consciousness. They typically consist of two phases:
Tonic Phase: Sustained muscle contraction and limb extension.
Clonic Phase: Rhythmic, jerking limb movements.
Summary Table: Seizure Comparison
Feature
Absence Seizure
Tonic-Clonic Seizure
Onset
Generalized
Generalized
Consciousness
Brief lapse/staring
Sudden loss
Motor Symptoms
Minimal (maybe brief twitches)
Intense (Tonic contraction → Clonic jerking)
EEG Pattern
3-Hz spike-and-wave
High-voltage discharges
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.